

Introduction to First Aid Medical Emergencies
1. General Approach (Golden Rules)
When approaching someone who is suddenly ill, always follow a systematic approach to ensure you do not miss a life-threatening issue:
🧠 The DRABC Approach
- D — Danger: Check the scene is safe for you, the casualty, and bystanders. Look out for traffic, fire, chemical fumes, or live wires. (Remember: A dead rescuer helps no one!)
- R — Response: Check if the casualty is responsive using the AVPU scale:
- A — Alert (fully awake, eyes open).
- V — Responds to Voice (opens eyes when you shout).
- P — Responds to Pain (reacts when you firmly pinch their shoulder or earlobe).
- U — Unresponsive (completely unconscious).
- A — Airway: Open the airway using the head-tilt, chin-lift maneuver. Look inside for any visible obstruction (like vomit or food).
- B — Breathing: Look, listen, and feel for normal breathing for up to 10 seconds.
- If breathing normally but unconscious → place them in the recovery position to keep the airway clear.
- If NOT breathing normally (or just gasping) → call for help and start CPR immediately.
- C — Circulation: Check the pulse, note the skin colour (pale or blue?), check temperature (hot or cold?), and control any severe bleeding if present.
- Call for help early: Shout for a bystander to call an ambulance or arrange transport to the nearest Health Centre while you stay with the casualty.
- Reassure the casualty constantly: Severe anxiety makes the heart work harder and worsens most medical emergencies.
- Do no harm: Never give food, drink, or oral medicine to a drowsy or unconscious casualty (they will aspirate/choke on it).
HISTORY-TAKING MNEMONIC: SAMPLE
To figure out exactly why the person is sick, ask these questions to them or their relatives:
| Letter | Meaning | Question to Ask |
|---|---|---|
| S | Signs & Symptoms | What do you see? What does the casualty feel? (e.g., "My chest hurts"). |
| A | Allergies | Are they allergic to any drugs, foods, or insect stings? |
| M | Medicines | What medicines do they take daily? (e.g., insulin, asthma inhalers, antihypertensives). This is a huge clue to their underlying disease. |
| P | Past Medical History | Do they suffer from diabetes, asthma, epilepsy, hypertension, or heart disease? |
| L | Last Meal | When did they last eat or drink? (Crucial if they need emergency surgery, or if they are hypoglycaemic). |
| E | Events | What exactly were they doing leading up to the emergency? (e.g., running in the hot sun). |
1.4 The Nurse's Role in a Medical Emergency
- Assess and recognise the emergency quickly (primary survey + SAMPLE history).
- Give immediate first aid within your scope of practice to stabilize the patient.
- Arrange urgent referral along the Uganda referral chain (Village Health Team → HC II → HC III → HC IV/Hospital). You must write a clear referral note detailing what happened and what you did.
- Document: Record the time of onset, vital signs, treatment given, and the patient's response.
- Educate: Teach the casualty and family on how to prevent a recurrence of the emergency.

Topic 2: Fainting (Syncope)
2.1 Definition
Fainting (syncope) is a sudden, temporary loss of consciousness and postural tone (they collapse) caused by a short-lived reduction of blood flow (and therefore oxygen) to the brain.
Why it happens: The brain requires a constant, heavy supply of oxygenated blood. If blood pressure drops suddenly, gravity pulls blood away from the head. The brain shuts down consciousness to force the body to fall flat, putting the head and heart on the same level so blood can easily flow back to the brain! It usually lasts only seconds to a few minutes, and recovery is rapid and complete if the casualty is laid flat.
2.2 Types of Syncope
- Vasovagal syncope (Commonest, ~50%+): A reflex drop in heart rate and blood pressure triggered by sudden pain, extreme fear, emotional shock, the sight of blood, or prolonged standing in a hot environment.
- Orthostatic (postural) hypotension: Blood pools in the legs when standing up too quickly, causing dizzy spells. Very common in dehydration, older adults, pregnant women, and patients taking strong blood pressure drugs.
- Situational syncope: Triggered by specific bodily actions like violent coughing, sneezing, swallowing, urination (micturition syncope), or severe straining during defecation.
- Cardiac syncope: Caused by an abnormal heart rhythm (arrhythmia) or heart valve disease. This is serious and may occur suddenly during exertion, with absolutely no warning signs.
- Other causes: Hypoglycaemia (low sugar), anaemia (low blood count), heat exposure, severe pain, vaginal bleeding (e.g., a ruptured ectopic pregnancy), and stroke (rare).
2.3 Signs and Symptoms
- Before fainting (Prodrome/warning signs): Light-headedness / dizziness ("feeling like the world is spinning"). Nausea, yawning heavily, feeling suddenly very warm. Sweating, with cold, clammy (moist) skin. Extreme paleness (pallor), blurring or narrowing of vision ("tunnel vision"), and ringing in the ears. Pulse is initially slow, but may later quicken to compensate.
- During fainting: The person collapses; brief loss of consciousness. Usually recovers within 20–60 seconds once they are lying flat. Brief, mild muscle twitching may occur (do not confuse this with full epilepsy).
- After fainting: Rapid recovery, but they may feel weak, embarrassed, and nauseated.
2.4 First Aid Management
- Check DRABC. If you see the casualty falling, step in to ease them to the ground and protect their head from hitting hard surfaces.
- Lay the casualty flat on their back and raise their legs about 30 cm (above heart level). Explanation: Raising the legs allows gravity to pull pooled blood from the legs directly back to the heart, which then pumps it straight to the brain, waking them up instantly.
- Loosen tight clothing (collar, belt, tie) to improve blood flow.
- Ensure a good supply of fresh air — open windows and firmly ask crowds of bystanders to stand back and give them space.
- Reassure the casualty once they recover; explain gently what happened to calm them down.
- When fully recovered, let them sit up gradually (sitting for a few minutes first, then standing slowly to observe if the dizziness returns).
- Once they are fully alert and can swallow perfectly, give them water or a sweet drink (especially if the faint was caused by hunger, dehydration, or heat).
- If they are NOT breathing normally at any point → assume cardiac arrest, start CPR, and call for emergency help.
🚨 What NOT To Do
- Do not give anything to eat or drink while the casualty is drowsy or not fully awake (massive risk of choking and aspirating fluid into the lungs).
- Do not crowd around the casualty or allow panic to spread.
- Do not slap their face, shake them violently, or pour buckets of water over their face to "wake them up".
- Do not let the person stand up quickly or walk away immediately; they will likely faint again.
2.6 When to Refer / Seek Medical Help
Urgently refer the patient to a health facility if:
- Fainting occurred suddenly without warning, during exercise, or while they were lying down (this points to a dangerous heart problem).
- The casualty does not wake up within 1 minute, or recovers but remains highly confused.
- There is associated chest pain, severe breathlessness, or palpitations.
- They sustained an injury during the collapse (e.g., they hit their head — watch closely for later drowsiness or vomiting indicating bleeding in the brain).
- The casualty is pregnant, elderly, or has a history of heart disease, diabetes, or severe anaemia.
- The fainting spells are recurrent.

Topic 3: Diabetic Emergencies
3.1 Background
Diabetes mellitus is a chronic metabolic condition where blood glucose (sugar) is poorly controlled due to issues with the hormone Insulin.
- Type 1: The pancreas produces little to no insulin. The patient absolutely needs daily insulin injections to survive.
- Type 2: The body has insulin resistance (it produces insulin, but the cells ignore it). Managed with diet, oral tablets, and sometimes insulin injections.
Normal fasting blood glucose is 3.9–6.1 mmol/L (70–110 mg/dL). There are two major diabetic emergencies: HYPOglycaemia (dangerously low sugar) and HYPERglycaemia (dangerously high sugar, which may lead to DKA/HHS coma). Hypoglycaemia is the most common diabetic emergency in the community. It develops incredibly fast and can kill the brain quickly.
3.2 HYPOGLYCAEMIA (Low Blood Sugar)
Definition: Blood glucose falls to < 3.9 mmol/L (< 70 mg/dL) with symptoms.
Why it kills: The brain cannot store its own glucose. It relies on a continuous supply from the blood every single second. If blood sugar drops too low, the brain starves, leading to confusion, seizures, coma, and permanent brain death.
Causes (Think: "Too much insulin or Too little sugar")
- Missed or delayed meals, or eating an inadequate amount of food.
- Taking too much insulin or diabetes tablets (accidental overdose, or taking the wrong dose).
- Unusual, heavy physical exertion or exercise without eating extra food to compensate.
- Drinking alcohol (especially on an empty stomach, which blocks the liver from releasing stored sugar).
- Vomiting or diarrhoea; severe fever or infection.
Signs and Symptoms (Develop SUDDENLY — in minutes)
- Feeling extremely shaky, trembling, intensely hungry.
- Skin becomes very sweaty, cold, and clammy (moist).
- Palpitations (heart pounding fast) and rapid pulse.
- Pale skin.
- Anxiety, irritability, sudden confusion, unusual bizarre behaviour, or aggression (the person may look and act like they are drunk!).
- Blurred vision, dizziness, severe headache, and slurred speech.
- Drowsiness progressing to deep unconsciousness and violent seizures if left untreated.
First Aid — CONSCIOUS Casualty
- Give fast-acting sugar IMMEDIATELY (about 15–20 g): 3–4 glucose tablets, OR 150 ml of fruit juice or a regular (NOT diet) sugary soft drink, OR 2–3 teaspoons of ordinary sugar or honey dissolved in a little water.
- Wait 15 minutes, then recheck their symptoms (or recheck blood glucose if you have a glucometer).
- If their sugar is still low or they are still symptomatic → repeat the fast-acting sugar dose.
- Once they have recovered and feel better → give them a longer-acting carbohydrate snack (like a slice of bread, a banana, or a glass of milk). Explanation: Fast sugar spikes the blood level quickly, but it crashes fast too. The complex carbs provide a slow, steady release of energy to prevent a relapse.
- Help them find the cause of the drop, and advise the casualty to inform their health worker to review their treatment doses.
First Aid — UNCONSCIOUS Casualty (Severe Hypoglycaemia)
- Do NOT give anything by mouth! (They will choke and die).
- Place them carefully in the recovery position to protect their airway; check breathing continuously.
- If at a health facility: Administer 50% Dextrose 50 ml IV slowly (this is a critical nursing role), or give Glucagon 1 mg IM/SC if available.
- If in the community: You can carefully rub a thick paste of sugar or honey into their gums/buccal cavity (inside the cheek). It absorbs slowly through the lining of the mouth.
- Meanwhile, arrange URGENT transport to a health facility.
- After regaining full consciousness, give oral sugar and a solid carbohydrate snack.
3.3 HYPERGLYCAEMIA (High Blood Sugar)
Definition: Persistently high blood glucose, usually > 11 mmol/L (> 200 mg/dL) causing symptoms. Severe untreated forms lead to Diabetic Ketoacidosis (DKA) or Hyperosmolar Hyperglycaemic State (HHS).
Causes
- Missed insulin doses or running completely out of insulin.
- Severe infection (e.g., Malaria, Pneumonia, Urinary Tract Infection), illness, injury, or surgery. (Infections cause the body to release stress hormones which drastically raise blood sugar).
- Extreme stress, eating a very poor high-sugar diet, or being an undiagnosed diabetic.
Signs and Symptoms (Develop GRADUALLY — over hours to days)
- Intense, unquenchable thirst (polydipsia) and exceptionally frequent urination (polyuria). The body is trying to flush the toxic levels of sugar out through the urine.
- Dry mouth and extremely dry skin; a flushed, warm face.
- Deep weakness, fatigue, and blurred vision.
- Rapid, deep, sighing breathing (Kussmaul breathing). The body is trying to blow off toxic acids from the blood.
- Fruity or acetone smell on the breath (smells like nail polish remover or rotting apples, caused by ketones).
- Nausea, severe vomiting, and acute abdominal pain.
- Confusion and drowsiness leading slowly to a deep coma (DKA/HHS).
First Aid
- Sit or lay the casualty down comfortably; reassure them.
- If they are fully conscious: give them plain water to sip (they are severely dehydrated from urinating so much). Do not give sugary drinks.
- Urgent referral to hospital — DKA and HHS are highly life-threatening and require IV insulin drips and massive IV fluid replacement. You cannot fix this with first aid.
- If unconscious: place in the recovery position, give absolutely nothing by mouth, check breathing constantly, and transport urgently.
📝 EXAM STRATEGY: Hypo vs Hyper Comparison
| Feature | HYPOglycaemia (Low Sugar) | HYPERglycaemia (High Sugar) |
|---|---|---|
| Onset | Sudden (Minutes) | Gradual (Hours to Days) |
| Skin | Pale, cold, sweaty (clammy) | Dry, flushed, warm |
| Breathing | Normal | Rapid and deep (Kussmaul) |
| Breath Smell | Normal | Fruity / Acetone (Ketones) |
| Consciousness | Confused, aggressive → sudden collapse | Drowsy, lethargic → slow coma |
| Food Response | Responds very quickly to sugar | Does NOT improve with sugar |
| Emergency Action | Give sugar NOW! | Give water + Urgent hospital referral |

Topic 4: Asthma Attack
4.1 Definition
Asthma is a chronic inflammatory disease of the airways characterized by reversible narrowing (bronchospasm), excess thick mucus production, and airway swelling. An asthma attack is a sudden, severe worsening of these symptoms; severe attacks can completely block the airway and be fatal.
4.2 Common Triggers
- Dust, pollen, smoke (including firewood smoke — a massive trigger in rural Uganda), and animal dander (hair/skin flakes).
- Respiratory infections like the common cold or flu.
- Heavy exercise, breathing very cold air, or sudden weather changes.
- Strong smells, harsh chemicals, and sprays (including some strong insecticides).
- Extreme emotional stress, severe anxiety, or even violent laughter.
- Certain medicines (like Aspirin, NSAIDs, or Beta-blockers) and some food preservatives.
4.3 Signs and Symptoms
- Wheezing: A high-pitched whistling sound heard primarily when the patient is breathing out (exhaling).
- Persistent dry cough (especially severe at night).
- Extreme difficulty breathing; complaining of severe chest tightness.
- Speaking in short sentences or single words because they are too breathless to complete a full thought.
- Using accessory muscles to breathe (you can see the skin between their ribs sucking in deeply); sitting hunched forward in the "tripod" position to force air into their lungs.
- Severe anxiety and visible fear in their eyes.
- IN A SEVERE ATTACK:
- Cyanosis: Blue lips and fingertips due to lack of oxygen.
- They become utterly exhausted and drowsy.
- "Silent Chest": You hear no wheeze at all. This is terrifying because it means the airways are so tight that air is hardly moving in or out. This is a pre-arrest sign!
4.4 First Aid Management
- Keep the casualty UPRIGHT (Sitting): Have them sit leaning slightly forward with their arms resting on a table or their knees. Explanation: Sitting upright allows gravity to pull the diaphragm down, giving the lungs maximum room to expand. NEVER lay an asthma casualty flat on their back; they will suffocate.
- Stay extremely calm and reassuring. Do not panic, and do not leave the casualty alone. Anxiety makes the airways constrict even tighter.
- Help them take their RELIEVER inhaler (usually Blue — Salbutamol):
- With a spacer (Best method): Spray 1 puff into the plastic spacer chamber, then have them take 4–6 deep breaths in and out of the spacer. Repeat this up to 4 puffs.
- Without a spacer: Spray 1 puff while they are breathing in slowly and deeply; ask them to hold their breath for ~4 seconds so the medicine settles in the lungs. Repeat to 4 puffs.
- Wait for 4 minutes. If their breathing has not returned to normal → give another 4 puffs in the exact same way.
- If there is little or no relief, or the attack was incredibly severe from the very start → call an ambulance / arrange urgent transport immediately. Continue giving 4 puffs every 4 minutes while travelling to the hospital.
- If the casualty becomes unconscious → check DRABC, place in the recovery position if breathing, or start CPR if not breathing.
🚨 What NOT To Do
- Do not lay the casualty flat.
- Do not give them a paper or plastic bag to breathe into! (That technique is strictly for anxiety/hyperventilation, NOT asthma. An asthmatic desperately needs fresh oxygen, not their own recycled carbon dioxide).
- Do not let them walk long distances to a health facility — the exertion will worsen the attack. Carry them or arrange transport.
Topic 5: Acute Chest Pain (Cardiac Emergency)
5.1 Definition and Causes
Chest pain becomes a critical cardiac emergency when it is caused by a severely reduced blood supply to the heart muscle itself.
- Angina pectoris: A temporary, reversible narrowing of the coronary arteries. The pain is often triggered by heavy exertion or strong emotion, and is typically relieved by rest or medication.
- Myocardial Infarction (Heart Attack): A coronary artery becomes completely blocked by a blood clot. The heart muscle begins to die from oxygen starvation. This is a massive emergency.
- Other causes of chest pain: Pulmonary embolism, pneumonia, pleurisy, severe acid reflux, peptic ulcers, muscular strain, or extreme anxiety. Always rule out a heart attack first!
5.2 Signs and Symptoms of a Heart Attack
- Central chest pain: Described as a crushing pressure, squeezing, tightness, or heavy ache ("It feels like an elephant is sitting on my chest"). It lasts more than a few minutes or comes and goes.
- Radiation: The pain often radiates (spreads) to the left arm, both arms, up into the neck, the jaw, the back, or the upper abdomen.
- Associated signs: Profuse, cold sweating; severe nausea and vomiting; sudden breathlessness; dizziness. An overwhelming sense of impending doom and extreme anxiety. The skin turns pale, grey, and ashen.
- Atypical signs: Women, the elderly, and diabetics may not have the classic crushing chest pain. They may present with unusual extreme fatigue, nausea, unexplained back or jaw pain, or mild abdominal discomfort. Do not ignore these!
- May progress suddenly to cardiac arrest (they collapse and stop breathing normally).
5.3 First Aid Management
- Stop all activity immediately.
- Sit the casualty down in a comfortable half-sitting (semi-reclined) position (e.g., sitting on the floor leaning back against a wall, with their knees bent and back supported). This eases the strain on the heart and makes breathing easier.
- Reassure them constantly.
- Call for emergency help immediately (ambulance or transport to a facility with oxygen and ECG capabilities). In heart attacks, "Time equals Heart Muscle."
- Loosen tight clothing around the neck, chest, and waist. Keep the casualty warm but not overheated.
- Chewable Aspirin: If available, if the casualty is an adult, fully conscious, and has no known aspirin allergy or active bleeding disorder (like a stomach ulcer) → give them Aspirin 300 mg to CHEW. Explanation: Aspirin is an anti-platelet drug. Chewing it absorbs it quickly into the blood, where it helps stop the deadly clot in the heart from growing larger.
- If the casualty has their own prescribed Angina medication (like GTN spray or tablets under the tongue), help them take it.
- Monitor them very closely: pulse, breathing, and level of response. Have your hands ready to start CPR the moment they collapse and stop breathing normally.
- Urgent referral: Never let a suspected heart attack casualty walk to the car or drive themselves. Carry them.
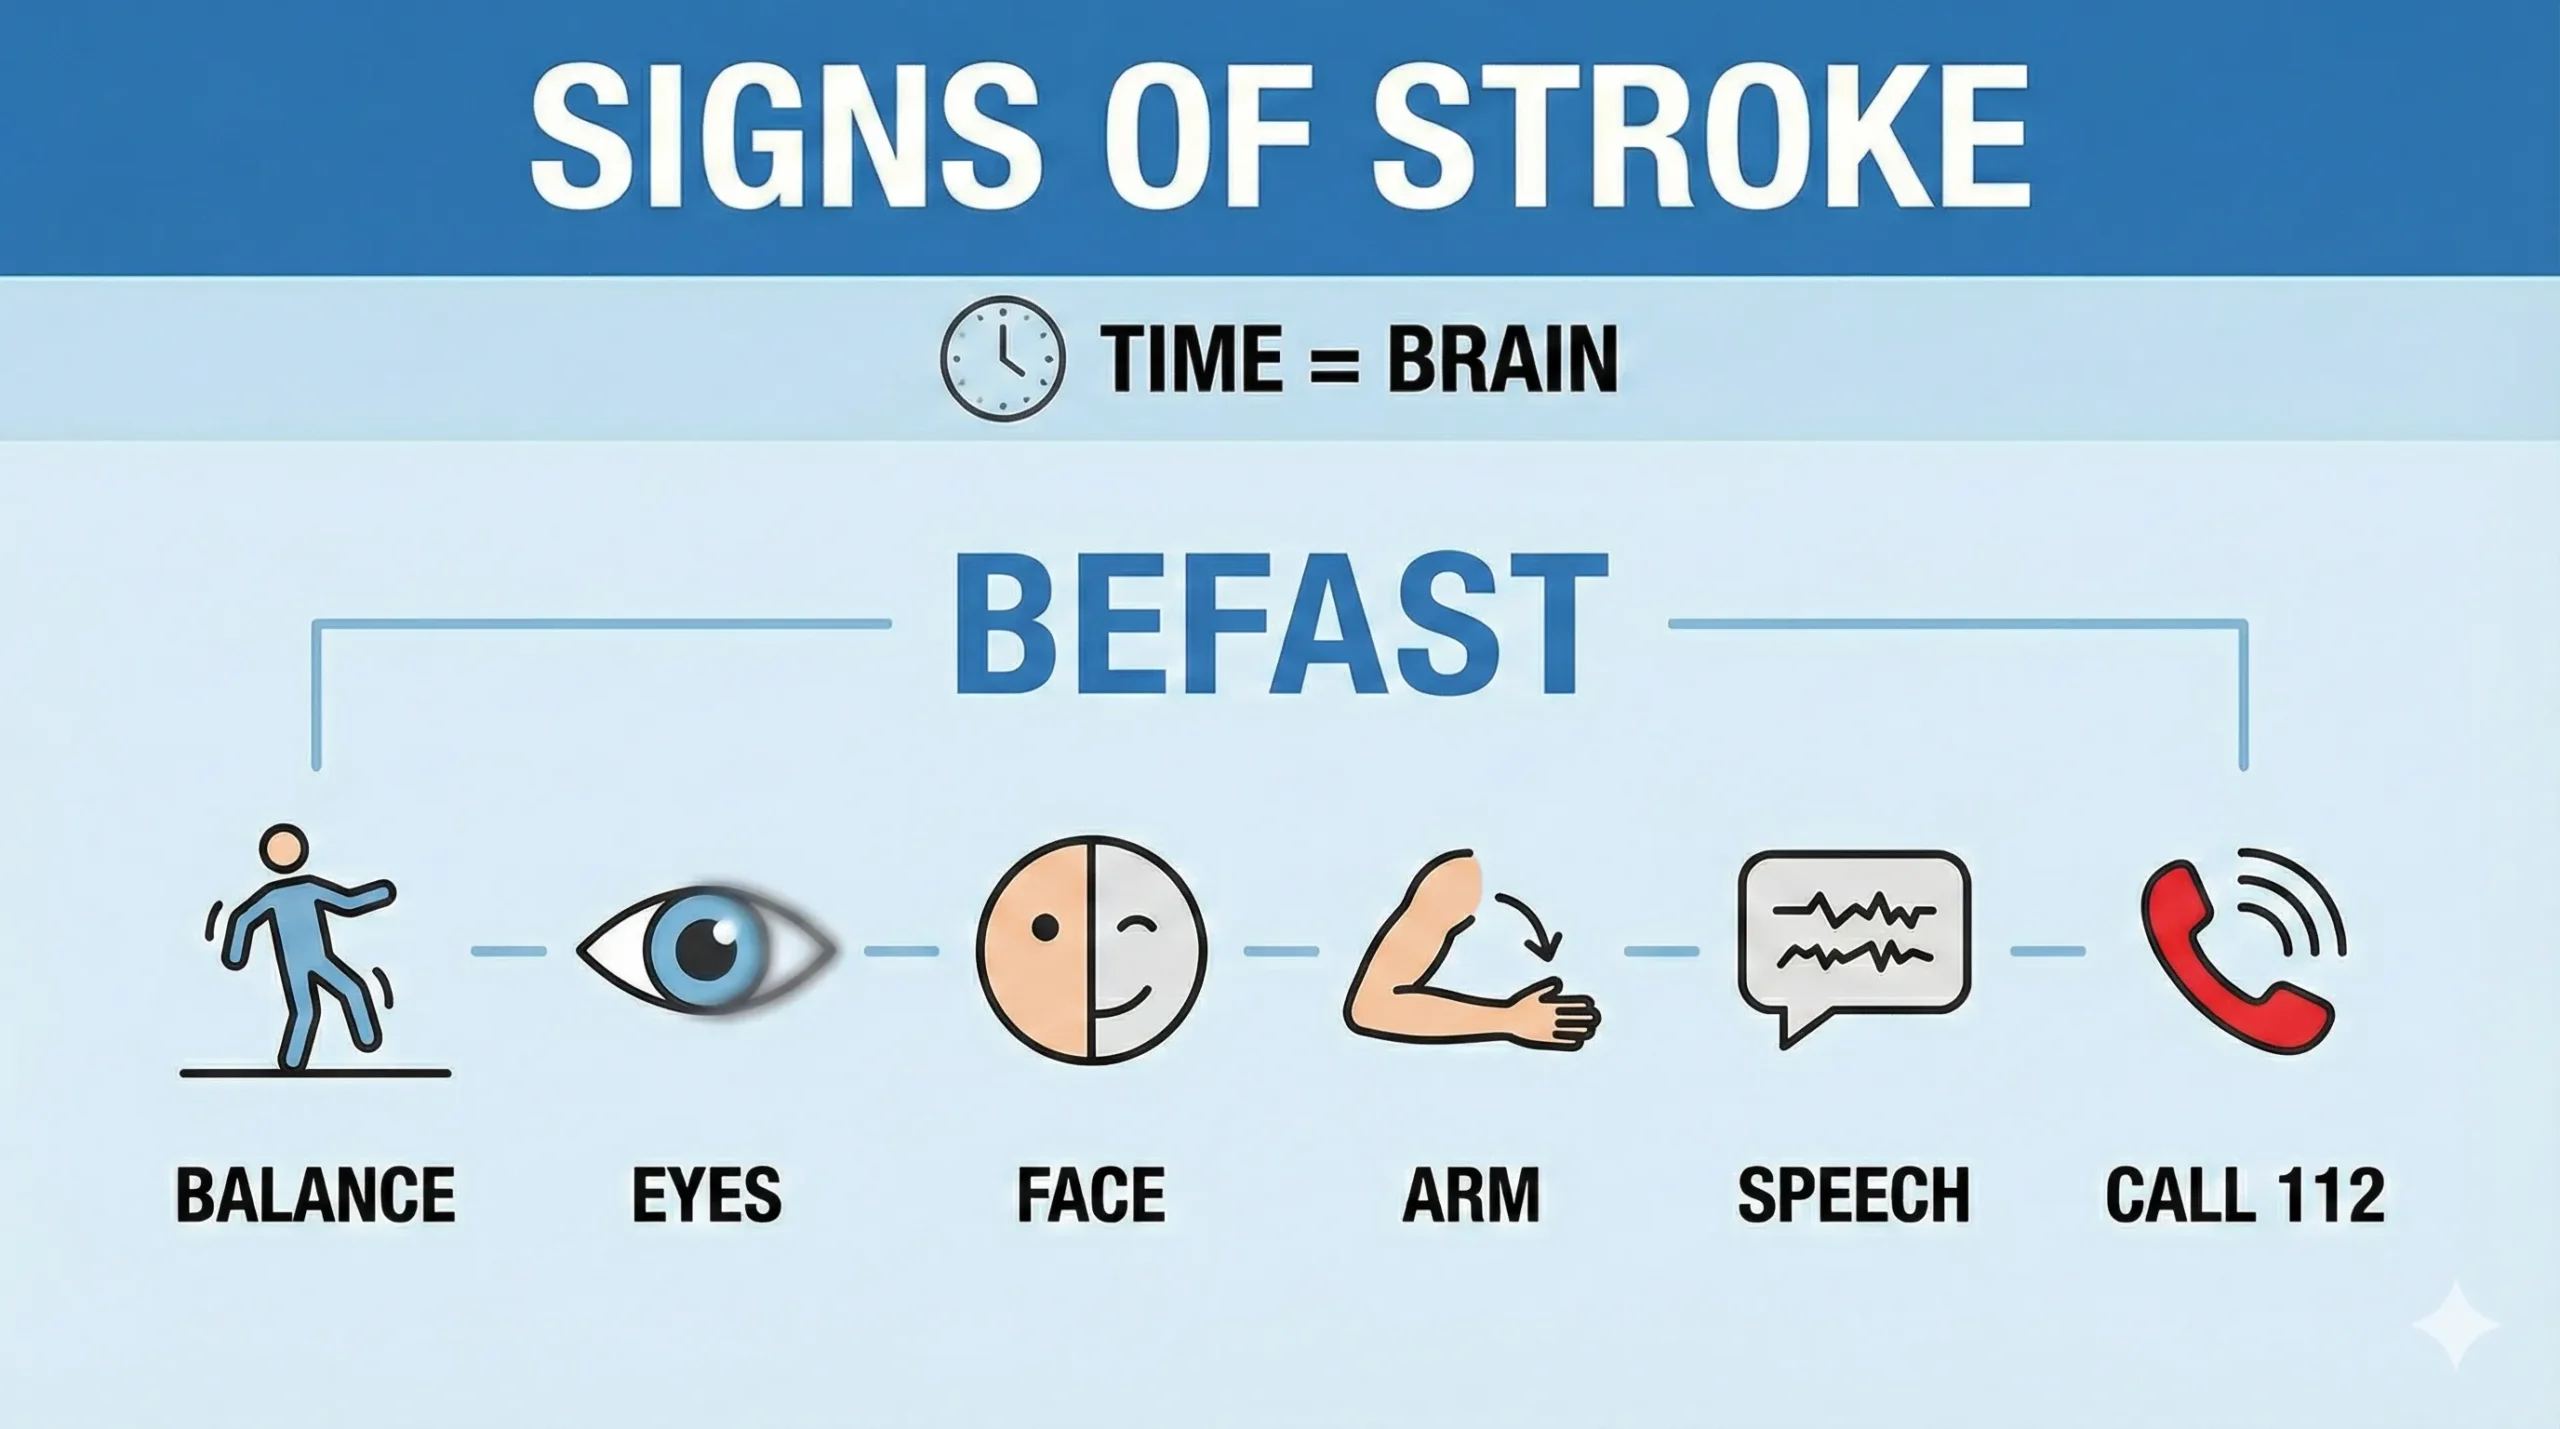
Topic 6: Stroke (Cerebrovascular Accident)
6.1 Definition
A stroke is a sudden, catastrophic interruption of blood supply to a part of the brain.
- Ischaemic stroke (~85%): An artery in the brain is completely blocked by a blood clot.
- Haemorrhagic stroke (~15%): An artery bursts and bleeds heavily into or around the brain, creating crushing pressure.
Without fresh blood, brain cells begin dying within minutes. The medical mantra is "TIME IS BRAIN."
6.2 Risk Factors
Hypertension (high blood pressure) is the biggest risk factor — it is incredibly common and often undiagnosed in Uganda. Other risks include Diabetes, high cholesterol, smoking, excessive alcohol, heart arrhythmias (like Atrial Fibrillation), Sickle Cell Disease, obesity, physical inactivity, family history, and previous strokes.
🧠 Recognising Stroke — The FAST Test
If you suspect a stroke, perform this rapid test immediately:
- F — Face: Ask the person to smile. Does one side of their face droop downwards?
- A — Arms: Ask them to raise both arms in front of them. Does one arm drift downward, or can they not lift it at all? (Look for sudden weakness or numbness on one side of the body).
- S — Speech: Ask them to repeat a simple, normal sentence ("The sky is blue"). Is their speech slurred, strange, or can they not understand what you are saying?
- T — Time: If you see ANY ONE of these signs, it is TIME to call for emergency help immediately. Note the exact time the symptoms first started!
Other Sudden Signs of Stroke
- Sudden weakness or numbness of one complete side of the body (face, arm, leg).
- Sudden severe confusion, trouble speaking or understanding language.
- Sudden trouble seeing in one or both eyes (vision goes black or blurred).
- Sudden trouble walking, severe dizziness, loss of balance or coordination.
- Sudden, inexplicably severe headache "like a bolt of lightning from the blue" (highly indicative of a bleeding Haemorrhagic stroke).
6.4 First Aid Management
- Act FAST — arrange urgent transport immediately. Every passing minute delays hospital treatment and permanently increases brain damage.
- Record the EXACT TIME the symptoms started. (This is critical because doctors only have a very short window of a few hours to give clot-busting drugs. If they don't know the time, they cannot give the drug safely).
- Lay the casualty down with their head and shoulders slightly raised (on one pillow if available) to reduce pressure inside the skull.
- Nothing by mouth (NPO): Give absolutely no food, water, or oral medicines. Explanation: Stroke heavily impairs the swallowing reflex. Giving them water will cause them to choke and aspirate fluid directly into their lungs, causing deadly pneumonia.
- If they become unconscious but are still breathing → place them in the recovery position. If possible, lay them on their affected/paralyzed side to keep the healthy lung clear. Monitor breathing continuously.
- Reassure them constantly (they may understand you even if they cannot speak); keep them warm; loosen tight clothing.
🚨 What NOT To Do
- Do NOT give Aspirin! You do not know if they are having a bleeding (haemorrhagic) stroke. If their brain is bleeding, Aspirin will thin the blood and cause them to bleed to death inside their skull.
- Do NOT "wait and see" if they get better. Even if symptoms disappear quickly (a TIA or "mini-stroke"), it is a massive warning sign that a full, fatal stroke is coming soon.
Topic 7: Poisoning
7.1 Definition & Background
Poisoning is injury or illness caused by exposure to a harmful substance. A poison is any substance which, when taken into the body in sufficient quantities, can cause severe injury to health or completely destroy life. It can be taken either accidentally (children) or intentionally (suicide attempts).
How Poisons Enter the Body
- Ingestion (Swallowing): The most common route. By eating or drinking a poisonous substance, it enters the circulatory system through the walls of the stomach and intestines.
- Inhalation (Breathing in): Inhaling toxic fumes, gases (like Carbon Monoxide), or smoke from burning poisonous substances into the lungs.
- Injection: Introduced directly into the bloodstream or tissues via needles, or venomous bites/stings (e.g., snake bites).
- Absorption (Skin Contact): A strong acid or agricultural spray (like organophosphate pesticides) comes into contact with the skin and is absorbed directly into the blood.
Effects of Poisons on Our Bodies
When poisons reach inside the body, they cause massive destruction in various ways:
- Central Nervous System (CNS) Depression: Once in the bloodstream, they suppress the brain, preventing vital activities like breathing, causing the patient to stop breathing and die.
- Heart & Vital Organs: They affect the electrical action of the heart causing deadly arrhythmias.
- Oxygen Distribution: Toxins like Carbon Monoxide bind to red blood cells, preventing them from carrying adequate oxygen to the tissues, leading to suffocation at the cellular level.
- Brain Irritation: When poisons reach the brain, the person may suffer violent convulsions or become delirious/hallucinate.
- Gastrointestinal Tract Damage: Swallowed poisons affect the food passages directly, causing severe vomiting, violent abdominal pain, and explosive diarrhea.
- Corrosive Burns: If a person swallows a corrosive poison (strong acid or alkali), it literally burns and destroys the lips, mouth, throat, and the whole food passage.
- Organ Failure: An overload of poison will overwhelm and completely damage the body’s poison filters — the liver and the kidneys.
7.2 Common Types of Poisoning in Uganda
A. Food Poisoning
Foodborne illness caused by consuming contaminated food or beverages. Contamination occurs due to harmful bacteria, viruses, parasites, or toxins.
- Bacterial: Salmonella, E. coli, Listeria. Due to improper cooking, poor refrigeration, and bad hygiene.
- Viral: Rotavirus, Hepatitis A. Usually through improper hand hygiene by food handlers.
- Parasitic: Giardia, Cryptosporidium. From raw/undercooked meat or dirty water.
- Toxins/Chemicals: Bacteria like Staphylococcus aureus leave toxins in food. Chemical contaminants include pesticide residue on unwashed fruits.
- Symptoms: Nausea, vomiting, severe abdominal pain, explosive diarrhea, bloody stools. Systemic symptoms include fever, muscle aches, fatigue, and sometimes shock from dehydration.
- Treatment: Give plenty of fluids (ORS) to prevent fatal dehydration. Collect vomitus for lab examination. Do not give anti-diarrheal drugs immediately (let the body flush the bacteria).
- Prevention: Safe food handling, strict handwashing, proper cooking/storage temps, and avoiding cross-contamination (using different boards for raw meat and veg).
B. Alcohol Poisoning
A severe, potentially fatal condition when blood alcohol concentration rises to toxic levels, usually from binge drinking large amounts in a short period. Alcohol is a CNS depressant.
- Symptoms: Confusion, disorientation, severe agitation, slow/irregular breathing, pale/bluish skin, severe vomiting, hypothermia, seizures, and progressing to respiratory failure or cardiac arrest.
- First Aid: Call for emergency help. Do NOT leave the person alone. Place them strictly in the recovery position so they do not choke on their own vomit. Monitor breathing closely; be prepared to do CPR.
- Complications: Brain damage from hypoxia, liver damage, choking death.
C. Drug Poisoning (Overdose)
Harmful effects caused by excessive amounts of medication, accidental overdoses, intentional self-harm (suicide), or dangerous interactions between drugs.
- CNS Symptoms: Confusion, drowsiness, coma, seizures, hallucinations.
- Cardiovascular Symptoms: Rapid/irregular heartbeat, very high/low blood pressure, chest pain.
- Respiratory Symptoms: Shallow, slow, or labored breathing leading to respiratory failure.
- Treatment: If conscious, place comfortably and quickly ask exactly what they took and how much. Keep empty pill bottles for the doctor. Monitor vitals. Refer immediately.
D. Industrial / Agricultural Poisoning
Exposure to hazardous substances in work environments (chemicals, heavy metals, biological agents).
- Chemicals: Solvents, agricultural pesticides (Organophosphates), acids, alkalis, toxic gases (Ammonia, Carbon monoxide).
- Heavy Metals: Lead, mercury, cadmium (accumulate over time causing chronic organ failure).
- Symptoms (Acute): Shortness of breath, severe nausea/vomiting, dizziness, skin rashes/burns, migraines.
- Symptoms (Chronic): Extreme fatigue, memory loss, chronic lung problems, cancer.
🚨 CLASSIC EXAM FINDING: Organophosphate Poisoning
Agricultural pesticides are extremely common in suicides and accidental farmer poisonings in Uganda. Memorize the SLUDGE signs:
- Salivation (drooling)
- Lacrimation (crying/tears)
- Urination (loss of bladder control)
- Defecation (diarrhea)
- GI cramps (stomach pain)
- Emesis (vomiting)
Plus: Pinpoint (tiny) pupils, severe sweating, muscle twitching, progressing to coma and respiratory failure.
7.4 General Aims & Treatment for Poisoning
Aims of First Aid: Maintain ABCs (Airway, Breathing, Circulation), identify the type of poison, obtain medical aid rapidly, remove contaminated clothing, and remove the casualty from further danger.
General Rules for Swallowed Poisons:
- Get medical aid as soon as possible (this can become a medico-legal case!).
- Protect yourself first — wear gloves, do not touch the poison.
- Keep any container, pill bottle, or leaf which you think might help doctors identify the poison.
- Do not throw away the vomitus; keep a sample for laboratory examination.
- Check the lips for signs of chemical burning. DO NOT induce vomiting if they swallowed a corrosive acid or alkali! (Vomiting brings the burning chemical back up the throat, causing double the damage and risking the chemical spilling into the lungs).
- If the casualty is conscious and swallowed a non-corrosive substance, some guidelines suggest giving fluids to dilute it, but modern protocols prefer rapid transport without oral fluids unless directed by a doctor. Give soothing drinks (like milk or egg white) only if specifically trained/directed for certain corrosives to coat the stomach.
- If the casualty is unconscious, place them in a semi-prone (recovery) position with the head turned to one side to prevent choking on vomit. Watch their breathing continuously.
- Start artificial respiration if necessary (use a pocket mask, NOT bare mouth-to-mouth if poison is on their lips!).
- Keep the casualty warm, treat for shock, and loosen tight clothing.
Specific Poisoning Management
- Acid Poisoning (e.g., Battery acid): Rinse affected skin areas with copious water for 20 mins. Do NOT induce vomiting. For ingestion, some traditional texts suggest giving an alkaline like sodium bicarbonate to counteract, but modern emergency medicine strongly prefers giving nothing by mouth and rushing to the hospital to avoid chemical reactions releasing massive heat in the stomach. Keep calm and transport.
- Alkali Poisoning (e.g., Bleach/Lye): Rinse skin with huge amounts of water. If ingested, do NOT induce vomiting. Traditional first aid suggests small sips of water or milk to dilute, or a weak acid like diluted lime juice, but rapid transport is the absolute safest priority.
- Mercury Poisoning (Liquid mercury): Isolate the area. Do not touch with bare hands (use gloves/barrier). Ventilate the room immediately by opening windows to let the toxic vapor disperse. Call emergency services for proper cleanup. Seek medical attention immediately.
- Opium / Narcotic Overdose (e.g., Heroin, strong painkillers): The drug stops the brain's breathing center. If unconscious with slow/no breathing, call EMS immediately. Do not induce vomiting. Put in recovery position if breathing. Start CPR if breathing stops. (Hospital will administer Naloxone as an antidote).
Prevention of Poisoning
- All medicine bottles and agricultural chemicals should be strictly labeled. Unlabeled medicines must be destroyed.
- Toxic medicines must clearly indicate the word "POISON" (often with a skull and crossbones) and be kept under lock and key.
- Always read the label 3 times before giving any medication.
- All poisonous substances (including bleach, paraffin) MUST be kept strictly out of the reach of children.
- Never store kerosene in empty soda or water bottles!
Topic 8: Heat Stroke & Heat Exhaustion
Heat-related illnesses form a spectrum of severity, usually resulting from exposure to high environmental temperatures, high humidity, dehydration, and heavy physical work in the sun.
Progression: 1. Heat Cramps (mildest) → 2. Heat Exhaustion (moderate) → 3. Heat Stroke (highly life-threatening).
8.1 Heat Cramps
- Painful muscle cramps or spasms (usually in the legs or abdomen) occurring after heavy sweating and physical exertion in the heat. The body loses salt and water.
- First aid: Stop the activity, rest in a cool shaded place, gently stretch and massage the cramping muscle, give fluids (water, ORS, or sports drinks). Avoid giving concentrated salt tablets.
8.2 Heat Exhaustion
Causes: Heavy sweating in hot/humid conditions leading to massive loss of water AND salts. Very common in farmers, builders, athletes, and boda boda riders working under the midday sun without drinking enough fluids.
Signs and Symptoms:
- Heavy, profuse sweating; skin feels cool, pale, and clammy (moist). (The body's cooling system is still working, trying desperately to cool down).
- Severe weakness, extreme tiredness, dizziness, and headache.
- Nausea, vomiting, and muscle cramps.
- Faintness when trying to stand up (blood pressure is dropping).
- Body temperature is normal or only slightly raised.
First Aid Management:
- Move the casualty immediately to a cool, shaded, and well-ventilated place.
- Loosen and remove any excess heavy clothing.
- Lay them down flat and raise their legs slightly to prevent fainting/shock.
- Cool the skin: Apply cool wet cloths or sponges to their skin, fan them vigorously, or spray them with cool water.
- Give them small, frequent sips of cool water or ORS (about 100–120 ml every 15 minutes if they are fully awake). Do not let them gulp it, as they will vomit.
- They should improve within 30 minutes. If they do not improve, begin vomiting, or their consciousness level drops → treat it as Heat Stroke and refer urgently!
8.3 Heat Stroke (A Massive Emergency)
Definition: A highly life-threatening emergency in which the body's internal temperature-regulating system completely FAILS. The body temperature rises dangerously high (≥ 40°C / 104°F), cooking the brain and organs.
Two Types: Classic (occurs in hot weather, usually affecting the elderly or chronically ill) and Exertional (strenuous exercise in extreme heat, like soldiers or athletes).
Signs and Symptoms:
- Very high body temperature.
- The skin is HOT, RED, and DRY (or only slightly moist). Sweating has completely stopped because the brain's thermostat has failed!
- Severe confusion, extreme agitation, staggering, bizarre combative behaviour, slurred speech.
- Pounding headache, dizziness, nausea/vomiting.
- Rapid, incredibly strong bounding pulse; rapid, shallow breathing.
- Violent seizures (fits), leading rapidly to collapse and coma.
First Aid Management:
- Call for emergency help / arrange URGENT transport immediately. Heat stroke kills quickly.
- Move to a cool place. Remove as much outer clothing as possible.
- Cool the body RAPIDLY and continuously:
- Best method: Immerse the body (up to the neck) in cold water if a tub is feasible, OR douse and spray them with cold water continuously.
- Alternative: Wrap them completely in a cold wet sheet and keep pouring cold water over the sheet while fanning them vigorously to force evaporation.
- Apply ice packs or cold packs to the neck, armpits, and groin (where large blood vessels are close to the surface, cooling the blood rapidly).
- Continue this aggressive cooling until their temperature falls to about 38°C, or their clinical state improves. (If you have no thermometer, cool them aggressively for ~20 minutes).
- If they are conscious and alert: give sips of cool water. If they are drowsy or confused — give absolutely nothing by mouth (choking risk).
- If unconscious but breathing → place in the recovery position, monitor breathing constantly; perform CPR if breathing stops.
- Even if they completely recover at the scene, they MUST be referred to a hospital for review — severe internal organ damage can follow hours later.
| Feature | HEAT EXHAUSTION | HEAT STROKE |
|---|---|---|
| Severity | Moderate | LIFE-THREATENING EMERGENCY |
| Skin | Cool, pale, CLAMMY, heavy sweating | HOT, RED, DRY (or slightly moist) |
| Temperature | Normal or slightly raised | Very high (≥ 40°C) |
| Consciousness | Dizzy, weak but alert | Confused, bizarre behavior, seizures, coma |
| Sweating | Yes (The body is still trying to cool itself) | May have completely stopped (System failure) |
| First Aid Action | Rest, fluids, gentle cooling — improves in 30 min | RAPID aggressive cooling + Urgent hospital transport |
Topic 9: Other Common Medical Emergencies
9.1 Seizures / Convulsions
Sudden, uncontrolled electrical activity in the brain causing violent jerking movements, loss of consciousness, incontinence, and tongue biting. In Uganda, always heavily suspect severe Malaria as the cause in children! Other causes: hypoglycaemia, meningitis, head injury, or eclampsia in pregnant women.
- First Aid: Protect from injury (move hard objects, cushion the head). Note the exact time it started. Do NOT restrain them. Do NOT put spoons or cloths in their mouth. When the fit stops, place in the recovery position. Refer urgently if: the fit lasts > 5 minutes, repeats without waking up, it is their first-ever fit, they are pregnant, diabetic, or a child with a high fever.
9.2 Febrile Convulsions (Children 6 months–5 years)
A convulsion triggered strictly by a rapid rise in body temperature (fever), often from Malaria or severe respiratory infections. Usually brief and self-limiting.
- First Aid: Protect the child from injury as above. Actively cool the child (remove heavy blankets/sweaters, use tepid sponging, give paracetamol syrup if conscious). Place in recovery position after, and refer immediately for cause-finding (like a Malaria RDT test).
9.3 Anaphylaxis (Severe Allergic Reaction)
A severe, incredibly rapid allergic reaction to drugs (Penicillin), bee/wasp stings, or certain foods (peanuts). Signs include massive swelling of the face/lips/tongue, hives, severe wheezing/stridor, hoarse voice, crashing blood pressure, and collapse.
- First Aid: Call for help urgently. Lay flat with legs raised (or sit up ONLY if breathing is heavily impaired). The only life-saving treatment is Adrenaline (Epinephrine) 0.5 mg IM into the anterolateral thigh — repeat every 5–10 mins as needed per clinical guidelines. Referral is mandatory!
9.5 Hyperventilation (Anxiety/Panic)
Rapid over-breathing, often from extreme anxiety or panic. Signs: fast deep breathing, extreme dizziness, tingling/numbness in fingers and lips, chest tightness, feeling of suffocation.
- First Aid: First, rule out asthma or a heart attack! Once confirmed as anxiety, offer calm, firm reassurance. Take the casualty to a quiet place. Coach them to breathe slowly with you (in for 4 seconds, out for 4 seconds). Do NOT use a paper bag (modern guidelines reject this due to hypoxia risks). Refer if the cause is unclear.
9.6 Acute Abdominal Emergencies
Conditions like acute appendicitis, intestinal obstruction, perforated ulcers, or ectopic pregnancy. Red flags: Worsening pain localising to the lower right abdomen, a rigid "board-like" stomach, vomiting, inability to pass gas/stool, or fainting in a woman of child-bearing age (huge sign of ectopic internal bleeding!).
- First Aid: Give absolutely NOTHING by mouth (NPO). Rest, monitor vitals, arrange urgent surgical referral. Do NOT give strong painkillers that hide the symptoms from the surgeon, and NEVER give laxatives.
9.7 Severe Malaria (Ugandan Context)
In Uganda, malaria is a leading cause of emergency illness. Think of it in ANY case of fever, convulsions, confusion, severe anaemia, or "flu-like" illness. Danger signs: Impaired consciousness, violent convulsions, severe paleness (anaemia), jaundice (yellow eyes), dark coca-cola coloured urine, extreme weakness, and breathing difficulty.
- Action: Refer urgently. Facility management involves testing (RDT), IV Artesunate, treating convulsions with diazepam, correcting low sugar, and giving fluids very carefully.
9.8 Suffocation
Suffocation results when fresh air is prevented from reaching the air passages by an external physical obstruction. Causes include a plastic bag tied over the head, a soft pillow pressed over the face, or falling face-first into loose sand. A baby may easily be suffocated by simply lying face down on a soft pillow or cushion.
General Signs and Symptoms:
- Severe difficulty in breathing. The rate and depth of breathing massively increases as they fight for air.
- Breathing may become incredibly noisy, presenting with loud snoring or gurgling (a low bubbling sound).
- Possible frothing at the mouth.
- Cyanosis: Deep blueness of the face, lips, and fingernails due to oxygen starvation.
- Severe confusion, extreme panic, and a rapid lowering of the level of responsiveness.
- Possible unconsciousness, and eventually, breathing may stop completely.
Aim of First Aid: Restore the supply of fresh air to the casualty instantly and seek medical aid.
Management:
- Immediately remove any obstruction (pull off the plastic bag, remove the pillow) or move the casualty to fresh air.
- If the casualty is conscious and breathing: reassure them constantly and observe their breathing carefully.
- If the casualty is unconscious: open the airway (head-tilt, chin-lift) and check breathing for 10 seconds.
- Complete the ABC of resuscitation if required (start CPR if they are not breathing).
- If they are unconscious but breathing normally, place the casualty safely in the recovery position.
- Seek medical aid immediately. If in any doubt about their recovering condition, arrange for moving them to the hospital, as brain damage from suffocation can be delayed.
📝 Quick Revision Summary (Exam Points)
| Emergency | KEY Action to Memorize |
|---|---|
| Fainting | Lay flat, raise legs 30cm, fresh air, sit up gradually. |
| Hypoglycaemia | Give fast Sugar NOW (15g), repeat in 15 min. If unconscious → IV dextrose/glucagon, give strictly NPO (nothing by mouth). |
| Hyperglycaemia | Give plain water + URGENT hospital referral (treats DKA). |
| Asthma attack | Sit UPRIGHT leaning forward, Salbutamol 4 puffs every 4 min, NEVER lay them flat. |
| Chest pain (Heart Attack) | Sit semi-reclined, Aspirin 300 mg chewed (if appropriate), calm them, urgent transport. |
| Stroke | Use FAST test + note exact TIME of onset, NPO, give NO aspirin, urgent transport. |
| Poisoning | NO vomiting induction for corrosives, identify the poison, rinse skin/eyes 15+ mins, recovery position if unconscious. |
| Heat exhaustion | Move to cool place, lie flat, sips of fluid, cool wet cloths. |
| Heat stroke | EMERGENCY — Rapid aggressive cooling to 38°C, NPO if drowsy, urgent transport. |
| Seizure | Protect from injury, put NOTHING in mouth, note time, recovery position after, refer if > 5 min. |
Golden rule for ALL medical emergencies: Danger → Response → Airway → Breathing → Circulation → Call for help → Reassure → Refer.
Good information
Thanks for the good and arranged notes🙏👍
this is so helpful thank you
This notes is helping me a lot thank you.
Great!
l loved how precise it’s to point.
thanks
so helpful