Midwives Revision

Reproductive Health

Gender Based Violence (GBV)

Gender Based Violence (GBV)

Gender based violence is any act that results in physical, sexual or psychological harm or suffering to women, men and children.


Key terms related to Gender-based Violence

1. Gender: Gender refers to the social and cultural expectations, roles, and behaviors assigned to men and women, boys and girls in a society. Unlike sex, which is biological, gender can vary greatly across different societies.

  • Example: In many societies, it is more common for men to hold leadership positions than women, illustrating a gender role.

2. Gender-based Violence: This includes any act that causes physical, sexual, or psychological harm or suffering to women, men, and children. It can occur in public or private and includes threats and coercion.

  • Example: Domestic abuse, where a partner uses physical or emotional harm to control the other, is a form of gender-based violence.

3. Violence Against Women: This refers to any act of gender-based violence that harms or is likely to harm women and girls, whether in private or public. It includes sexual violence.

  • Example: Rape and sexual assault are forms of violence against women.

4. Sexual Violence, Exploitation, and Abuse: This includes any act, attempt, or threat of a sexual nature.

  • Example: Forcing someone into sexual acts against their will is sexual violence.

5. Gender Equality: This is the state where men and women have equal rights, opportunities, and access to resources.

  • Example: Ensuring that both men and women have equal access to education and job opportunities.

6. Gender Blind: A policy or plan that does not address relevant gender issues.

  • Example: A workplace policy that does not consider the different needs of male and female employees, such as maternity leave.

7. Gender Responsiveness: A policy or plan with strategies to reduce inequality and ensure equal benefits for all genders.

  • Example: A healthcare program that ensures both men and women have equal access to medical services.

8. Sexual and Gender-based Violence: This is a serious form of discrimination, particularly against women and children, and violates human rights. It is both a public health problem and a human rights issue.

  • Example: Sexual harassment in the workplace is a form of sexual and gender-based violence.

9. Sex: This refers to the biological characteristics of males and females, limited to physiological reproductive functions.

  • Example: Being born male or female is determined by biological sex.

10. Violence: Any act that causes injury, harm, intimidation, fear, damage, or humiliation to a person. It can include emotional, social, and economic force or pressure.

  • Example: Threatening someone with a weapon or physically assaulting them is violence.

11. Sex Typing: The differential treatment of people based on their biological sex.

  • Example: Assigning certain jobs only to men or women based on their sex.

12. Gender Equity: Ensuring that women and men, boys and girls have equal opportunities to receive services that are accessible to all.

  • Example: Providing equal educational opportunities for both boys and girls.

13. Gender Sensitive: Being aware that women and men have different roles and needs, and planning accordingly.

  • Example: Designing a workplace policy that considers the different needs of male and female employees.

14. Gender Neutrality: Planning for men and women without considering their different needs and roles, which can be ineffective.

  • Example: A healthcare service that does not consider the specific needs of women, such as prenatal care.

15. Gender Roles: The tasks and responsibilities that society assigns to women and men, girls and boys. These roles can change over time and across different societies.

  • Example: In some cultures, women are expected to be primary caregivers, while men are expected to be breadwinners.

16. Coercion: Forcing someone to engage in behavior against their will using threats, manipulation, or economic power.

  • Example: Threatening to harm someone if they do not comply with your demands.

17. Sexual Preference/Orientation: A person’s preference for partners of the same or opposite sex.

  • Example: Being heterosexual (attracted to the opposite sex) or homosexual (attracted to the same sex).

18. Gender Role Stereotype: Socially determined beliefs about what gender roles should be.

  • Example: The belief that girls should be obedient and boys should be brave.

Forms of Violence in Uganda

Domestic Violence

  • Wife Battering: Physical abuse of wives by their husbands.
  • Oppression: Controlling behaviors that limit a partner’s freedom and autonomy.
  • Intimidation: Using threats and fear to control a partner.
  • Emotional Abuse: Verbal insults, humiliation, and constant criticism.
  • Economic Abuse: Controlling a partner’s access to financial resources.
  • Isolation: Preventing a partner from interacting with friends, family, or community.

Sexual Abuse

  • Rape: Forced sexual intercourse without consent.
  • Defilement: Sexual abuse of minors.
  • Incest: Sexual relations between family members.
  • Sexual Exploitation: Taking advantage of someone’s vulnerability for sexual purposes.
  • Sexual Harassment: Unwanted sexual advances, requests for sexual favors, and other verbal or physical harassment of a sexual nature.

Harmful Cultural Practices

  • Female Genital Mutilation (FGM): Partial or total removal of external female genitalia for non-medical reasons.
  • Widow Inheritance: Forcing a widow to marry a relative of her deceased husband.
  • Bride Price: Payment made by the groom’s family to the bride’s family, often leading to the commodification of women.
  • Child Marriage: Marrying off young girls, often for economic reasons or cultural beliefs.

Forced Marriages

  • Economic Purposes: Marrying off girls for financial gain, such as bride price.
  • Cultural Beliefs: The belief that girls are destined for marriage rather than education.
  • Social Pressure: Families forcing marriages to maintain social status or avoid stigma.
  • Lack of Education: Limited access to education leading to early marriage as the only perceived option.

Other Forms of Violence

  • Sexual Harassment and Intimidation: Occurring in workplaces, religious institutions, and schools.
  • Coercion: Forcing someone to act against their will through threats or manipulation.
  • Arbitrary Deprivation of Liberty: Unjustified detention or restriction of movement.
  • Belief in Large Families: Pressure to have many children, leading to health risks and economic strain.
  • Forced Sex: Men having non-consensual sex with their partners.
  • Institutional Violence: Violence perpetrated or condoned by institutions such as the government or religious bodies.

Settings Where Gender-Based Violence Can Occur

Family

  • Battering of Women: Physical abuse within the home.
  • Sexual Abuse of Children: Incest and other forms of sexual abuse within the family.
  • Emotional Abuse: Verbal and psychological harm inflicted by family members.
  • Neglect: Failure to provide basic needs such as food, shelter, and healthcare.

Community

  • Sexual Abuse: Rape, defilement, and other forms of sexual violence.
  • Sexual Harassment and Intimidation: Unwanted sexual advances and threats.
  • Trafficking: Exploitation for labor or sexual purposes.
  • Forced Prostitution: Coercing individuals into sex work.
  • Mob Violence: Community-based violence targeting individuals or groups.

State

  • Poorly Drafted or Unenforceable Laws: Legal frameworks that do not adequately protect victims.
  • Violence by Law Enforcement: Abuse of power by police and other authorities.
  • Lack of Facilities: Inadequate healthcare and support services for victims.
  • Education: Insufficient education on prevention and treatment of violence.
  • Corruption: Officials taking bribes to ignore or condone violence.

Predisposing Factors of Sexual and Gender-Based Violence

Socio-Economic Factors

  • Low Socio-Economic Status: Poverty and lack of education increasing vulnerability.
  • Women’s Low Status: Cultural and social norms that devalue women.
  • Dependence on Men: Economic and decision-making dependence.

Cultural Factors

  • Infertility: Blaming and abusing women for not being able to have children.
  • Fear of Reporting: Victims afraid to report due to lack of support and fear of reprisal.
  • Gender Roles: Traditional roles that limit women’s autonomy and expose them to violence.
  • Harmful Practices: FGM, early marriage, and widow inheritance.

Health and Disability Factors

  • Physical and Mental Disabilities: Increased risk of abuse and stigmatization.
  • Ill Health: Especially from HIV/AIDS, leading to vulnerability.
  • Poverty: Economic hardship leading to exploitation.
  • Idleness: Unemployment and lack of productive activities leading to substance abuse.

Environmental Factors

  • Abduction: Kidnapping leading to sexual abuse and exploitation.
  • Land Wrangle: Property disputes leading to violence against women.
  • Conflict: War and displacement increasing vulnerability.
  • Poor Role Modeling: Lack of positive examples for children.

Risk Groups for Sexual and Gender-Based Violence

Vulnerable Populations

  • All Children and Women: Higher risk due to power imbalances and cultural norms.
  • Adolescents: Vulnerable to peer pressure and exploitation.
  • Displaced Persons: Including refugees and internally displaced people.
  • People with Disabilities: Increased risk of abuse and neglect.
  • Prisoners: Vulnerable to abuse by authorities and other inmates.
  • Men: Often reluctant to report violence due to fear of stigma.
  • Pregnant Mothers: Vulnerable to domestic violence and lack of support.

Specific Risk Factors

  • Economic Dependence: Lack of financial independence.
  • Social Isolation: Lack of support networks.
  • Cultural Norms: Beliefs that justify violence against women.
  • Legal Gaps: Inadequate laws and enforcement.
  • Health Issues: Physical and mental health problems increasing vulnerability.
  • Education: Lack of awareness and education on rights and protections.

Domestic Violence

This term specifically refers to violence that occurs within the domestic sphere, typically between individuals who are related by blood or intimacy. It includes intimate partner violence (IPV) and can also encompass violence against children, siblings, or grandparents within the same household. Domestic violence is a subset of GBV and is one of the most common forms of GBV.

Domestic violence is a specific form of GBV that occurs within the family or intimate relationships, GBV is a broader concept that encompasses any form of violence directed at individuals based on their gender.

Reasons for Staying in an Abusive Relationship (1)

Reasons for Staying in an Abusive Relationship

Hope for Change:

  • Belief that the abuser will change their behavior.
  • Optimism that the relationship can improve.
  • Faith in the abuser’s promises to stop the abuse.

Total Love for the Partner:

  • Deep emotional attachment to the abuser.
  • Strong feelings of love and commitment.
  • Belief that love can conquer all problems.

Fear of Losing the Marriage:

  • Concerns about the social stigma of divorce.
  • Fear of being alone or single.
  • Worries about the impact on children and family.

Purpose of the Children:

  • Staying for the sake of the children’s well-being.
  • Belief that children need both parents.
  • Fear of disrupting the children’s lives.

Shame:

  • Embarrassment about the abuse.
  • Fear of judgment from family, friends, and society.
  • Concerns about being blamed for the abuse.

Poverty Fear of Returning the Bride Price:

  • Financial dependence on the abuser.
  • Fear of economic hardship if the relationship ends.
  • Cultural obligations to return the bride price, which can be a financial burden.

Security Purpose:

  • Dependence on the abuser for financial and physical security.
  • Fear of losing a stable home and lifestyle.
  • Belief that the abuser provides necessary protection.

Lack of Support:

  • Isolation from friends and family.
  • Lack of a support system to help leave the relationship.
  • Fear of being alone without emotional and practical support.

Cultural and Social Pressure:

  • Pressure from society to maintain the relationship.
  • Cultural beliefs that prioritize marriage and family unity.
  • Fear of being ostracized by the community.

Fear of Retaliation:

  • Fear that the abuser will become more violent if the victim tries to leave.
  • Concerns about the abuser harming the victim, children, or other family members.
  • Fear of the abuser stalking or harassing the victim after leaving.

Low Self-Esteem:

  • Belief that the victim deserves the abuse.
  • Feelings of worthlessness and inadequacy.
  • Lack of confidence in the ability to live independently.

Lack of Alternatives:

  • Limited options for housing, employment, and financial support.
  • Fear of homelessness or poverty if the relationship ends.
  • Belief that there are no better alternatives to the current situation.

Characteristics of Those Who Are Abused

Belief That Violence Gives Immediate Results:

  • The abuser believes that violence is an effective way to control and dominate the victim.
  • The abuser uses violence to achieve immediate compliance and obedience.

Insecure, Extremely Jealous, and Possessive:

  • The abuser feels threatened by the victim’s independence and relationships with others.
  • The abuser exhibits extreme jealousy and possessiveness, often accusing the victim of infidelity.

Emotionally Dependent on the Partner:

  • The abuser relies on the victim for emotional support and validation.
  • The abuser feels a strong need to control the victim to maintain emotional stability.

Denial That Their Actions Are Violent:

  • The abuser minimizes or denies the severity of their actions.
  • The abuser blames the victim for provoking the violence.
  • The abuser refuses to take responsibility for their abusive behavior.

Poor Impulse Control:

  • The abuser has difficulty managing anger and frustration.
  • The abuser acts impulsively and aggressively without considering the consequences.
  • The abuser struggles with emotional regulation and self-control.

Manipulative and Controlling:

  • The abuser uses manipulation and control tactics to maintain power over the victim.
  • The abuser isolates the victim from friends and family to increase dependence.
  • The abuser uses guilt, shame, and fear to control the victim’s behavior.

History of Abuse or Trauma:

  • The abuser may have experienced abuse or trauma in their past.
  • The abuser may repeat patterns of abuse learned from their upbringing or past relationships.
  • The abuser may have unresolved emotional issues that contribute to their abusive behavior.

Lack of Empathy:

  • The abuser shows little or no concern for the victim’s feelings and well-being.
  • The abuser is unable or unwilling to understand the impact of their actions on the victim.
  • The abuser prioritizes their own needs and desires over the victim’s.

Impacts of Sexual and Gender-Based Violence

Sexual and gender-based violence (SGBV) has profound and lasting effects on survivors, impacting their physical, mental, and social well-being. The impacts can be categorized into physical, psychological, social, and economic dimensions.

Physical Impacts

Injuries:

  • Bruises, fractures, and internal injuries.
  • Long-term physical disabilities and chronic pain.
  • Scars and disfigurement.

Sexually Transmitted Infections (STIs):

  • Increased risk of contracting STIs, including HIV/AIDS.
  • Long-term health complications from untreated STIs.
  • Stigma and discrimination associated with STIs.

Unwanted Pregnancies:

  • Risk of unsafe abortions, leading to lifelong health effects and potential death.
  • Complications during pregnancy and childbirth.
  • Emotional and financial burden of raising a child from an abusive relationship.

Chronic Health Issues:

  • Long-term health problems such as chronic pain, headaches, and gastrointestinal issues.
  • Weakened immune system and increased susceptibility to illnesses.
  • Cardiovascular problems and hypertension.

Psychological Impacts

Mental Health Issues:

  • Depression and anxiety.
  • Post-traumatic stress disorder (PTSD).
  • Suicidal thoughts and attempts.

Low Self-Esteem:

  • Feelings of worthlessness and inadequacy.
  • Loss of confidence and self-worth.
  • Difficulty trusting others and forming healthy relationships.

Trauma and Fear:

  • Constant fear and hypervigilance.
  • Nightmares and flashbacks.
  • Difficulty sleeping and concentrating.

Substance Abuse:

  • Turning to drugs or alcohol to cope with trauma.
  • Increased risk of addiction and related health problems.
  • Social and economic consequences of substance abuse.

Social Impacts

Isolation:

  • Withdrawal from social activities and relationships.
  • Loss of friends and support networks.
  • Difficulty forming new relationships due to trust issues.

Stigmatization:

  • Social judgment and blame.
  • Difficulty reintegrating into society.
  • Fear of disclosure and seeking help due to stigma.

Family Disruption:

  • Breakdown of family relationships.
  • Impact on children, including behavioral and emotional problems.
  • Difficulty maintaining stable housing and employment.

Economic Impacts

Poverty:

  • Loss of income and financial stability.
  • Difficulty finding and maintaining employment.
  • Increased dependence on social services and support.

Loss of Livelihood:

  • Difficulty pursuing education and career goals.
  • Loss of job opportunities and professional advancement.
  • Economic strain from medical expenses and legal fees.

Housing Instability:

  • Difficulty finding and maintaining safe and stable housing.
  • Risk of homelessness or living in unsafe conditions.
  • Financial burden of relocating and starting over.

Long-Term Effects

Intergenerational Trauma:

  • Impact on future generations, including increased risk of abuse and violence.
  • Cycle of violence and trauma passed down through families.
  • Long-term effects on community and societal well-being.

Community Impact:

  • Increased strain on social services and healthcare systems.
  • Economic burden on communities and societies.
  • Decreased productivity and increased social unrest.

Legal and Justice System:

  • Challenges in accessing justice and legal support.
  • Difficulty navigating the legal system and seeking redress.
  • Fear of reporting abuse due to lack of trust in the justice system.

Ways through which Sexual Gender-based Violence can be reduced in Uganda

Sexual and gender-based violence should be recognized as an important public health matter. Therefore, everyone in the community can contribute tremendously to reducing the acts of sexual gender-based violence by actively doing the following:

  1. Leaders should spearhead sensitization of communities on the impacts of sexual gender-based violence throughout the country.
  2. Reporting all acts of violence to the health centers, police, and other relevant authorities.
  3. Ensuring that those who commit these acts are punished appropriately.
  4. Some of the current measures to punish the perpetrators should be revised and made stronger to deter people from committing acts of violence.
  5. Communities should be encouraged to stop the culture of silence which hampers victims from reporting fearing the repercussions e.g. imprisonment and stigmatization.
  6. Advocacy to reduce sexual and gender-based violence must be intensified at all levels.
  7. Review the legal systems to improve the court relationship between the legal officers and the victims.
  8. Improve the relationship between the legal and other practitioners during court session.
  9. Health workers should be supported to undertake their roles to manage and care for survivors of Sexual Gender-based Violence.

Roles of leaders on SGBV in their community

The following ways can be used by leaders to fight Sexual Gender-based Violence by:

  1. Speaking out against Sexual Gender-based Violence at every opportunity for instance during community meetings, campaigns, fundraising, funerals, drinking places.
  2. Leaders should strive to act as role models by avoiding being perpetrators of SGBV.
  3. Assisting victims to get help and to see that the culprits such as defilers, rapists, men who batter their wives are reported to the police and punished appropriately.
  4. Leaders can form counseling groups to help men, children and women who are perpetrators of Sexual Gender-based Violence.

Control and prevention of Sexual Gender-based Violence

  1. Improve girl child education at all level.
  2. Reducing the high level of poor socio-economic status will in long run reduce women vulnerability to violence.
  3. Increasing awareness of women‘s rights and responsibilities related to owning property and assets.
  4. Reviewing and amending laws that safeguard women‘s rights.
  5. Strengthening nationwide/community wide efforts to challenge the widespread tolerance and acceptance of violence against women.
  6. Encouraging parents to bring up children who respect the rights of individuals as men or women, boys or girls
  7. Supporting parents to bring up their boys and girls as equal partners

Reasons Why the Community and Leaders Should Be Concerned About SGBV

Damages Social Bonds:

  • Isolation of Victims: Women and girls who are sexually abused often isolate themselves or are isolated by their families and communities, leading to a breakdown in social cohesion.
  • Community Division: The stigma and shame associated with SGBV can create divisions within communities, affecting trust and cooperation.
  • Social Exclusion: Victims may face social exclusion, further damaging community bonds and support networks.
  • Intergenerational Impact: The trauma experienced by victims can affect future generations, perpetuating a cycle of abuse and social dysfunction.

Substantial Health Burden:

  • Difficult Diagnosis and Treatment: Victims often present with vague complaints that are challenging to diagnose and treat, placing a significant burden on healthcare systems.
  • Mental Health Issues: SGBV survivors frequently suffer from mental health problems such as depression, anxiety, and post-traumatic stress disorder (PTSD), requiring long-term psychological support.
  • Physical Health Problems: Victims may experience chronic pain, sexually transmitted infections (STIs), and other physical health issues that require ongoing medical care.
  • Reproductive Health: SGBV can lead to unwanted pregnancies, unsafe abortions, and reproductive health complications, further straining healthcare resources.

Economic Loss:

  • Loss of Productivity: Victims of SGBV, due to physical injury or emotional stress, are often unable to fulfill their roles in households and workplaces, leading to economic loss.
  • Financial Burden: The cost of medical treatment, legal proceedings, and support services for victims can be substantial, placing a financial burden on households and communities.
  • Reduced Economic Contribution: In many Ugandan villages, women are key breadwinners. SGBV can significantly reduce their economic contribution, affecting family income and community development.
  • Long-Term Economic Impact: The economic repercussions of SGBV can be long-lasting, affecting future generations and hindering economic growth and development.

Legacy of Bitterness:

  • Conflict Situations: SGBV can exacerbate tensions in conflict situations, creating a legacy of bitterness and resentment towards the group from which the perpetrators came.
  • Negative Impact on Reconciliation: The bitterness and mistrust resulting from SGBV can hinder reconciliation efforts and community reconstruction, prolonging conflict and instability.
  • Cycle of Violence: The bitterness and desire for revenge can perpetuate a cycle of violence, making it difficult to achieve lasting peace and stability.
  • Community Polarization: SGBV can polarize communities, making it challenging to foster unity and cooperation.

Legal and Justice System Strain:

  • Increased Caseload: SGBV cases can overwhelm the legal and justice system, leading to delays and inefficiencies in handling other cases.
  • Resource Allocation: Addressing SGBV requires significant resources, including trained personnel, infrastructure, and support services, which can strain limited resources.
  • Public Trust: Failure to adequately address SGBV can erode public trust in the legal and justice system, undermining its effectiveness and legitimacy.

Educational Impact:

  • School Dropout: Victims of SGBV, particularly girls, may drop out of school due to trauma, stigma, or pregnancy, affecting their education and future prospects.
  • Learning Environment: SGBV can create a hostile learning environment, affecting the educational outcomes of all students.
  • Teacher-Student Relationships: SGBV can damage trust between teachers and students, making it difficult to provide a safe and supportive educational environment.

Cultural and Social Norms:

  • Perpetuation of Harmful Practices: SGBV can reinforce harmful cultural and social norms, such as gender inequality and patriarchal attitudes, perpetuating a cycle of abuse.
  • Challenge to Traditional Values: Addressing SGBV may require challenging deeply ingrained cultural and social norms, which can be met with resistance and backlash.
  • Community Values: SGBV can undermine community values of respect, dignity, and equality, affecting the overall well-being and cohesion of the community.

Roles of health workers in managing victims and addressing gender-based violence

This is important to note that health workers play instrumental roles in ensuring that families and victims of gender-based violence are professionally attended and see that the victims get justice. Therefore, the following cited are some of roles of health worker in gender-based violence management;

  1. Offering psychosocial support and counseling services to the affected families and individuals.
  2. Liaising with people and other stakeholders to see that the perpetrator (culprits) is brought to book to prevent possibility of reoccurrences.
  3. Collecting victim‘s medical information and performing required medical examination to promote continuity of care.
  4. Creating a friendly and confidential environment (shelter) where victims needs are addressed.
  5. Offering timely and appropriate referral services as needed.
  6. Establishing and promoting strict reporting of all gender-based violence related cases to responsible authority and ensure victims get fair justice.
  7. Ensuring and maintaining constant follow-up care of all affected families or victims.

Sources of Help for Victims of SGBV

Police:

  • Reporting and Investigation: Victims can report incidents of SGBV to the police, who are responsible for investigating and taking legal action against perpetrators.
  • Protection and Support: Police can provide immediate protection and support to victims, including referrals to other services.

Probation Officers:

  • Rehabilitation and Monitoring: Probation officers can monitor perpetrators and provide rehabilitation services to prevent future incidents of SGBV.
  • Victim Support: Probation officers can also support victims by ensuring that perpetrators comply with court orders and conditions of probation.

Child and Family Protection Unit:

  • Specialized Services: This unit provides specialized services for children and families affected by SGBV, including counseling, legal support, and referrals to other services.
  • Child Protection: The unit focuses on protecting children from abuse and ensuring their well-being and safety.

Local Leaders/Elders:

  • Community Support: Local leaders and elders can provide support and advocacy for victims within the community, helping to address SGBV at the local level.
  • Mediation and Reconciliation: Local leaders can facilitate mediation and reconciliation efforts to address SGBV and promote community healing.

Trusted Person or Family Members:

  • Emotional Support: Trusted individuals or family members can provide emotional support and a safe space for victims to share their experiences and seek help.
  • Practical Assistance: They can also offer practical assistance, such as helping victims access services and navigate the legal system.

Counselors:

  • Psychological Support: Counselors provide psychological support to help victims cope with the trauma of SGBV, including therapy and emotional healing.
  • Long-Term Support: Counselors can offer long-term support to help victims rebuild their lives and overcome the effects of SGBV.

Healthcare Providers:

  • Medical Care: Healthcare providers can offer medical care and treatment for physical injuries and health complications resulting from SGBV.
  • Mental Health Services: They can also provide mental health services to address the psychological impact of SGBV.

Legal Aid Services:

  • Legal Representation: Legal aid services can provide victims with legal representation and support to navigate the legal system and seek justice.
  • Advocacy: They can also advocate for victims’ rights and ensure that their voices are heard in legal proceedings.

Non-Governmental Organizations (NGOs):

  • Comprehensive Support: NGOs can offer comprehensive support services, including counseling, legal aid, and advocacy for victims of SGBV.
  • Community Outreach: NGOs can engage in community outreach and awareness campaigns to educate the public about SGBV and promote prevention efforts.

Support Groups:

  • Peer Support: Support groups can provide a safe and supportive environment for victims to share their experiences, receive peer support, and build a network of solidarity.
  • Empowerment: Support groups can empower victims to speak out against SGBV and advocate for change in their communities.

Note: In some African cultures, beating a woman or girls is part of the disciplining process; in fact some women even willingly accept to be beaten
Gender Based Violence (GBV) Read More »

hormonal Family Planning

Hormonal Methods of Family Planning

Hormonal family planning refers to the use of hormonal methods to prevent pregnancy. These methods involve the use of hormones, typically synthetic versions of those naturally produced by the body, to regulate a woman’s menstrual cycle and prevent ovulation (the release of an egg from the ovaries). By preventing ovulation, hormonal methods make it difficult for sperm to fertilize an egg and thus prevent pregnancy.

These include;

  1. Oral contraceptive pills
  2. Implants
  3. Injectable contraceptive
  4. Emergency contraceptive pills

Oral Contraceptive Pills

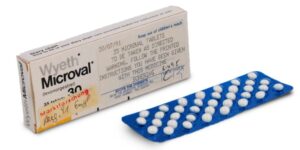
i)      Progesterone Only Pills (POP)
Examples
  • Ovrette
  • microval
  • They contain progesterone hormone
  • They are recommended for breastfeeding mothers because they do not affect/suppress milk
Modes of action
  • It acts mainly by making cervical mucus thick and viscous, thereby preventing sperm penetration
  • Endometrium becomes atrophic so blastocyst implantation is also
  • In about 2% ovulation is inhibited and 50% of women ovulate normally
Advantages
  1. Highly effective
  2. Limited related side effects
  3. Protects against unwanted pregnancy
  4. Do not affect breastfeeding
  5. May decrease menstrual cramps
  6. May improve anemia
  7. Protects against ectopic pregnancy
Contraindications
  1. Pregnancy
  2. Unexplained vaginal bleeding
  3. Recent history of breast cancer
  4. Arterial diseases
  5. Thromboembolic diseases
  6. Active hepatic diseases
  7. Hypertension
Side effects
  1. Amenorrhea
  2. Spotting
  3. Prolonged or heavy bleeding
  4. Lower abdominal pain
  5. Weight gain or lose
  6. Jaundice
  7. Nausea and vomiting
  8. Headache with blurred vision
  9. Excessive hair growth
  10. Breast fullness or tenderness
  11. High blood pressure
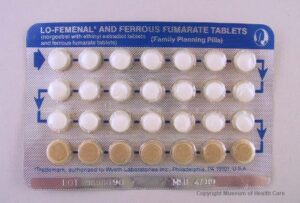
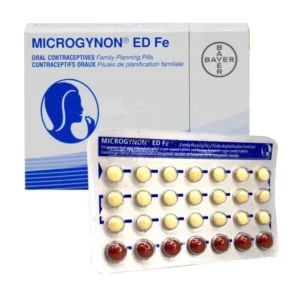
i)      Combined Oral Contraceptive Pills (COC)
  • This contains both oestrogen and It achieves effects of both hormones
  • Oestrogen suppresses ovulation and progesterone creates unfavorable conditions for egg transport and thickening of the cervical mucus to impair sperm entrance into the canal.
Examples
  • Lo-femenal
  • Pillplan (duofen)
  • Microgynon

Advantages

  1. Highly effective (99%)
  2. Protects against unwanted pregnancy
  3. It is convenient, simple to take and does not interfere with sexual intercourse
  4. Helps to correct menstrual irregularities
  5. Reduces risks of ovarian and endometrial cancers by 50%
  6. Decreased menstrual cramps
  7. Pelvic examination is not required before use
  8. Limited related side effects
  9. Quicker return of infertility
Disadvantages
  • Refer to pop Side effects
Side effects
  1. Chest pain
  2. Amenorrhea
  3. Spotting
  4. High blood pressure
  5. Nausea, dizziness & nervousness
  6. Acne
  7. Breast fullness & tenderness
  8. Depression
  9. Jaundice
  10. Headache
Implants

Types

  • Implanon ( 1 rod capsule for effective 3 years)
  • Jadelle (2 rod capsules for 5 years)
  • Norplant ( 6 rod capsules labeled for 5-7 years)

Modes of action

  1. Thickens the cervical mucus 24 hours making it difficult for the sperm to enter the uterus.
  2. It inhibits ovulation from taking place.
Advantages
  1. Very effective within 24 hours after insertion
  2. Easily reversible
  3. No delay to return to fertility after removal
  4. Make sickle cell crisis less frequent & less painful
  5. Highly effective for long term
  6. Others same as with Depo Provera
Common side effects and disadvantages
  1. Changes in menstruations
    • Spotting
    • Heavy bleeding (rare)
    • Amenorrhea
  2. Does not protect against STIs including HIV/AIDs
  3. Discomfort in the hand after insertion
  4. Overweight or weight loss
  5. Minor surgical procedure required for insertion and removal.
Indications
  1. Breast feeding post-partum mothers
  2. Adolescents
  3. Post abortion
  4. Women with SCD
  5. Women waiting surgical contraception
  6. Women on treatment e. ARVs
Contraindications
  1. Serious problems with heart or blood vessels
  2. Breast cancer
  3. Liver diseases- jaundice
  4. Pregnancy
Signs and problems that need medical attention
  • Soreness at the site of insertion
  • Capsules come out
  • Severe headache
  • Heavy bleeding twice as much and twice as long she usually bleeds
  • Pregnancy
  • Missed period after several regular period or cycles.
Injectable contraceptives
Examples
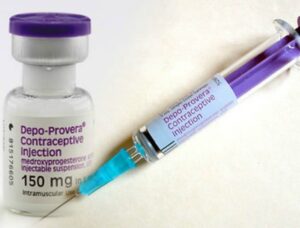
  • Depo provera 150mg
  • Injecta plan
  • Sayana press 104mg, 65ml subcutaneously
  • Noristrat 200mg intramuscularly
  • Norigynon 5mg intramuscularly

They both contain only one type of hormones, progestin

Depo Provera

Depo Provera 

Mode of action 
  • Inhibits ovulation
  • Thickens the cervical mucus making it difficult for the sperm to enter the uterus
  • It also makes the lining of the womb thinner. This makes it unlikely that a fertilized egg will be able to implant in the womb.
Indications/who can use it?
  • Breastfeeding mothers 6 weeks after delivery or immediately if not breastfeeding
  • Women requiring long term contraception
  • Known/suspected HIV positive women who need an effective FP method
  • Women with sickle cell disease
  • Women who cannot use COC due to estrogen content
  • Women awaiting surgical method of contraception
Contraindications
  • As for POP
  • Women without proven fertility unless they have HIV/AIDs
  • Pregnancy (known or suspected)
  • Liver disease (jaundice)
  • Unexplained vaginal bleeding that has not be investigated
  • Hypertension 140/90mmg and above
  • Serious problem with the heart or blood loss
  • Breast or genital malignancy (known or suspected)
  • Women with bone thinning/osteoporosis (known or suspected)
Advantages and non-contraceptive benefits
  • Very effective
  • Does not suppress lactation
  • Clients only has to remember the return dates for subsequent injection
  • Private-no one can know that the woman is on it
  • No estrogen side effects
  • Make sickle cell crisis less frequent
  • If you want to stop using it you don’t have to go back to your doctor or nurse to have it removed; you just have to wait for it to wear off.
  • It does not interfere with sex
Disadvantages and common side effects
  • Changes in menstrual bleeding
    • Spotting (common in the first 3 months)
    • Amenorrhea (often after 1st injection and after 9-12months of use)
    • Prolonged heavy vaginal bleeding during 1st 1-2 months after injection
  • Weight gain or loss
  • The injection cannot be removed once given. Any side-effects will last for more than 2-3 months, until the progesterone goes from your body.
  • Delayed return of fertility
  • Loss of lido
  • Does not protect against STI/HIV/AIDs
  • Alopecia
  • Milk headache
Signs and problems that need medical attention
  • Repeated severe headaches
  • Excessive weight gain
  • Depression
  • Prolonged abdominal pain and pain at injection site
  • Heavy bleeding per vagina twice as much and twice as long as she usually bleeds
Management
  • Medroxyprogesterone acetate depot (Depo provera) Injection 150mg deep IM into deltoid or buttock muscle
    • Do not rub the area as this increases absorption and shortens depot effect

If given after day 1-7 of menstrual cycle

  • Advise client
    • To abstain from sex or use a back-up FP method, e.g. condoms, for the first 7 days after injection
    • To return for the next dose  on a specific date 12 weeks after the injection (if the client returns more 2-4 weeks later than the date advised, rule out pregnancy before giving the next dose)
    • On likely side effects
    • To return promptly if there are any warning signs
Sayana Press

Sayana Press

  • Sayana press ® is a single-dose container with 104mg Medroxyprogesterone acetate (MPA) in 0.65ml suspension (104mg) formulated for subcutaneous
  • It is administered subcutaneously into the anterior thigh or abdomen or arm
  • The efficacy of Sayana press depends on adherence to the recommended dosage schedule of administration.
Mechanism of actions
  • Its‘ main mechanism of action is to suppress ovulation
  • It makes the endometrium unsuitable for implantation if fertilization occurs
  • It also increases the viscosity of cervical mucus making the mucus less easily penetrable to sperm.
Indications

Nearly all women can use it safely & effectively including women:-


  • Women whose partners have undergone vasectomy until vasectomy is effective
  • Have or have not had children
  • Any age including adolescents & women over 40 years old
  • Have just had an abortion/miscarriage
  • Breastfeeding women 6 weeks postpartum
  • HIV infected whether or not on ART
Advantages & non- contraceptive benefits
  • New formulation for S/C injection
  • 30% low side effects compared to Depo-Provera
  • Do not interfere with sex
  • Private & no one else can tell that a woman is using it
  • May help women gain weight
  • Do not require daily action
  • Prevents pregnancy
  • Protects against endometrial cancer, uterine fibroids
  • Reduces sickle cell crisis among women with sickle cell anemia
  • Protects against symptomatic PID & iron deficiency aneamia
Contraindications

Sayana press is contraindicated in the following:-


  • Clients with a known hypersensitivity to MPA
  • Pregnancy (known or suspected)
  • women with known or suspected malignancy of the breast or genital organs
  • clients with undiagnosed vaginal bleeding
  • patients with severe hepatic impairment
  • patients with metabolic bone disease
  • patients with thromboembolic disease
  • patients with current or past history of cerebro-vascular disease
Disadvantages & Side effects
  • Weight gain or loss
  • Does not protect against STI/HIV/AIDs
  • Delayed fertility return
  • Hypersensitivity reactions
  • Decreased/increased appetite
  • Loss of libido & irritability
  • Dizziness, headache & migraine
  • Thromboembolic disorders
  • Nausea & vomiting
  • Jaundice
  • Alopecia & urticaria
  • Loss of bone mineral density
  • Back & leg pains
  • Mood changes
  • Abdominal bloating & discomfort
Problems that may need medical attention
  • Loss of bone mineral density
  • Menstrual irregularities
  • Thromboembolic disorders
  • Anaphylaxis & anaphylactoid reactions
  • Sudden partial or complete loss of vision
Permanent Method/Voluntary Surgical Contraceptives

 Because male and female sterilization are permanent methods of contraception, thorough counseling procedures must be followed to ensure that the client fully understands his or her choice and to minimize chances of regret. Clients younger than 30 years old or with fewer than three children require particularly careful counseling and exploration of other long-term method options.

  1. Tubal ligation/tubectomy
  • This is a voluntary surgical procedure for permanent termination of fertility in women.
  • It can be done by a mini-operation (laparatomy/laparoscopy)
Mode of Action
  • Blocking fallopian tube by cutting, cautery, rings or clips
  • Prevent sperms from reaching the ovum
Indications

 In general, the majority of women who want tubal ligation can have a safe and effective procedure in a routine in a health facility equipped to provide the service, provided they have been counseled. They should also be able to give informed consent. Women who may consider tubal ligation include:

  1. Those who are certain that they have achieved their desired family size
  2. Women who want a highly effective permanent method of contraception
  3. Women for whom pregnancy presents unacceptable risk Family planning should be delayed in case of:
    1. Pregnancy
    2. Immediately/early postpartum if woman had severe pre-eclampsia/eclampsia, early rupture of membrane (EROM), sepsis etc.
    3. Complicated abortion (infection, hemorrhage)
    4. Current DVT
    5. Unexplained vaginal bleeding (before evaluation)
    6. Malignant trophoblastic disease
    7. Current PID or purulent cervicitis
    8. Current gall bladder disease
    9. Severe anemia
    10. Acute respiratory disease
    11. Acute systemic infection or gastroenteritis
    12. Abdominal skin infection –      peritonitis
Timing of the tubal ligation
  1. Immediately after childbirth or within first seven days (if she made voluntary choice in advance)
  2. Six weeks or more after childbirth
  3. Immediately after abortion (if she made voluntary choice in advance)
  4. any time provided pregnancy is ruled out (but between seven days and six weeks postpartum)
  5. during caesarean section
Benefits
  • Highly effective
  • Effective immediately
  • It is permanent
  • It is a simple surgery, usually done under local anesthesia
  • No exposure or worries about contraception
  • No further expense or worries about conception
  • No long term side effects
  • Does not interfere with sexual intercourse
Disadvantage
  • Does not protect against STIs/AIDs
  • It is irreversible
Side effects
  • Wound infection
  • Post-operative fever
  • Bladder and intestinal injuries(rare)
  • Hematoma
  • Pain at the incision (post operatively)
  • Superficial bleeding
Challenges associated with tubal ligation
  • Desire for more children after when the operation is done
  • Excessive desire in reversal
  • Disagrees to sign the informed consent form
  • Pressure from the someone else
  • Depression
  • Marital problems
  • Single women
  • Women with no children
General complications of tubal ligation
  1. Obesity
  2. Psychological upset
  3. Chronic pelvic pain
  4. Congestive dysmenorrheal
  5. Menstrual abnormalities like menorrhagia, hypomenorrhea
  6. Alteration in libido.
2.     Vasectomy
  • This is a voluntary surgical procedure for permanently terminating fertility in men
Mode of action

Blocking the vas deferens (ejaculatory duct) so that sperms are not present in the ejaculate.

Indications

  • Those who are certain that they have achieved their desired family size
  • Men who want a highly effective permanent method
  • Men whose wives face unacceptable risk in pregnancy
Contraindications

Vasectomy should be delayed in case of:


  • Local infections (scrotal skin infections, orchitis etc)
  • Current STI
  • Systemic infections
Benefits
  • Highly effective
  • It is permanent
  • It is a simple surgery done under local anesthesia
  • No further expense or worries about conception
  • No long term side effects
  • Does not interfere with sexual intercourse
Side effects
  • Wound infection
  • Scrotal hematoma
  • Granuloma
  • Excessive swelling
  • Pain at incision sites
Explain the following to the clients
  • When to come back for follow up visits
  • Common side effects of the method offered
  • What to do if there are changes in the menstrual periods
  • How soon the method is effective
  • How to protect against STIs
  • How to care for the wound in case of implants, vasectomy and tubal ligation
General instruction to the clients using permanent methods of family planning
  1. Inform him or her when to come back for follow up visits
  2. Explain the common side effects of the method in a simple language
  3. Tell the client the warning signs or possible problems that may require medical attention
  4. Tell the client what to do if there are changes in the menstrual periods
  5. Inform the client how soon the method is effective
  6. Let the client know that the method does not protect against HIV/AIDs and STIs and emphasize on the use of backup methods like condoms
  7. Guide the client on how to care for the wound post operatively
Emergency /Post Coital Contraceptives

Emergency contraception (EC) refers to methods of contraception used by women to prevent unintended pregnancy following unprotected sexual intercourse. It should not be used as a routine contraceptive method. EC not a method for termination of pregnancy

Indications
  1. Any woman who has had unprotected sexual intercourse
  2. Women who have been raped
  3. Any woman whose contraceptive method has failed (e.g. condom broke or slipped)
  4. Any woman who has forgotten to take her COC pills for more than two days or who has forgotten to take her POP at the regular time
  5. Missed injection for more than two weeks
  6. Delay in taking pills more than 3 hours
  7. Sexual assault or rape and the first time intercourse
Contraindications
  1. Pregnancy
  2. After 120 hours or 5 days of unprotected sex
Types
  1. Emergency contraceptive pills (ECP)
  2. Progesterone only pills regimen.

They are the preferred ECP regimen as they are more effective and have fewer side effects than COC pills

When to start?

 This should be started or taken within 5 days or 120 hours but the sooner the better following unprotected sexual intercourse.

What to use and the dose
  1. Lofemenal or microgynon 4BD for 1 day (low dose COC)
  2. Eugynon (high dose COC) 2BD for 1day
  3. Regular POP such as Ovrette or microval can be used in recommended dose
  4. Levonogestrel 2stat
  5. Postinar 2 BD for 1day
  6. vikela orlevonelle-2 or Norlevo plan B may be used
Side effects
  1. Nausea & vomiting
a)            Intrauterine contraceptive devices (IUCDs)

Introduction of copper IUCDs with a maximum period of 5days can prevent conception following accidental unprotected sexual exposure.

Mechanism of action
  • Prevents implantation
  • Failure rate is about 1%
  • Effectiveness is over 99% in preventing pregnancy
Notes

Post coital contraception is only employed as emergency measure and is not effective if used as regular method of contraception with the exception of the copper IUCDs

Women who need emergency contraception should be counseled about regular contraceptive options and encouraged to use regular methods consistently and correctly. Referral:
  • Women should be referred for other relevant services such as HIV counseling and testing, post exposure prophylaxis (PEP) and treatment for STIs
  • Women should be referred to specialized services such as for sexual and gender based violence.
Basic steps of client care for ECP
  • Greet client, introduce yourself, and ask what he/she
  • Show a respectful attitude
  • Explain that your discussion with the client will be kept
  • Explain the different ECP
  • Screen the client for ECP use.
  • Tell client about ECPs; give clear information about use, side effects, and needs for referral or follow-up.
  • Encourage her to ask questions
  • Discuss options for regular contraception with client
Counseling ECP clients

When counseling a client about ECP, the provider should:

  • Actively involve the client in the counseling process
  • Reassure the client that all information she gives you is kept confidential
  • Provide a private and supportive environment
  • Do not make judgmental comments or indicate disapproval through body language (such as such as crossing your arms over your chest)
  • Be responsive to the client‘s needs
  • Be supportive of the clients choices
  • Be respectful

Hormonal Methods of Family Planning Read More »

hormonal Family Planning

Artificial Methods of Family Planning

Artificial methods of family planning refer to the use of various techniques and devices to prevent pregnancy. These methods rely on the use of physical barriers, chemicals, or surgical interventions to either prevent sperm from reaching the egg or to interfere with the fertilization process.

FAMILY PLANNING CARD

artificial

 Criteria to follow before a client is put on a family planning methods

History taking

    1. Personal Age, sex, address, next of kin
    2. Social Marital status, education, any habits that may affect choices of some family planning methods e.g. smoking
    3. Medical To identify the presence of medical diseases, problems, sickle cell, medications.
    4. Reproductive /obstetric history:
      • Find out when clients started her period
      • How many children/pregnancies she had
    5. Gynecological To identify any diseases affecting a woman‘s reproductive organs e.g. bleeding, cancer of the cervix, PIDs, breast cancer etc.
    6. Family planning To find out about previous use of family planning methods.

General examination

Should be done from the head to toes;

  • Anemia, edema, jaundice, lymphadenopathy
  • Breast for colour changes, masses
  • Per abdominal examination to check for masses
  • Per vaginal examination to check for abnormal discharges

Note: Weight, blood pressure should be recorded when starting one on family planning especially the hormonal ones.

Artificial methods of family planning

 Barrier methods

  1. Spermicides
  2. Condoms
  3. IUCDs
  4. Diaphragm
  5. Intra-vaginal contraceptive sponge
  6. Cervical caps
Condoms (male and female)
  • This is the most popular and oldest method
  • This is a rubber sheath that is worn by a woman or man during sexual intercourse
  • It is the only family planning method that prevents both pregnancy and STIs including HIV/AIDs if used consistently and correctly.
Indications

Condoms can be used by any man or woman regardless of his/her health status. People in particular need of condoms include:

  • Men wishing to participate more actively in family planning
  • Sexually active adolescents
  • Couples who have sexual intercourse infrequently
  • People in casual sexual relationships where pregnancy is not desired
  • Couples needing a back-up method while waiting for another contraceptive methods to become effective.
  • Couples who need a temporary method while waiting to receive another contraceptive method.
  • Those who are at increased risk of STIs, (e.g. when one or both partners have other partners)
  • Couples where one or both partners are HIV positive
Male Condoms

Male condoms are sheaths or coverings that fit over a man‘s erect penis. Most are made from thin latex rubber; some are polyurethane (plastic).

Primary mechanism of action
  • Work by forming a barrier that keeps sperm out of the vagina, preventing pregnancy
  • Also keep infectious agents in semen, on the penis, or in the vagina from infecting the other partner
Effectiveness
  • Protection against pregnancy:
  • As commonly used, about 18pregnancies per 100 women whose partners use male condoms over the first year
  • When used correctly with every act of sex, about 2 pregnancies per 100 women whose partners use male condoms over the first year
Protection against HIV and other STIs:
  • Male condoms significantly reduce the risk of becoming infected with HIV when used correctly with every act of sex.
  • When used consistently and correctly, condom use prevents 80% to 95% of HIV transmission that would have occurred without condoms.
  • Condoms reduce the risk of becoming infected,
    • Protect best against STIs spread by discharge, such as HIV, gonorrhea, and Chlamydia
    • Also protect against STIs spread by skin to skin contact, such as herpes and human papilloma virus (if condom covers lesions)
Any client concerns or questions
  • Reinforcing correct condom use and reminding clients that condoms should not be reused
  • Allergy to latex
Dispelling myths regarding condoms

Male condoms:

  • Do not make men sterile, impotent, or weak
  • Do not decrease men’s sex drive
  • Do not promote promiscuity
  • Cannot get lost in the woman’s body
  • Do not have holes that HIV can pass through
  • Are not laced with HIV
  • Do not cause illness in a woman because they prevent semen or sperm from entering her body
  • Do not cause illness in men because sperm may move back up
  • Are used by married couples; they are not only for use outside marriage
Who should not use condoms?

Individuals allergic to latex should consider other contraceptive options. However, for those at risks of STIs/HIV, condom use is still appropriate as there are no other methods that offer STI/HIV protection.

How to use male condoms
  1. Use a new condom for each act of sex. Check package for damage and check the expiration Tear open carefully without using any sharp objects.
  2. Before any physical contact, put condom on the tip of the erect penis with the rolled side out.
  3. Unroll condom all the way to the base of the erect penis.
  4. Immediately after ejaculation, hold rim in place and withdraw penis while it is still Slide the condom off, avoiding spilling semen.
  5. Dispose of the used condom safely.
Practices to avoid when using condoms
  • Unrolling condom before putting it on
  • Using oil-based lubricants with latex condoms
  • Using condoms that may be old or damaged (e.g. dried out, brittle, sticky)
  • Reusing condoms

Practicing dry sex as it increases possibility of condom breakages due to friction

Artificial family planning female condoms (1)
Female Condoms
  • Female condoms are sheaths, or linings, that fit loosely inside a woman‘s vagina
  • Most common type is Female Condom Two (FC2) made of thin, soft, synthetic rubber film, with flexible rings at both ends
  • Latex female condoms are available in some countries Primary mechanism of action
  • Work by forming a barrier that keeps sperm out of the vagina, preventing pregnancy
  • Also keep infectious agents in semen, on the penis, or in the vagina from infecting the other partner
Effectiveness

Protection against pregnancy:

  • When used correctly with every act of sex, about 5 pregnancies per 100 women using female condoms over the first year
  • As commonly used, about 21 pregnancies per 100 women using female condoms over the first year.
  • Protection against HIV and other sexually transmitted infections (STIs):
  • Female condoms reduce the risk of infection with STIs, including HIV, when used correctly with every act of sex.
Characteristics of female condoms
  • Safe
  • Women can initiate their use
  • Have a soft texture that quickly conducts body heat during sex
  • Provide dual protection (against STIs/HIV and pregnancy)
  • Outer ring provides added sexual stimulation for some women
  • Do not require provider‘s help
  • Can be inserted ahead of time so do not interrupt sex
  • Are not tight or constricting like male condoms
  • Do not dull the sensation of sex like male condoms
  • Do not have to be removed immediately after ejaculation
  • No side effects
  • Can be used as a temporary backup method of contraception
  • Protect women from conditions caused by STIs (pelvic inflammatory disease, cervical cancer, infertility)
  • As typically used, less effective than many other FP methods
  • Require partner communication and cooperation
  • May be difficult to insert
  • Can make noise during sex
Side effects of female condoms:
  • None
  • Allergic reactions to latex
Who can use female condom?
  • All men and women can safely use synthetic rubber female
  • All men and women can safely use natural latex female condoms, except those with a severe allergy to latex (extremely rare).
How to use female condoms
  1. Use a new condom for each act of sex.
    • Check the condom
    • Do not use if torn, damaged or past the expiration
    • Open the package
  2. Before any physical contact, insert the condom into the vagina. It can be inserted up to eight hours before sex. Find a comfortable position for insertion—squat; raise one leg, sit, or lie down. Grasp the ring at the closed end, and squeeze it so it becomes long and With the other hand, separate the outer lips and locate the opening of the vagina. Gently insert the inner ring into the vagina as far up as it will go. Insert a finger into the condom to push it into place. (The inner ring should be pushed up just past the pubic bone.)
  3. Ensure that the penis enters the condom and stays inside the
  4. To remove the condom, hold and twist outer ring to seal in fluids, and gently pull condom out of the vagina. The female condom does not need to be removed immediately after sex, but any time before standing up, to avoid spilling semen.
  5. Dispose of the used condom safely.
Tips for new users
  • Suggest to a new user that she practice putting in and taking out the condom before the next time she has sex. Reassure her that correct use becomes easier with practice. A woman may need to use the female condom several times before she is comfortable with it. 
  • Suggest she try different positions to see which way insertion is easiest for her.
  • The female condom is Some women find insertion easier if they put it in slowly, especially the first few times.
  • If a client is switching from another method to the female condom, suggest that she continue with the previous method until she can use the female condom with confidence.
Provide follow up and counseling for
  • Any client concerns or questions
  • Correct condom use 
Dispelling myths regarding female condoms

Female condoms:

  • Cannot get lost in the woman‘s body
  • Are not difficult to use, but correct use needs to be learned
  • Do not have holes that HIV can pass through
  • Are used by married couples; they are not only for use outside marriage
  • Do not cause illness in a woman because they prevent semen or sperm from entering her body
General Advantages
  1. Effective when used correctly
  2. No medical supervision required
  3. Convenient to carry
  4. Prevents both pregnancy and STIs including HIV/AIDs
  5. Easy to use
  6. Reduce risk of systemic side effects and reaction
  7. Fairly cheap and available in almost every places
General Disadvantages
  1. There is loss of spontaneity
  2. May rupture or lose position during intercourse
  3. It is often associated with extra marital sex and STIs
  4. It is not suitable for poorly motivated persons
  5. There is lack of privacy while purchasing condoms
  6. It cannot be used by a man who cannot maintain erection
  7. Requires male responsibility
  8. It is considered unclean to some people
Spermicides

This involves application of chemicals into the vagina to prevent pregnancy.

Mode of action
  • Aims at killing or inactivating sperms
Forms of Spermicides
  • Jellies
  • Creams
  • Foams
  • Tablets
  • Lubricants in condoms
  • Ingredient in vaginal sponge
Advantages
  1. Available without prescription
  2. Fairly effective if used correctly
  3. Can be used as backups
  4. Used only if required
  5. Control is in the hand of a woman
  6. Provide extra-vaginal lubrication
  7. Protects against some STIs and PIDs
Disadvantages
  1. Not effective when used alone
  2. Some couple find the method messy i.e. too fluidic
  3. Associated to some allergic reaction
  4. Interrupts sexual intercourse
artificial Intra-Uterine Contraceptive Device (IUCDs)
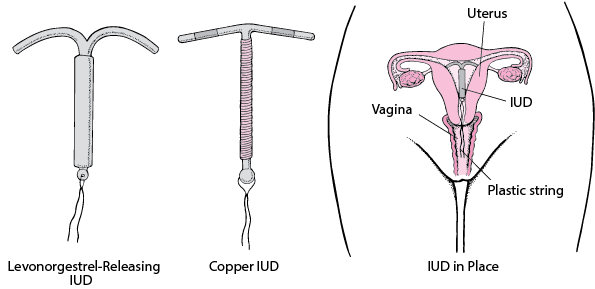
   Intra-Uterine Contraceptive Device (IUCDs)

These are devices inserted into the woman uterus to prevent implantation of the fertilized ovum by local inflammation.

Types of IUCDs

  • Copper T 380A effective for 10-12 years
  • Multi-load 375 for 5 years
  • Mirena R hormonal IUCD
Advantages
  1. It is very effective since it starts working right way
  2. She does not need to keep coming for refill
  3. Can offer protection up to 10 years and above
  4. Fertility returns is immediate
  5. Limited side effects reported as compared to other methods
  6. Does not interfere with sexual intercourse
  7. Has no effects on breastfeeding
  8. Only one follow up is needed unless there are problems
Side effects
  1. Increases menstrual bleeding
  2. Spotting
  3. Abnormal vaginal discharge
  4. Menstrual cramps
  5. PID
Indications
  1. Breastfeeding
  2. Women of any age
  3. As for POP
Contraindications
  1. Irregular vaginal bleeding of unknown origin g. cancer of cervix
  2. Pregnancy
  3. Heavy and painful menstruation
  4. Cancer of the uterus
  5. Current PIDs
  6. Multiple sexual partners
  7. Pregnancy
IUCDs users who develop PID should be treated with the IUCD in place if they want to continue using it. If no improvement within 72 hours, remove it.

 Insertion of IUCD Timing of IUCD insertion

  • Any time provided pregnancy is ruled out
  • The first seven days of the menstrual cycle
  • Immediately following delivery or any time within 46 hours after childbirth
  • Any time beyond four to six weeks after childbirth
  • Immediately or within seven days after an uncomplicated abortion
  • During caesarean section
Procedure
  1. Consider aseptic technique like hand washing, wearing sterile gloves.
  2. The device is put in an introducer and plunger.
  3. It straightens inside the introducer.
  4. Insert a Cusco ‘s vaginal speculum and clearly visualize the cervix.
  5. Clean the cervix and vaginal vault with sterile swabs.
  6. Measure the length of the uterus with a uterine sound.
  7. Insert the introducer into the uterus through the cervix.
  8. The plunger is gently pushed to force device out of the introducer into the uterus.
  9. In the uterus, the device resumes its original shape and lodges against the uterine walls.
  10. The two small strings attached to the device hang down through the cervical opening.
  11. Cut the string with a pair of scissors to reduce the size approximately 3cm hanging out of the cervix.
  12. After the insertion, the client She can remain on the procedure table until she feels ready to get dressed.
  13. The woman usually feels the strings in the vagina to ensure that the device is in position.
Post insertion instructions
  1. To use back up for a minimum of 3 days.
  2. There may be some slight pain which does not require medication.
  3. To check the string during menstruation to ensure that it is in place or come back if it is removed or dislodged.
  4. To return to the facility immediately in case of any discomfort.
Removing the IUDs
  1. In case a client is finding side effects difficult to tolerate, first discuss the complaints the client has. Weigh if she would rather try to manage the problem or to have the IUD removed.
  2. Removing IUD is usually It can be done any time of the month.
  3. Removing may also be easier during monthly bleeding, when the cervix is naturally In cases of uterine perforation or if removal is not easy, please refer the client to an experienced service provider to employ appropriate removal technique.
Steps for IUD removal
  • Explain what you are going to do to the client during removal
  • Ensure privacy & confidentiality at all times
  • Request the client to lie on her back
  • The provider inserts a vaginal speculum to visualize the cervix & UID strings
  • Carefully cleans the cervix & vagina with an antiseptic solution such as Savlon & do inspection
  • The provider requests the client to take slow, deep breaths & to Inform the client to make you know in case she feels pain or any other discomfort during the procedure
  • Using narrow forceps, the provider gently pulls the IUD strings & slowly until it comes completely out of the cervix
  • Show the removed IUD to the client & let her handle with the hands. This helps to make the client understands that nothing has remain inside the uterus.
  • Thank the client for cooperating throughout the procedure
  • Clear away
Reasons for missed threads in IUDs
  1. Coiled thread inside
  2. Thread torn through
  3. Device expelled outside unnoticed by the client
  4. Device perforated the uterine wall and is lying in the peritoneal cavity
  5. Device pulled by the growing uterus in pregnancy
Methods of identification
  1. History taking i.e. exclude pregnancy
  2. Ultrasonography
  3. Hysterectomy
  4. Hysteroscopy
  5. Straight x-ray

Artificial Methods of Family Planning Read More »

hormonal Family Planning

Family Planning

Family Planning is defined as a process through which individuals, couples make up an informed choice on how many children to have, when to have and how often to have so that each child born is expected and properly catered for in all ways. 

For instance, basic needs like good health, education, shelter, and all essential needs of humans are available.

This involves planning and proper birth spacing according to wishes rather than by chances. Birth spacing promotes the health of the mother, children and father.

Consent for family planning services

No verbal or written consent is required from parent, guardian or spouse before the client can be given family planning services except in cases of incapacitation (intellectual disability). Clients should give written consent to permanent family planning methods.

Setting of family planning clinics

Service delivery points where a health provider comes into contact with a potential or actual client

  • Social mobilization events for any health services
  • Youth clubs and schools through family life education activities
  • Women and men organized clubs/groups
  • Work places

Where to get family planning services

    • Facility based outlets such as hospitals, health centers and dispensaries
    • Outreach services including mobile clinics and workplaces
    • Community based outlets e.g. community based distribution, drug shops and dispensing machines
    • Social marketing
    • Private sector facility such as clinics, maternity and nursing homes, pharmacies and drug retail shops

Counseling

In order to promote informed choice, all clients seeking contraceptives are entitled, given accurate and adequate information about family planning methods available in the common settings. This is important for the initiation and continuation of family practice. Methods (of choice) of clients will be done individually and in a dignified manner. The discussion between the service provider and client must be private, confidential and should never include incentives or coercion for the adaptation of any method.

Initial counseling should include the following:

  • Discussion of client’s reproductive goals, previous knowledge and/or experience with any method
  • Showing the FP methods available
  • Information on how each method prevents pregnancy
  • How effective the method is and what conditions make I effective
  • Method failure
  • Common side effects
  • The follow-up regarding each method
  • Where the method can be obtained
  • Importance of physical and pelvic examination
  • Information on HIV/AIDs/STIs in relation to F/P
  • HIV testing and screening of STIs
  • Symptoms of breast and cervical cancer including available services for screening
  • Clarification of misconceptions or rumors the client may have about each type of method

Subsequent counseling will aim at promoting and encouraging continued use of a method and should include:

  • A review of the client ‘s satisfaction or problem with the method
  • A review of the client ‘s understanding of user instructions
  • Dispelling rumors and/or misconceptions, if any
  • In indicated, a review of change of the client’s reproductive goal necessitating the need for a long term or permanent method
  • Counseling on STIs and HIV/AIDs
  • Possible method failure
  • Information of common symptoms of breast and cervical cancer including available services for screening
  • Counseling is also important:
  • Where a contraceptive method has failed
  • There is regret for having had a permanent method
  • In cases of rape or defilement
  • Where there are is need for referral for appropriate care

Screening

After a thorough counseling a client should then be ready to choose a contraceptive method. The next step is to screen for contraceptive use.

  • Clients opting for hormonal method should have the relevant health, social history taken and physical assessment carried out on the first or subsequent visits. Where indicated, do a complete physical check up to rule out contra-indications to method use. Where is not possible or necessary to perform routine physical assessment, the client should be screened by a qualified staff or FP trained service provider using a standard checklist to initiate or resupply oral contraceptive or Depo Provera. After screening, the important findings should be communicated to the client including any issues she/he may want clarification on. The client will then be provided with the appropriate or preferred method and important findings should be recorded according to the guidelines.
Routine physical or pelvic examinations is not obligatory for initiating or re-supply of oral contraceptives or Depo Provera, an examination could be valuable for reproductive health and may help to rule out contra-indications to methods and/or establish the presence or absence of infections or cancer.

Where selected physical assessment or laboratory tests are indicated and is not possible to carry them out at a particular clinic, clients should be referred to a health unit equipped to provide the assessment test.

Importance of family planning

a)   To the mother

  1. Allows mother to recover physically and mentally from the effects of previous pregnancy
  2. Offers ample time for a woman to actively participate in productive activities like farming and business.
  3. It increases social bondage between the mother and her baby
  4. It helps to reduce on maternal mortality and morbidity the couples due to pregnancy related complications
  5. It promotes a happy marital life and enjoyment between the couples without fear of getting unwanted pregnancy.
b)    To the child
  1. Child receives adequate emotional and social support and as a result gets emotional maturity and stability
  2. Allows adequate nutrition of the baby while in the womb and hence a healthy newborn
  3. There is reduction of malnutrition as there is no early weaning and likely to have enough food for the child
  4. The child gets fewer infections since immunity is
c)     To the father
  1. Reduces domestic violence in a home
  2. Ability to meet basic needs like foods, medical care
  3. Reduces the cost of living in a home hence the father is able to invest in productive
d)    To the Community
  1. Healthy and productive people who enhance community stability and harmony
  2. Reduces overcrowding hence available land can be maximize for productivity
  3. There will be increased socio-economic development
  4. Presence of bad characters in the community like street kids, smokers and other bad group in the community since parents have adequate time to provide for their
e)     To the Nation
  1. Reduces rapid population growth rate
  2. Reduces the country‘s dependence on foreign aids
  3. The government will be able to provide better social services and infrastructures like roads, health facilities
  4. It is easy to budget for the people since the number of resources to the population is

Available family planning methods in Uganda

 The family planning methods can be broadly classified into: –

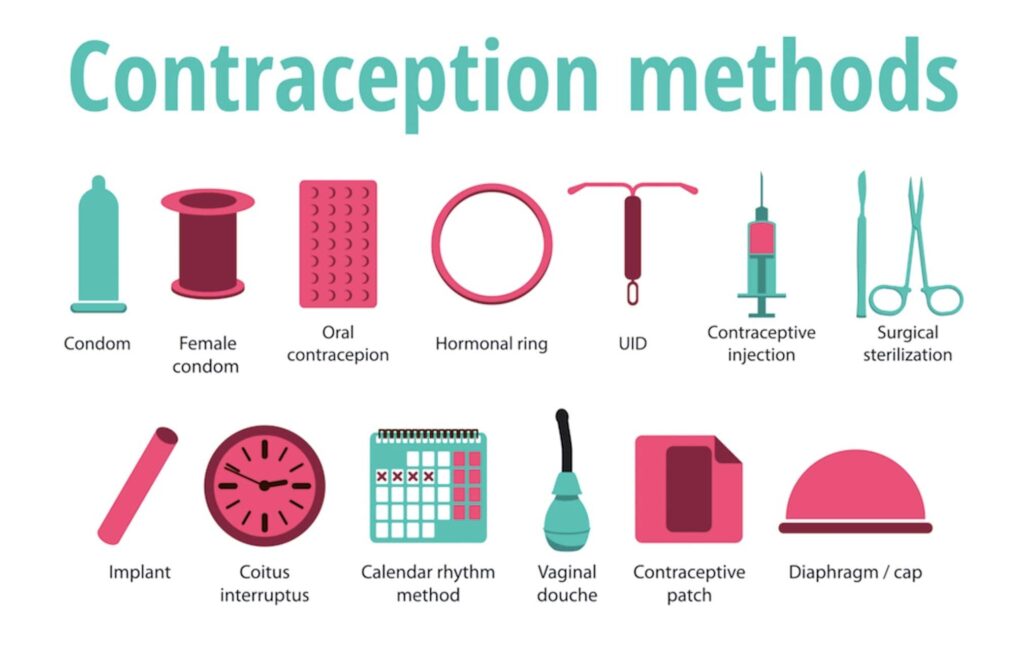
  • Natural family methods.
  • Hormonal /Artificial family planning.
1.     Natural /traditional methods
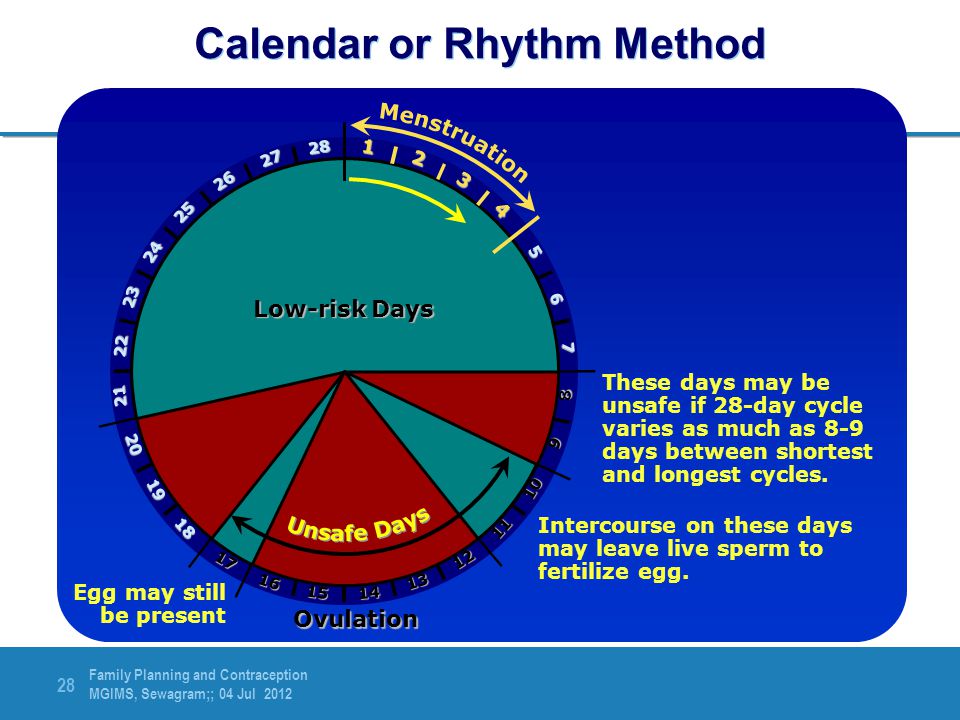
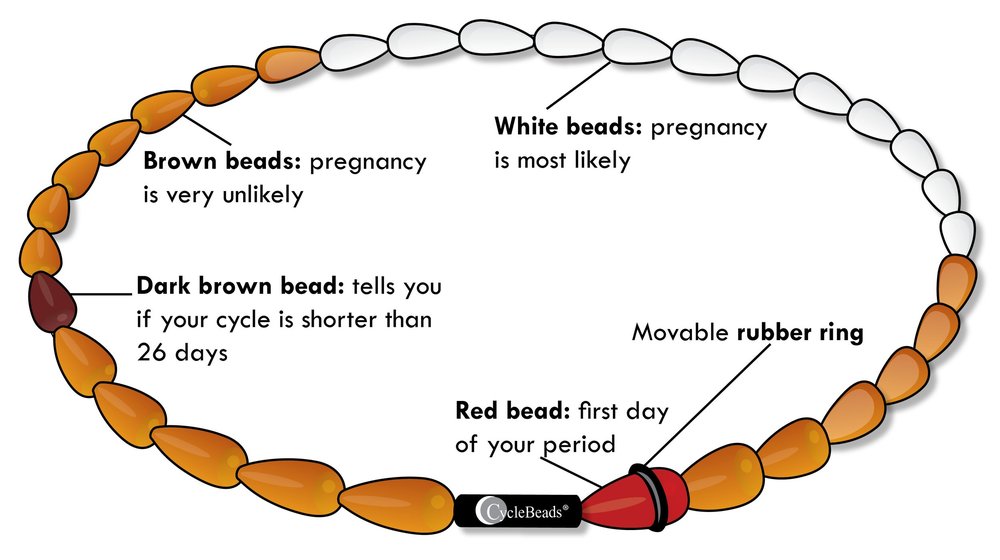
  • Calendar/rhythm
  • Basal body temperature
  • Cervical mucus method
  • Lactation amenorrhea methods
  • Abstinence
  • Withdrawal/coitus interrupters
2.     Artificial methods
  1. Barrier methods
  • Spermicides
  • Condoms
  • Intrauterine contraceptive devices (IUCDs)
  • Diaphragm
b)    Hormonal methods
  1. Oral pills
    • Combined oral contraceptives
    • Progesterone only pills
    • Emergency contraceptive pills
ii.          Implants
  • Implanon (1 rod capsule)
  • Jadelle (2 rod capsules)
  • Norplant (6 rod capsules)
iii.          Injectable contraceptives
  • Depo Provera
  • Injector plan
  • Sayana press
  • Noristerat
c)     Permanent methods
  • Tubal ligation (tubectomy) for women
  • Vasectomy for men

Natural methods of family planning

These are also known as fertility awareness method. They are based on the following physiological conditions.

  • The lifespan of a sperm is 24 hours
  • The lifespan of an ovum is 48 hours
  • Menstruation takes place between 1-16 days before the next period
General advantages
  1. They are safe with no side effects
  2. Cheap
  3. They are acceptable to many groups and religious that opposes the modern methods
  4. They teach women about their own menstruation cycle and fertility
  5. Couples have control over their methods
  6. Help in planning a pregnancy
General disadvantages
  1. Some require substantial teaching before use
  2. It is difficult as records on several cycles ought to be kept for proper references
  3. Difficult to use if the period are irregular
  4. Requires adjustment to sexual behaviors
  5. Requires co-operation between the partners which in most cases is difficult
  6. Do not protect against STIs/HIV/AIDs

 Fertility awareness method

 Fertility awareness methods of family planning involve identification of the fertile days of the menstrual cycle (when pregnancy is most likely to occur) and avoiding sexual intercourse (or using barrier methods) during these days. The fertile days of the menstrual cycle can be determined by one of the following methods:

  • Basal body temperature (BBT)
  • Cervical mucus
  • Symptom- thermal (a combination of cervical mucus and BBT methods)
  • Calendar (rhythm) or Standard Days method, including cycle
A woman or couples who are planning to use fertility awareness methods need special training from a trained counselor in family planning.

Indications

 Any woman or couple who is willing and motivated to observe, record and interpret fertility signs daily.

    • Women who find other contraceptive methods unacceptable for various reasons including religious beliefs
    • Women who are unable to use some other methods for health reasons
    • Couples who are willing to abstain from sexual intercourse (or use condoms) for more than one week during each days
Contraindications

There are no medical conditions that are worsened with the use of fertility awareness methods. However, there are some conditions that make their use more difficult. If these conditions are present, the method can either be delayed or the provider should offer special counseling to ensure the correct use.

These conditions include:

  • Breast feeding (especially until menses return)
  • Less than three postpartum menses
  • Irregular vaginal bleeding
  • Abnormal vaginal discharge
  • Disease that evaluates body temperature
Calendar or Rhythm Method

Calendar /rhythm method

  • This is the only method approved o the Roman Catholic Church
  • Before starting to use this method, one needs to have an accurate record of menstrual cycles for about 6-8 months
  • The failure rate is between 20-30%
  • The method is referred to as ―safe days‖ because it aims at identifying days with least chance of conception
  • The woman should provide a record of her menstrual cycles to the health worker and then go into the calculation as shown below.
Calculating the fertile period

Fertile period is the time of the cycle when a woman has the ―highest ―chances of conception.

Procedure
  1. Record the length of each Length of a cycle is the time between the first day of one menstruation period and the first day of the following period
  2. Identify the shortest and longest cycle
  3. Get the first fertile day (FFD) by subtracting 18 from the shortest cycle (16 + 2 days of sperm survival)
  4. Get the last fertile day (LFD) by subtracting 11 from the longest cycle (12-1 day of ovum survival)
Examples

A woman with a regular cycle of 28 days duration report to the family planning clinic and has opted for calendar method. Demonstrate the ability to calculate this in order for her to start using the method.

  1. Record the length of each menstrual cycle: This is the time between the first day of one menstruation period and the first day of the following period.
  2. Identify the shortest and longest cycles: Determine the cycle with the fewest days as the shortest cycle, and the cycle with the most days as the longest cycle.
  3. Calculate the first fertile day (FFD): Subtract 18 from the duration of the shortest cycle. This accounts for the fact that sperm can survive for about 2 days.
  4. Calculate the last fertile day (LFD): Subtract 11 from the duration of the longest cycle. This considers the fact that the ovum (egg) can survive for about 1 day.

Here’s an example to demonstrate how to apply this method:

Examples
  1. A woman with a regular cycle of 28 days duration report to the family planning clinic and has opted for calendar method. Demonstrate the ability to calculate this in order for her to start using the method.

Given: Number of cycles: 28 days

To calculate:

Shortest cycle: 28 – 18 = 10th day

Longest cycle: 28 – 11 = 17th day

Interpretation:

The woman is highly fertile between the 10th and 17th days of her cycle.

Comments/Remarks:

  • It is recommended to avoid sexual intercourse between the 10th and 17th day of her cycle.
  • It’s advisable to use condoms or another form of contraception as a backup method.

      2. A woman with irregular cycle whose shortest cycle is 25 days and the longest cycle is 32. Calculate and interpret he finding to the client

Solution

Given number; Shortest cycle =25 days Longest cycle=32 days

Therefore:

FFD=shortest cycle=shortest cycle-18          =25-18 =7th day

LFD=longest cycle-11                =32-11                  =21st day 

Interpretation

  • A woman is very fertile between 7th-21st day of every cycle
  • Avoid sexual intercourse between 10th-17th day of her cycle
  • To always use condoms or any other family planning method as a dual or backup
Self-help assessment

Demonstrate your ability to calculate & interpret the following to the client:-

  • A client with cycle of 29 regular
  • A client with cycles of 24 & 30 days respectively (irregular cycles)
  • A client with 27 day cycle (regular)
Advantages
  1. No cost
  2. No side effects
  3. Refer to general advantages of natural methods of family planning
Disadvantages
  1. Difficult to calculate the safe period reliably
  2. Needs several months training to use these methods
  3. Compulsory abstinence from sexual act during certain periods
  4. Not applicable during lactation amenorrhea when the periods are irregular
  5. Does not protect against STIs including HIV/AIDs


Lactation amenorrhea method

  • Immediately after birth, there is a period of naturally decreased fertility which can be prolonged by regular breastfeeding. The hormone responsible for the suppression of fertility is prolactin that controls milk production.
  • The effect of breast feeding on reducing fertility awareness is well known. However, LAM is a temporary 9 short- term) method of contraception. It is highly effective for the first six months after delivery, providing the woman breastfeed fully and remains amenorrhoeic.
  • In non- lactating mothers, prolactin gradually decreases within weeks after child birth reaching normal levels in about 4 weeks post-partum.
  • Regular nipple stimulation by sucking is necessary to maintain milk production and lactation amenorrhea method.
  • LAM may last up to 24 months during a regular prolactin release which inhibits the ovarian functions
  • When all three criteria of LAM are met, it is about 98%
Indications
  1. Women who are fully breastfeeding and
  2. Who are amenorrhoeic (no menses) and
  3. Whose baby is not older than six months
Fully breastfeeding means:
  • Breast feeding whenever the baby desires (at least every four hours)
  • Night time feeding (at least every six hours)
  • Not substituting other food or drink in place of breast milk
Who cannot use LAM/contraindications?
  1. Women whose menses have returned.
  2. Women whose babies have turned six months old.
  3. Women who have introduced supplementary feedings.

Note: Women with HIV should be counseled about the infant feeding options to reduce risk of mother-to-child transmission and be supported in their choice. Women without reliable access to safe alternative feeding options should be encouraged to breast feed exclusively for six months

Standard Days Method (Moon beads/cycle beads)

The Standard Days Method® is a fertility awareness-based family planning method that identifies a fixed fertile window for women with cycles that are between 26 and 32 days long. For women with cycles in this range, the method identifies days 8 through 19 as potentially fertile days. A user simply tracks the start date of her period and the days of her cycle to know if she is on a day when pregnancy is possible or not.

What are moon beads?
  • They are string of colored beads
  • The colors of moon beads help you know the days when you can get pregnant
  • They also help you know the days you are not likely to get pregnant
  • To prevent a pregnancy do not have sex on the days you can get pregnant, or use a barrier method.

Note: Moon beads are based on a natural method of family planning that is 95% effective when used correctly. This means that only 5 out of 100 women may become pregnant when the method is used correctly.

Modes of action

If a woman wants to prevent pregnancy using this family planning method, then she should avoid intercourse or use a back-up birth control method such as condoms during her fertile days (days 8-19). The patented Cycle Beads tools help a woman use this method by tracking her cycle, identifying her fertile and non-fertile days based on when her period started, and confirming that her cycles are in range for effective use of this family planning method.

Moon beads and the menstrual cycle
  • Moon beads represent a woman‘s menstrual cycle
  • Each bead is a day of the

Note: The menstrual cycle is not the same as the woman‘s period. The period is when a woman has menstrual bleeding while cycle includes all days from the start of one period to the day before the next period.


Indications/Eligibility/who can use it
  1. Couples who communicate well and agree not to have unprotected sex when the woman is likely to get pregnant
  2. Women who have failed to use other modern methods
  3. Women who have cycles that is between 26 and 32 days
Advantages
  • Refer to natural methods
  • More than 95% Effective
  • Side-Effect Free
  • Easy to Use
  • Inexpensive
  • Educational & Empowering
How to use moon beads
  1. The day you get your period, move the ring to the RED bead.
  2. Also mark that day on the calendar
  3. Move the ring, one bead each day
  4. Do not have unprotected sex when the ring is on any WHITE bead. You can get pregnant on those days
  5. You can have sex when the ring is on any brown beads. You are not likely to get pregnant on those days
  6. Move the ring to the RED bead again when your next period starts. Skip over any beads that are left.
MOON BEADS FAMILY PLANNING METHOD
When to contact the healthcare provider
  1. Had unprotected sex on a WHITE bead If she thinks she might be pregnant because she has not gotten her period.
  2. If she gets her period before she reaches the DARK BROWN beads, this means that her cycle is shorter than 26 days.
  3. If her period does not start by the DAY AFTER she reaches the last brown bead, this mean that her cycle is longer than 32

Family Planning Read More »

antenatal Care
Home > Reproductive > Antenatal Care in Reproductive Health

Antenatal Care in Reproductive Health

Antenatal Care (ANC) is a meticulously planned program of medical management and observation for pregnant women. It is directed towards making pregnancy and labour a safe, satisfying, and deeply rewarding experience.

The health of pregnant women would be drastically improved if effective ANC was universally available. Antenatal care, therefore, constitutes one of the absolute cornerstones of Safer Motherhood. The Ministry of Health strongly recommends the integration of services during ANC visits, including family planning, Elimination of Mother-to-Child Transmission (EMTCT) of HIV, and routine immunizations, to boost attendance and consumer satisfaction.

1. Aims and Purposes of Antenatal Care

Comprehensive antenatal care fulfills multiple critical purposes for the mother, the fetus, and the family. The aims include:

  • Promote Health: To promote and maintain the physical, mental, and social health of the mother during pregnancy.
  • Detect and Treat Conditions: To detect and treat conditions pre-existing or arising during pregnancy, whether they are medical, surgical, or obstetric.
  • Prepare for Safe Birth & Emergencies: To prepare the mother for the safe birth of the child and mentally/physically prepare her for potential emergencies and complications.
  • Achieve Healthy Delivery: To achieve the delivery of a full-term healthy baby (or babies) with minimal morbidity to the mother.
  • Ensure Normal Puerperium: To help the mother experience a normal puerperium and, in conjunction with her partner, take good care of the child’s physical, psychological, and social needs.
  • Recognize Deviations: To recognize any deviation from normal and provide management or treatment as required, always ensuring privacy.
  • Prepare for Lactation: To prepare the mother for successful breastfeeding and give specific advice about adequate preparation for lactation.
  • Nutritional Advice: To offer customized nutritional advice to the mother.
  • Parenthood Advice: To offer advice on parenthood either in a planned program or on an individual basis, taking the client’s concerns into consideration.
  • Build Trusting Relationships: To build up a trusting relationship between the family, the mother, and health workers. This encourages her to share her anxieties and fears about pregnancy through adequate communication and counseling.
  • Provide Preventive & Advisory Services: To provide preventive services and consult regarding the most appropriate place of delivery, emphasizing the concept of a clean safe delivery (e.g., preparing Maama kits).

2. Goals of Focused Antenatal Care

Focused Antenatal Care (FANC) emphasizes the quality of targeted actions over the mere quantity of visits. The goals differ depending on the timing of the visit.

  • To promote maternal and newborn health survival through:
    • Early detection and treatment of problems and complications.
    • Prevention of complications and disease.
    • Birth preparedness and complication readiness.

⚠️ Attention: FANC Guidelines

A minimum of 4 visits is aimed for an uncomplicated pregnancy. If a woman books later than the first trimester, the preceding goals should be combined and attended to immediately. At all visits, the midwife must address identified problems, check Blood Pressure (BP), and measure the Symphysio-Fundal Height (SFH).

Scheduling and Timing of Focused Visits

  • First Visit: By 0–16 weeks or as soon as a woman first thinks she is pregnant.
  • Second Visit: At 16–28 weeks (must be at least once in the second trimester).
  • Third Visit: At 28–32 weeks.
  • Fourth Visit: Between 36 weeks and delivery.
  • Additional Visits / Referral: Required if a complication occurs, intensive follow-up is needed, the woman wants to see a provider, or if findings (history, exam, testing) dictate frequent changes.

⚠️ Important: Goal Oriented Antenatal Care Protocol

Goals are different depending on the timing of the visit. A minimum of 8 contacts are aimed for in an uncomplicated pregnancy. If a woman books later than the first trimester, preceding goals should be combined and attended to. At all visits, address any identified problems, check the BP, and measure the Symphysio-Fundal Height (SFH).

Trimester / ContactGoalTiming of ContactHistory TakingExaminationLaboratory InvestigationsPromotionAction
FIRST CONTACT

First Trimester
(0 – 12 weeks)
  • Confirm pregnancy
  • General/Risk Assessment
  • Health Education
  • Plan for delivery
  • Appropriate preventive interventions
  • Involve the male partner / spouse
Contact 1:
Anytime ≤ 12 weeks
  • Presenting complaint
  • LNMP
  • Estimate period of gestation
  • Contraceptive?
  • Obstetric
  • Medical
  • Surgical
  • STI
  • Social: smoking, alcohol/drugs
  • TB screening
  • Intimate Partner Violence (IPV)
  • Dietary
  • General exam
  • Vital exam (e.g., BP, pulse)
  • SFH measurement
  • Abdominal/specific exam
  • Vulva exam (Speculum if indicated)
  • Nutritional assessment (height, weight, MUAC)
  • Hb (CBC where available)
  • HIV test
  • Syphilis test (RPR)
  • Blood group/RhD
  • Urine albumen, Glucose
  • Gram staining for ASB, urine culture if indicated
  • Glucose tolerance test (GTT) (for suspicious cases/hospital)
  • RDT for Malaria (where indicated)
  • Hepatitis B test
  • H/E on common pregnancy complaints
  • Address any problem
  • Involve husband in ANC
  • Draw up a birth and emergency preparedness plan
  • Counsel on PPFP methods
  • Danger Signs (abdominal pain, severe headache, blurred vision etc.)
  • eMTCT / PMTCT
  • Nutrition education, Hygiene, Rest and exercise
  • Infant feeding
  • LLINs, IPTp use
  • Dangers of smoking, alcohol and substance abuse
  • Tetanus/Diphtheria vaccine (Td)
  • Ferrous SO₄
  • Folic acid
  • Treat incidental ailments
  • Condom use for HIV prevention in discordant couples and those at high risk
  • Debriefing mother on findings and course of action
  • Give next appointment and explain what will be done, emphasising need to come back any time if there is need
2nd & 3rd CONTACT

Second Trimester
(>13 – 28 weeks)
  • Respond to abnormal Lab results
  • Provide preventive measures (Td, IPTp)
  • Exclude multiple pregnancy and fetal abnormalities
  • Promote nutrition and wellbeing
  • Assess for danger signs of Pregnancy Induced Hypertension and any other danger signs
  • Rule out anaemia
Contact 2:
13 – 20 Weeks

Contact 3:
21 – 28 Weeks
  • Ask for presenting complaints
  • Date of 1st foetal movements
  • Vaginal bleeding
  • Social: smoking, alcohol/drugs
  • TB screening
  • Intimate partner violence
  • General exam
  • BP
  • SFH (Symphysis Fundal Height)
  • Abdominal exam
  • Rule out multiple pregnancy
  • Nutritional assessment
  • Early Ultra Sound Scan (best at 20 weeks but can be done up to 24 weeks)
  • Hb at 26 weeks
  • If BP ≥140/90
  • Urine albumen, if there is glycosuria refer to hospital for GTT
  • Address presenting complaints
  • Discuss Laboratory results and need to treat partner where necessary
  • Symptoms of PIH, vaginal bleeding
  • eMTCT/HCT
  • LLINs/IPTp use
  • Danger Signs
  • Nutrition & Hygiene, Rest and exercise
  • Male involvement
  • Birth and emergency preparedness plan
  • Td
  • Ferrous SO₄
  • Folic acid
  • IPT dose
  • Mebendazole
  • Treat incidental ailments
  • Use of condoms in high risk individuals/discordant
  • Debriefing mother
  • Give next appointment and explain what will be done, emphasising need to come back any time if there is need
4th, 5th, 6th, 7th & 8th CONTACT

Third Trimester
(29 – 40 weeks)
  • Check foetal growth
  • Exclude anaemia
  • Assess for signs of PIH
  • Review birth and emergency preparedness plan
  • Exclude abnormal presentation/lie
  • Review delivery plan
Contact 4: 30 weeks
Contact 5: 34 weeks
Contact 6: 36 weeks
Contact 7: 38 weeks
Contact 8: 40 weeks
  • Ask for problems/ complications
  • Vaginal bleeding
  • Fetal movements
  • Intimate partner violence
  • General exam
  • Rule out anaemia
  • Nutritional assessment
  • BP
  • Abdominal exam
  • Obstetric (SFH)
  • Check lie presentation
  • If BP ≥140/90
  • Urine albumen
  • Hb at 36 WOA (Weeks of Age)
  • Midstream gram staining to rule out Asymptomatic Bacteruria at 34 weeks
  • Repeat HIV testing and Viral as per current guidelines (36 weeks)
  • Address problems
  • Discuss signs of labour/ PROM
  • Discuss vaginal bleeding
  • Review delivery plan
  • PMTCT/HTS
  • LLIN/IPTp use
  • Postpartum FP
  • Sex and other postpartum Care
  • Infant Feeding
  • Danger signs
  • Nutrition & Hygiene, Rest and exercise
  • Male involvement
  • Cervical cancer screening
  • Ferrous SO₄
  • Folic acid
  • IPT dose
  • Treat incidental ailments
  • Treat presenting ailments based on lab findings
  • Use of condoms in high risk individuals/discordant
  • Debriefing mother
  • Review and modify birth and emergency preparedness plan

⚠️ Note on Post-Term Pregnancy

If the mother has not delivered by 41 weeks, immediately report and refer to the nearest fully equipped health facility for further evaluation and induction of labour.

3. Risk Factors During Pregnancy

The following conditions are considered to have an adverse effect on the course and outcome of pregnancy and are strictly categorized as risk factors:

A. Conditions Likely to Recur and Cause Bleeding

  • Previous hemorrhage (Antepartum Hemorrhage - APH, Postpartum Hemorrhage - PPH, retained placenta).
  • Too many pregnancies (Grand multiparity of 5 or more).
  • Anemia.
  • Multiple pregnancy.
  • Previous uterine scar (e.g., from a previous Caesarean section).

B. Conditions That Affect Intrauterine Fetal Growth (May Cause Abortion or Prematurity)

  • Pre-eclampsia.
  • Anemia and Malnutrition.
  • HIV infection.
  • Malaria, smoking, and maternal underweight due to malnutrition.
  • Births spaced less than 2 years apart.
  • Diabetes.
  • Multiple pregnancy.
  • Excessive alcohol consumption.
  • Sickle cell disease.
  • History of abortion in the last 3 months.

C. Conditions That Pose Risk of Infections to Mother and Baby

  • HIV infection.
  • STIs (e.g., Syphilis, Gonorrhea).
  • Early/Premature rupture of membranes (PROM).
  • Diabetes mellitus.
  • Malaria.

D. Conditions Where Delivery May Have to be Assisted (C-Section or Vacuum Extraction)

  • Short stature (below 150 cms).
  • Young primigravida (below 18 years).
  • Elderly primigravida (above 35 years).
  • Previous uterine scar.
  • Cardiac disease or Diabetes mellitus.
  • Injury or deformity of the pelvis and lower part of the spine.
  • Severe pre-eclampsia and eclampsia.

E. Other Critical Conditions

  • Conditions likely to Recur: Abortion, Stillbirth, Premature delivery, Eclampsia.
  • Conditions likely to Worsen with Pregnancy: Renal disease, Mental illness, Epilepsy, Pulmonary tuberculosis, Heart disease, AIDS, Diabetes mellitus.
  • Conditions causing Social Discomfort: Lack of support from partner/family, Gender-Based Violence (GBV), Low socio-economic status, Unwanted pregnancy.
  • Conditions likely to cause Abnormalities or Disease to the Baby:
    • Maternal age above 35 years.
    • STDs such as Syphilis, HIV infection, etc.
    • Teratogenic drugs used to treat maternal conditions (e.g., Tetracycline, Methotrexate, Efavirenz, Ciprofloxacin).
    • Alcohol consumption and smoking (including passive smoking).
    • Genetic diseases (e.g., Hemophilia, Sickle cell disease).

Common Problems That May Complicate Pregnancy

  • Anemia.
  • Malaria.
  • STDs (including HIV, Gonorrhea, Syphilis, Vaginal/vulvar warts).
  • Urinary Tract Infections (UTIs).

4. Roles of Health Workers & Services Offered During ANC

Roles in Reducing Dangers of Risk Factors

  • Health Education: Targeted at the community and pregnant women, giving them sufficient time to express their concerns and discuss them openly.
  • Identification: Detecting pregnant women at risk of recurrent conditions or developing complications (such as pre-eclampsia, eclampsia, cephalo-pelvic disproportion) and referring them appropriately.
  • Birth Planning: Discuss the birth plan and emergency preparedness with the mother and another person of her choice.
  • Management Preparation: Prepare thorough management of the pregnancy.
  • Appropriate Referral: Prompt referral of women presenting with identified risk factors.

Services Offered During Antenatal Care

A comprehensive ANC visit must rigorously include the following 12 services:

  1. Health education.
  2. Professional Counseling.
  3. Screening and risk assessment through: History taking, General and abdominal examination, Investigations, Vaginal pelvic examination (where applicable), and STI testing (including HIV).
  4. Provision of hematinics (iron and folic acid).
  5. Deworming.
  6. Immunization against tetanus (TT).
  7. Intermittent Presumptive Treatment (IPT) of malaria.
  8. Early recognition, management, and referral of high-risk mothers and those developing complications.
  9. A delivery and postpartum care plan drafted for every woman.
  10. Treatment of medical conditions (e.g., malaria, hypertension, diabetes, STIs, Pulmonary tuberculosis).
  11. PMTCT / EMTCT services for HIV-positive mothers.

Facility Requirements for ANC Clinics

In order to effectively offer these services, the clinic must physically have at least the following:

  • Waiting Room: A space where mothers assemble for antenatal education, including a reception table and comfortable benches for clients.
  • Examination Room: Must provide strict privacy and contain a stable, firm examination couch.
  • Essential Equipment: Weighing scale, height measure (in cm), tape measure, clinical thermometer, urine testing kits, BP machine, stethoscope, and a fetoscope.
  • Small Laboratory: Capable of screening for common problems such as anemia, hookworm infestations, syphilis, pre-eclampsia, and diabetes.
  • Essential Drugs: Spelt out for the health centre, including vaccines (TT), SP (Fansidar), hematinics, and EMTCT drugs for HIV/AIDS.

It is highly recommended that mothers attend ANC as early as possible (preferably within the first 16 weeks). ANC should be integrated into other family health services, offered daily, and supported by outreach ANC services on specified days known to the public.

5. Health Education in ANC

Aims: To provide clients with vital information that will help a pregnant woman ensure that she remains completely healthy throughout pregnancy and delivery.

Key Messages for Health Education

  • Services offered to pregnant women during ANC and the benefits of attending.
  • How to keep healthy during pregnancy (nutrition, hygiene, rest).
  • STIs and their dangerous effects on pregnancy and the newborn.
  • Malaria prevention and its severe complications during pregnancy.
  • Minor disorders of pregnancy and effective ways to cope with them.
  • Proper diet during pregnancy and lactation.
  • Danger signs during pregnancy and labour.
  • Identifying pregnant women who must be attended to and delivered in a hospital.
  • The immense benefits of family planning and the different options available.
  • Identifying women who are likely to get problems if they become pregnant again too soon.
  • Exactly what to prepare for delivery (Maama Kits, baby clothes).
  • The signs of true labour.
  • Benefits of delivery under a skilled provider in a sanitary health unit.
  • Family planning methods specifically suited for postpartum mothers.
  • The importance of Postnatal Care.
  • The lifelong benefits of exclusive breastfeeding.

🧠 Memory Aid for Conducting Health Education

I-A-S-D-A-E-S-G-A-A-T (11 Steps):
Introduce self > Acknowledge leaders > State purpose > Deliver content > Allow Q&A > Evaluate > Summarize > Give follow-on info > Allow topic selection > Announce next > Thank the group.

Steps in Planning and Conducting Health Education

1. Planning the Session

  • Identify the target group.
  • Identify the specific needs of the target group (e.g., present knowledge/practices in Reproductive Health, priority messages related to local problems).
  • Choose the best media approach and language.
  • Identify resources: Community leaders, influential supporters (e.g., old acceptors of RH services), relevant visual aids, and a conducive venue.

2. Preparation Phase

  • Prepare the venue to ensure it is conducive for delivery.
  • Notify the target group through community leaders.
  • Prepare yourself thoroughly.
  • Identify satisfied clients to act as testimonials.
  • Prepare influential supporters.
  • Prepare materials and visual aids.
  • Prepare the exact contents and the channels for delivering it (e.g., a song, a skit, or a direct talk).

3. Steps in Conducting the Session

  1. Introduction of self and colleagues.
  2. Acknowledge leaders and the group present.
  3. State the purpose of the session in a stimulating way (e.g., use a slogan, poster, or short story).
  4. Deliver the content, allowing the group to actively participate and using visual aids where appropriate.
  5. Allow time for questions and answers.
  6. Evaluate the session using simple methods (observe participation, ask questions to test understanding, gauge their feelings, and ask how they will use the knowledge).
  7. Summarize the key points.
  8. Give follow-on information (e.g., exactly where one can obtain individual attention).
  9. Allow the group to select a topic among Reproductive Health topics for the next visit.
  10. Announce where and when the next session will be held.
  11. Thank the group for participating.

6. Antenatal Risk Assessment (The Booking Visit)

This is an intensive evaluation carried out on pregnant women during the antenatal period to screen them for probabilities of developing poor pregnancy outcomes, detect illnesses, and manage complications as they arise.

First Antenatal Visit / Booking Visit: The main purpose is to obtain baseline information against which all subsequent findings in the woman will be assessed. This is achieved through three main pillars: History Taking, Physical Examination, and Investigations.

A. History Taking

This must be done in a proper, orderly, and respectful manner to accurately assess the health status of the mother and fetus.

  • Demographics: Name and place of residence (specifically noting the accessibility to medical and maternity care).
  • Age & Parity: Note high-risk ages (below 18 and above 35 years). Note parity, specifically flagging young/elderly primigravidas, grand multiparas (above Para 4), and closely spaced pregnancies (less than 2 years between).
  • Social History: Inquire if married, source of financial/social support, educational status, history of genital mutilation (where applicable), alcohol/smoking habits, and the overall health of the partner.
  • Medical History: Inquire deeply about hypertension, renal disease, epilepsy, diabetes mellitus, sickle cell disease, asthma, TB, and HIV. Check surgical history (operations, blood transfusions, skeletal deformities, fractures of pelvis/spine/femur).
  • Obstetric/Gynecological History: Outcomes of previous pregnancies (e.g., previous C-sections, retained placenta, PPH, stillbirth, prolonged labour, early maternal death, ectopic pregnancies, D&C, APH, pre-eclampsia).
  • Family History: Ask about hypertension, diabetes, twins, or sickle cell disease in her family.
  • Menstrual & Contraceptive History: Age at menarche, length/regularity of cycle, duration/amount of flow. Record use of modern contraceptives and exact dates of discontinuation.
  • History of Present Pregnancy: Obtain the first day of the LNMP to calculate the EDD (Expected Date of Delivery). This guides the provider to compare amenorrhea weeks with fundal height. If over 20 weeks, note the date of quickening. Probe deeply into problems encountered (bleeding, vomiting, hospitalization, HIV status, fever, cough, diarrhea).

B. Physical Examination (General and Abdominal)

A physical examination from head to toe must be performed, carefully noting the nutritional state and any illness unrelated to pregnancy.

General Examination

  • Measure Weight: Note those underweight (below 45 Kg) and overweight (above 80 Kg).
  • Measure Height: Note those below 150/159 cm and visually check for skeletal deformities or limping.
  • Take Blood Pressure: Note those with BP of 140/90 mmHg and above.
  • Check for Anemia and Jaundice: Examine the conjunctiva, tongue, palms, and capillary refill in nail beds.
  • Check for Oedema: Inspect feet, hands, face, and the sacral area.
  • Perform a systematic examination of the respiratory and cardiovascular systems to entirely exclude abnormalities.
  • Examine Breasts: Look for masses or signs of malignancy. Educate the woman on nipple care and teach self-breast examination.
  • Assessment of Physical Abuse: Look for signs of drug abuse or unexplained bruising.
  • Assessment of any general physical complaints.

Abdominal Examination

  • Inspect: The abdomen must be adequately exposed. Note size, shape, presence of fetal movements, and importantly, any scar that may indicate a previous uterine operation.
  • Palpate: Note the presence of an enlarged liver, spleen, or tenderness in the renal angles. Measure the Height of Fundus and compare it precisely with gestational weeks. (Excessive enlargement indicates multiple pregnancy or polyhydramnios). Determine the lie, presentation, position, tenderness, and estimate liquor volume.
  • Auscultate: Listen to the fetal heart, meticulously noting the rate, volume, and rhythm.

Inspection of the Vulva

  • Done to detect lesions, scars (on perineum/vulva), or abnormal discharge. If abnormal discharge is detected and lab facilities exist, take a specimen. If no lab exists, immediately use the STI syndromic approach to provide treatment.

💡 Quick Practice Check

Question: During the abdominal examination of a mother at 32 weeks, you notice the Symphysio-Fundal Height (SFH) is measuring at 38 weeks. What two major obstetric conditions should immediately come to your mind based on this "excessive enlargement"?

Answer: Multiple Pregnancy (e.g., twins) or Polyhydramnios (excessive amniotic fluid).

C. Laboratory Investigations

  • Baseline Investigations (Routine):
    • Hb (Hemoglobin) - Normal is 10.5–15gm/dl.
    • Blood Group (ABO and Rhesus factor).
    • Urinalysis (Checking for protein to rule out pre-eclampsia, and sugar for diabetes).
    • VDRL / RPR (Testing for Syphilis).
  • Special Investigations (Refer when necessary):
    • Rhesus antibodies for RH-negative mothers.
    • Random Blood Sugar (if there is a history or presence of glycosuria).
    • Mid-stream urine for culture and sensitivity.
    • High Vaginal Swab (HVS).
    • Elisa test for HIV.
    • Sickling test.
  • Other Interventions:
    • Provide Tetanus Toxoid (TT) to complete the schedule. This routinely protects both mother and neonate from fatal tetanus.
    • Thoroughly explain to the mother the critical importance of tetanus immunization.

7. Recording, Assessing Findings, and Planning For Management

  • After the examination, ALL findings must be meticulously recorded on the ANC client's card and the clinic register.
  • Review all findings from the history, physical examination, and lab investigations.
  • Share plans and next steps clearly with the client.
  • If the woman must be referred, a detailed referral note must be filled out, handed to the client, and she must be explicitly explained where to go for further management.

⚠️ Attention: Referral Protocols

The health worker must refer a patient to a facility that is definitively able to handle the identified obstetric condition to avoid wasting the patient's time and transport costs. The health worker, alongside relatives, should organize a quick means of transport. If applicable, a health worker should escort the mother.

Conducting Follow-Up Visits

Purposes of Follow-up:

  • Monitor the strict progress of the pregnancy and the well-being of the mother and fetus.
  • Identify and rapidly manage arising conditions (STIs, HIV risks, pre-eclampsia, anemia, syphilis).
  • Provide ongoing information on birth planning, newborn preparation, postpartum care, and family planning.
  • Provide an opportunity to deal with the woman’s growing concerns.

Frequency of Follow-Up Visits:

  • Routine Schedule:
    • Every 4 weeks until 30 weeks.
    • Every 2 weeks until 36 weeks.
    • Every week until delivery.
  • High-Risk Schedule: Visits must occur much more frequently if the mother has past or present risk factors, such as:
    • Late vaginal bleeding during the current pregnancy.
    • Unsure of dates and booked late.
    • Past history of pre-eclampsia, premature labour, or abnormally small/large gestations.
    • Not gaining weight, or the fundal height is completely stagnant (not growing).
    • Gaining weight excessively (sign of severe oedema/pre-eclampsia).

Quick Quiz

ANC Quiz

Reproductive Health - mobile-friendly and focused practice.

Privacy: Your details are used only for quiz tracking and certificates.

Antenatal Care in Reproductive Health Read More »

delays in Safe Motherhood
Home > Reproductive> Delays, Mortality & Preconception Care

Delays in Safe Motherhood, Maternal Mortality & Preconception Care

Delays in Safe Motherhood Mean Death. Many women die due to fatal delays at several levels while seeking medical help. The community and health workers must work hand in hand to prevent this delay. Addressing this problem directly reduces maternal death and promotes safe motherhood.

This comprehensive module covers the root causes of these delays, the high incidence of maternal and perinatal mortality and morbidity (specifically in Uganda), and the preventative power of rigorous Preconception Care.

The 3-Delay Model: Causes of Delay in Acquiring Medical Care

In most instances, women who die in childbirth have experienced at least one of the following three delays. Understanding these specific barriers is critical for any midwife.

1. Delay in Decision Making (Seeking Care)

This delay occurs at the level of the individual woman, her family, and the community. It involves the inability or hesitation to make a timely decision regarding life-threatening health conditions.

  • Lack of Information: Ignorance or lack of knowledge regarding the health services available, or late recognition that a physiological problem (danger sign) actually exists.
  • Communication & Physical Barriers: Communication barriers in language, or extreme physical barriers such as mountains, lakes, or impassable bad roads that discourage the family from attempting the journey.
  • Lack of Resources: The family has absolutely no money, or the husband is away, and immediate transport cannot be secured to take the mother to the hospital.
  • Inappropriate Care: The mother is taken to an untrained Traditional Birth Attendant (TBA) first, wasting critical hours before hospital referral is considered.
  • Lack of Decision-Making Autonomy: The mother cannot make the decision to leave the house independently; she is forced to wait for her husband to return to give her explicit permission and money.
  • Fear: Deep-seated fear of the hospital environment, fear of the costs that will be incurred there, or fear of poor treatment by medical staff.

2. Delay in Reaching the Health Facility

Once the decision is made, the next hurdle is physically accessing the services.

  • Vast Distances: The sheer geographical distance may delay the mother so much that by the time she reaches the hospital, it is too late to reverse the complication (e.g., severe hemorrhage).
  • Lack of Transport: A vehicle or ambulance may simply not be available in the village to take the mother quickly to the hospital.
  • Poor Road Networks: Roads may be completely bad, muddy, or impassable, taking a drastically longer time to reach the hospital.
  • Exorbitant Transport Costs: The cost of hiring private transport in an emergency is often far too high for the mother or her family to afford.

3. Delay in Receiving Adequate Care at the Facility

The woman has arrived, but institutional failures cause fatal delays in intervention.

  • Unskilled Staff: Health workers who lack the necessary obstetric knowledge, skills, or confidence to deal with high-risk pregnancies and emergencies.
  • Lack of Essential Drugs: Life-saving drugs may not be available in the health units. This includes a lack of blood for transfusion, IV antibiotics, anticonvulsants, and analgesics.
  • Lack of Equipment: Absence of sterile supplies which may delay a vital Cesarean section, or a simple lack of syringes which delays the administration of life-saving oxytocic drugs.
  • Limited Service Varieties: Few varieties of comprehensive emergency obstetric services offered at the specific health facility, requiring a secondary referral.

Specific Factors That Affect the Delay to Seek Medical Care

  • Family Dynamics: The mother may be single or young and does not know whether she is pregnant, or she fears going to the health unit. Mothers-in-law may cause delays by attempting to manage the labour using traditional herbs for contractions.
  • The Husband: He may take too much time to decide, or he may be far away looking for money.
  • Education Level: If lowly educated, the mother may not even think of seeking professional medical advice.
  • Socio-Economic Status: Severe poverty prevents quick action, as all medical and transport steps require funding.
  • Natural Barriers: Geographical obstacles like rivers, lakes, mountains, and seasonal floods.
  • Security: Outbreaks of wars, insurgencies, or civil unrest making travel impossible.

Maternal Mortality

Definition: Maternal mortality is the death of a woman/mother while pregnant or within 42 days of the termination of pregnancy, irrespective of the duration and the site of the pregnancy, from any cause related to or aggravated by the pregnancy or its management (but not from accidental or incidental causes).

Maternal Mortality Rate (Ratio): This is the ratio of the total number of maternal deaths occurring in a period of time (usually a year) to the total number of live births occurring in the same period, expressed as a percentage, or per 1,000, or per 100,000.

Global and Local Incidence

  • Worldwide, every year approximately 8 million women suffer from pregnancy-related complications.
  • Over half a million of them die as a result.
  • The problem is greatest (99%) for poor women in developing countries. One woman out of 11 may die of pregnancy-related complications in developing countries, compared to 1 in 5,000 in developed countries.
  • For every 1 maternal death, at least 16 more women suffer from severe morbidities.
  • Note on Newborns: Not only mothers die; babies die too. 4,000,000 newborn deaths occur globally, yet almost all are due to preventable conditions.
  • Ugandan Context: The maternal mortality rate in Uganda has been declining over the years, from 506/100,000 in 2004 to 435/100,000 in 2011. Recent data shows that 16 women die every day during giving birth in Uganda. While the WHO reports a 44% worldwide decrease due to MDGs, developing countries like Uganda have not seen as drastic a difference.

Factors Contributing to High Maternal Mortality in Uganda

There is no single factor responsible for the high maternal mortality in Uganda. It is an interplay of the following factors:

  • Poverty: Several women engage in unpaid productive work at home. They cannot afford simple transport costs during emergencies or basic human needs like nutritious food, predisposing them to complications and denying them adequate housing and ANC.
  • Gender Issues & Inequality: Men are the sole decision-makers. Women must wait for a man's permission to seek care. Some are entirely prevented from attending ANC by their husbands.
  • Inadequate & Inaccessible Health Services: Very few facilities are fully equipped. Despite government policies, women still travel vast distances to access care, keeping unwell women away.
  • Limited Health Workers: A skyrocketing population against a low number of trained workers results in massive daily queues. Discouraged mothers often leave and prefer traditional village healers who lack emergency skills.
  • Poor Attitudes of Health Workers: Health workers are frequently reported as rude, arrogant, and unfriendly. This scares women away, forcing them into the hands of untrained people.
  • Early Marriages: The girl child is viewed as a source of family wealth (cattle/money). Forced into marriage at a tender age before their bones and bodies are fully developed, they are highly predisposed to severe labour complications.
  • Illiteracy: High illiteracy means women cannot influence policy or stand up for their rights. Education empowers girls, keeps them in school until they are old enough to marry, and reduces pregnancy rates.
  • Harmful Beliefs, Customs, and Taboos: Denying pregnant women nutritious foods (like chicken/eggs) causes malnutrition. Female Genital Mutilation (FGM) causes extensive hemorrhage. Use of traditional cytotoxic herbs causes uterine ruptures. Communities often stigmatize hospital deliveries as a sign of "weakness."
  • Poor Transport & Communication Infrastructure: 75% of Ugandans live in rural areas with poor road networks, delaying emergency transfers (especially in mountainous Kigezi or areas encircled by water).
  • High Child Mortality: Uncertain if their children will survive to adulthood, parents produce many children so a few survive (e.g., in post-war Northern Uganda).
  • Desire for More Children & Sex Preferences: Children are a source of prestige. Families desire many children, or keep delivering in an attempt to get a specific sex, heavily multiplying the mother's lifetime risk of death.
  • High Fertility Rate: Uganda has one of the highest fertility rates globally (approx. 7 children per woman). This exposes women to obstetric risks many times over.
  • Underutilization of Existing Services: Ignorance and lack of awareness lead to poor usage of the facilities that do exist.
  • Systemic Failures: Inadequate drug supplies, poor referral systems, disrespect for human rights, and deep gender stereotypes.

Causes of Maternal Mortality

A Direct death is one resulting from obstetric complications of pregnancy, delivery, or from interventions, omissions, incorrect treatment, or a chain of events resulting from any of the above.

An Indirect death is one resulting from a previously existing disease (or a disease developed during pregnancy) that was not due to obstetric causes but was aggravated by the physiological effects of pregnancy.

Direct Causes of Maternal Mortality

  • i) Sepsis: A very common cause. Results from early rupture of membranes, dirty delivery environments (like gardens), or compromised aseptic techniques during C-sections. Action: Prophylactic antibiotics must be given after C-sections or prolonged labour.
  • ii) Hemorrhage: Extremely serious, especially in women with underlying anemia. Presents as Antepartum Hemorrhage (APH), placental retention, or uterine inertia. Action: Micronutrient supplements during pregnancy, anemia screening, and booking blood for labour.
  • iii) Early Pregnancy Deaths: Resulting from ectopic pregnancies and abortions. Criminal/unsafe abortions account for the highest number of deaths in this category in Uganda.
  • iv) Hypertensive Conditions: Severe pre-eclampsia and eclampsia. Action: Magnesium sulphate is the drug of choice. Ensure proper fluid management and early identification during ANC.
  • v) Others: Thrombosis, thrombo-embolism, and genital trauma (e.g., uterine rupture).

Indirect Causes of Maternal Mortality

  • i) Cardiovascular diseases: Pulmonary hypertension and Endocarditis.
  • ii) HIV/AIDS
  • iii) Malnutrition
  • iv) Diabetes
  • v) Thyroid diseases
  • vi) Severe Anemia

Predisposing Factors

Early pregnancy (less than 20 years old), uncontrolled fertility, low socioeconomic status, poverty, lack of female empowerment, lack of access to quality services, inadequate referral systems, and absolute lack of support from spouses.

Prevention of Maternal Mortality

Eighty percent (80%) of these deaths can be completely prevented through coordinated, long-term actions within families, health systems, and national legislation.

1. Primary Prevention

  • Girl Child Education: Keeps girls in school, delays marriage, reduces pregnancies, and empowers them to demand employment and health rights.
  • Proper Nutrition of the Girl Child: Prevents childhood malnutrition, which causes contracted pelvises and leads to severe Cephalopelvic Disproportion (CPD) during future labour.
  • Family Planning: Eliminates unwanted pregnancies and criminal abortions. Enables couples to have children by choice, not by chance, avoiding the extreme risks of teenage pregnancies.
  • Quality Antenatal Care: Timely attendance of at least 4 quality ANC visits to fully assess and properly manage any risk factors.
  • Immunization: All women of reproductive age must be immunized against Tetanus and Hepatitis B.
  • Information, Education, and Communication (IEC): Educating families on the specific causes of maternal mortality so individuals take proactive action rather than solely relying on the government.

2. Secondary Prevention

  • A skilled attendant must be present at every single birth, supported by a functional referral system.
  • Emergency Obstetric Care (EmOC) services must be provided and easily accessible.
  • Improvement of transport networks and readily available ambulances.
  • Equipping health facilities with functional operating theaters, blood storage, and a steady supply of essential drugs.
  • Adequate referral systems so clients do not decline transfers out of fear of inadequate help at the next level.
  • Proper evaluation and prompt reporting of maternal deaths (Maternal Death Audits).
  • Decentralization of health services to make them available to rural women.
  • Removal of barriers and implementation of policies that increase women's decision-making power.
  • Recruitment of skilled staff to balance the workload, and organizing continuous refresher courses to improve the standard of care.

3. Tertiary Prevention

  • The immediate control, medical management, and treatment of complications once they have already arisen (e.g., repairing severe lacerations or managing shock).
  • Comprehensive Emergency Obstetric Care (CEmOC) interventions.

Maternal Morbidity

While death gets the most attention, maternal morbidity destroys lives. It is estimated that for every one maternal death, at least 15 more women suffer from severe morbidities. An optimistic 5 to 7 million women suffer a severely impaired quality of life from short-term or long-term disability.

Definition: Obstetric morbidity originates from any cause related to pregnancy or its management at any time during the antepartum, intrapartum, and postpartum periods (usually up to 42 days after confinement).

Parameters of Maternal Morbidity

  • Fever greater than 38°C
  • Blood pressure greater than 140/90 mmHg
  • Recurrent vaginal bleeding
  • Hemoglobin (Hb) less than 10.5 g/dl irrespective of gestational age
  • Asymptomatic bacteriuria of pregnancy

Classifications of Morbidity

  • Direct Temporary (Mild): APH, PPH, eclampsia, obstructed labour, ruptured uterus, sepsis, ectopic pregnancy, and molar pregnancy.
  • Direct Permanent (Chronic): Vesico-vaginal fistula (VVF), rectovaginal fistula (RVF), severe dyspareunia (painful intercourse), uterine prolapse, secondary infertility, and obstetric palsy.
  • Indirect Morbidity: These conditions are expressions of previously existing diseases (like malaria, hepatitis, tuberculosis, anemia) that are heavily aggravated by the physiological changes of pregnancy.

Perinatal Mortality

Definition: Deaths among fetuses weighing 1000g or more at birth (greater than 28 weeks gestation) that die before or during delivery, or within the first 7 days of delivery. According to the WHO, the absolute limit of viability is a fetus weighing 500g (22 weeks).

The Perinatal Mortality Rate (expressed per 1000 total births) closely reflects the standards of medical care and the effectiveness of a country's social health measures.

Incidence

  • Worldwide, nearly 4 million newborns die within the first week of life, and another 3 million are stillborn.
  • Perinatal deaths could be reduced by at least 50% worldwide if key interventions are applied.
  • In developed countries, it is less than 10 per 1000 total births; in developing countries, it is drastically higher due to malnutrition, infections, unregulated fertility, and poor obstetric care.
  • The vast majority of fetal deaths (70-90%) occur before the onset of labour.

Predisposing Factors to Perinatal Mortality

  • a) Maternal Epidemiology: Maternal age over 35 years, teenage pregnancies, multiparity, poverty, and poor maternal nutritional status.
  • b) Medical Disorders: Severe anemia (Hb < 8g/dl), hypertensive disorders, syphilis, diabetes mellitus, malaria, other infections, prematurity, and fetal congenital malformations.
  • c) Obstetric Complications: Antepartum hemorrhage (abruptio placentae alone is responsible for 10% of perinatal deaths due to severe hypoxia), pre-eclampsia/eclampsia (causes placental insufficiency), Rhesus iso-immunization, and cervical incompetence (leading to premature effacement between 24-36 weeks).
  • d) Complications of Labour: Dystocia (from CPD, mal-presentation, abnormal uterine action) and Premature Rupture of Membranes (PROM) resulting in hypoxia, amnionitis, and birth injuries.
  • e) Feto-Placental Factors: Multiple pregnancies (leading to preterm delivery), congenital and chromosomal abnormalities (responsible for 15% of deaths), and Intrauterine Growth Restriction (IUGR).
  • f) Unexplained Causes: About 20% of stillbirths have absolutely no obvious fetal, placental, maternal, or obstetric causes.

Causes of Perinatal Mortality

  • Infection: Sepsis, meningitis, pneumonia, congenital neonatal tetanus.
  • Birth asphyxia and physical birth trauma.
  • Severe Hypothermia.
  • Prematurity and Low Birth Weight.
  • Fatal Congenital Malformations.

Control and Prevention of Perinatal Mortality

Every baby has a right to be born alive, safe, and healthy. Interventions include:

  • Pre-pregnancy healthcare, genetic counseling for high-risk cases, and prenatal diagnosis.
  • Regular ANC with advice on health, diet, and rest.
  • Early detection and management of maternal anemia, diabetes, and hypertension.
  • Mandatory hospital delivery screening for clients of poor socioeconomic status, high parity, or extreme age.
  • Careful monitoring of labour (partograph) to detect hypoxia or traumatic delivery early.
  • Skilled birth attendance to eliminate neonatal sepsis.
  • Provision of specialized neonatal referral services for preterm babies.
  • Health education on early, exclusive breastfeeding and the strict prevention of hypothermia.
  • Educating the community to fully utilize family planning and MCH services.
  • Increased resource allocation and improving social infrastructure (transport, roads).
  • Regular review of perinatal death cases (Perinatal Death Audits) and decentralization of MCH services.

Preconception Care

The outcome of a pregnancy depends immensely on the factors that operated during the entire period of growth and development of the mother from childhood. These include the circumstances surrounding her own birth, her birth weight, breastfeeding, childhood infections, formal education, socio-cultural practices, and reproductive health education.

Definition: Preconception care refers to the medical care and focus given to women and men during their reproductive years. It focuses on taking concrete steps now to protect the health of a baby they might have in the future. It is not just for those planning a pregnancy—it is about individuals getting and staying healthy overall, because unplanned pregnancies happen often.

Why is Preconception Care Important?

  • For Healthy Babies: It gives babies the absolute best chance for a healthy start. Babies are less likely to be born prematurely, have a low birth weight, or suffer from severe birth defects.
  • For Men: It means choosing to get healthy, protecting future children, and actively encouraging and supporting the health of their partner.
  • For Healthy Families: The health of a family relies entirely on the health of the people in it. Taking care of your health now ensures a better quality of life for the family in the coming years.

Objectives of Preconception Care

  • Assess clients' absolute readiness for pregnancy (mental, physical, and socio-economic readiness).
  • Prevent, treat, and aggressively manage medical conditions that negatively affect pregnancy and the newborn.
  • Prepare the body for a safe pregnancy and childbirth.
  • Promote safer and responsible sexual behaviors.
  • Promote the delay of the age at first pregnancy.
  • Prevent HIV and other sexually transmitted diseases.

Services Offered During Preconception Care

1. Education and Information

  • Sexuality, responsible parenthood, family planning, and STI/HIV prevention.
  • Growth and development of the coming child, and education on pregnancy/childbirth.
  • Malaria prevention, personal hygiene, and proper nutrition.
  • The dangers of drug abuse and unprescribed medicine use during pregnancy.
  • Education on managing previous health interventions (e.g., repair of VVF, ruptured uterus, infertility treatments, diabetes).

2. Screening and Managing Conditions

  • Routine screening for HIV, Syphilis, Sickle cell diseases, Heart disease, Hypertension, Diabetes Mellitus, severe Anemia, and Mental illness.
  • Screening for genetic congenital abnormalities.

3. Provision of Direct Medical Services

  • Folic acid supplementation: Given for 3 months before pregnancy to prevent neural tube defects.
  • Routine Immunization and Deworming for women.
  • Management of STI/STDs and provision of long-lasting insecticide-treated nets (LLINs).
  • Routine screening for reproductive health cancers (e.g., Pap smears for cervical cancer).
  • Provision of Family Planning and VCT for HIV.

4. Support Channels

  • Identifying and locating organizations that will support community groups.
  • Appropriate counseling of individuals and couples about their specific pregnancy needs.
  • Establishing a pre-pregnancy health profile for the purpose of long-term follow-up.
  • Identifying special groups (e.g., women with disabilities, adolescents, and HIV-infected women) and developing appropriate interventions for them.
  • Mobilizing and sensitizing the community to be highly supportive of the needs of these special groups.
  • Promoting responsible motherhood, fatherhood, and contraception information.

Where Preconception Care is Done and How to Reach Out

Preconception care is heavily conducted in Health Units and through Community-based groups. The best ways to reach out to special groups include:

  • Direct health education in the community.
  • Mass media campaigns (Radio/TV).
  • Church and religious groups.
  • Appropriate ITC (Information, Technology, and Communication) materials.
  • Engagement of powerful community opinion leaders.

📚 References & Further Reading

  • World Health Organization (WHO). (2017). Trends in Maternal Mortality: 1990 to 2015.
  • United Nations Population Fund (UNFPA) & World Bank. The Safe Motherhood Initiative (1987).
  • AbouZahr, C. (2003). Safe Motherhood: A brief history of the global movement 1947–2002. British Medical Bulletin.
  • Uganda Demographic and Health Survey (UDHS). (2006 & 2011). Maternal and Infant Health Indicators.
  • World Health Organization (WHO). The Mother-Baby Package: Implementing safe motherhood in countries.
  • McGowan, J. (2017). Strategies of the Safe Motherhood Initiative.
  • Global Strategy for Women's, Children's and Adolescents' Health (2016-2030) - Sustainable Development Goals (SDGs).

Quick Quiz

Delays Quiz

Reproductive Health - mobile-friendly and focused practice.

Privacy: Your details are used only for quiz tracking and certificates.

DELAYS IN SAFE MOTHERHOOD Read More »

Obstetrical Emergencies
Home > Reproductive > Obstetrical & Pediatric Emergencies

Obstetrical and Pediatric Emergencies

Obstetrical Emergency: This is a life-threatening situation where the life of the mother and/or the fetus is in imminent danger of death or severe morbidity, and immediate, swift medical intervention must be carried out to save lives.

Pediatric Emergency: Conditions where the life of a newborn or child (from birth up to 5 years of age) is in critical danger due to birth complications, congenital issues, severe infections, or environmental hazards.

For both categories, the midwife's ability to take quick action, provide immediate emergency treatment, and initiate proper, timely referral systems dictates the survival outcome.

1. List of Obstetrical Emergencies

A midwife must instantly recognize and respond to the following critical emergencies. (Expanded with brief clinical contexts):

  • Antepartum Hemorrhage (APH): Severe vaginal bleeding occurring after 28 weeks of gestation but before delivery (e.g., Placenta Previa, Placental Abruption).
  • Postpartum Hemorrhage (PPH): Excessive bleeding (500ml+ vaginally, 1000ml+ C-section) occurring after the birth of the baby.
  • Cord Prolapse: The umbilical cord descends through the cervix ahead of the presenting part, risking fatal fetal hypoxia.
  • Ruptured Uterus / Impending Rupture: Tearing of the uterine wall, often due to obstructed labour or previous C-section scars.
  • Fetal Distress: Severe compromise of the fetus, indicated by abnormal fetal heart rates (tachycardia or profound bradycardia) or thick meconium-stained liquor.
  • Vasa Previa: Fetal blood vessels cross or run near the internal opening of the uterus, risking massive fetal hemorrhage when membranes rupture.
  • Intrapartum Hemorrhage: Heavy bleeding occurring actively during the labour process.
  • Obstructed Labour: The presenting part of the fetus cannot progress into the birth canal despite strong uterine contractions (e.g., Cephalopelvic Disproportion).
  • Retained Placenta: Failure of the placenta to deliver within 30 minutes after childbirth, heavily predisposing the mother to PPH and sepsis.
  • Severe Pre-eclampsia and Eclampsia: Pregnancy-induced hypertension accompanied by proteinuria and progressing to life-threatening maternal convulsions (seizures).
  • Pulmonary Embolism: A sudden blockage in a lung artery, often by a blood clot (thrombosis) or amniotic fluid, causing sudden maternal collapse.
  • Severe Anemia: Critically low hemoglobin levels leading to heart failure or hypovolemic shock during delivery.
  • Inversion of the Uterus: The uterus turns inside out, often caused by mismanagement of the 3rd stage of labour (pulling the cord before separation).
  • Obstetric Shock: Severe collapse of the maternal circulatory system (Hypovolemic from bleeding, or Septic from profound infection).

2. Roles of a Nurse/Midwife in Obstetrical Emergencies

The midwife's roles are broadly categorized across the entire reproductive continuum to ensure prevention, early detection, and rapid intervention.

A. At The Community Level (Prevention & Preparedness)

  • Health Education: Educate the community about obstetric danger signs, emergencies, and their roles in prevention and management.
  • Supervise TBAs: Educate, supervise, and continuously evaluate Traditional Birth Attendants (TBAs) on safe practices during pregnancy, labour, and puerperium, ensuring they refer cases early.
  • Create Facility Awareness: Promote the use of available health facilities (dispensaries, clinics, maternity centers, hospitals).
  • Promote Clinic Attendance: Heavily encourage women to attend Antenatal (ANC), Intranatal, Postnatal (PNC), Young Child Clinics (YCC), and Family Planning clinics.
  • Women's Empowerment: Advise women to start self-help and income-generating projects to minimize total financial dependency on husbands, which often delays transport to hospitals.
  • Nutritional Advocacy: Help the community realize the critical importance of a well-balanced diet to prevent severe anemia and malnutrition.
  • Eradicate Harmful Practices: Actively discourage harmful traditional practices, early sex, child marriages, and boy-child preferences that expose girls to early, high-risk pregnancies.
  • Male Involvement: Educate husbands to take over tiring, heavy duties from pregnant wives to relieve them physically and psychologically.
  • Community Transport Readiness: Encourage communities to establish emergency transport funds or vehicles for immediate transfer during obstetric crises.

B. During Pregnancy (Antenatal Care)

  • Risk Identification: Identify High-Risk Pregnancies (HRP) early (e.g., twins, previous C-section, hypertension) that may end in obstetrical emergencies, and refer them to specialists in time.
  • Comprehensive Assessment: Conduct thorough history taking, physical examinations, and early laboratory investigations (Hb, Syphilis, HIV, Urinalysis) on every mother.
  • Birth Preparedness: Assist mothers in developing a clear Birth and Emergency Preparedness Plan, preparing them for labour and successful lactation.
  • Prompt Treatment: Treat minor disorders of pregnancy (e.g., hyperemesis gravidarum/morning sickness, urinary tract infections) promptly before they escalate.
  • Early Referral: Immediately refer mothers with serious conditions (e.g., pre-eclampsia, severe anemia) via proper referral pathways.

C. During Labour (Intrapartum Care)

  • Proper Admission: Welcome the mother warmly, provide reassurance, and offer counseling to reduce anxiety, which can prolong labour.
  • Thorough Assessment: Conduct proper history taking, physical, and obstetric examination on every mother upon admission.
  • Partograph Use: Strictly monitor the progress of labour, maternal vitals, and fetal condition using the Partograph to detect prolonged/obstructed labour early.
  • Early Detection: Detect danger signs instantly and summon for help (doctors or senior midwives) without delay.
  • Prevent Exhaustion: Avoid prolonged and exhausting labour by administering prescribed analgesics, reassuring the mother, preventing early pushing, and aggressively rehydrating her with IV fluids or oral sips.
  • Timely Episiotomy: Give a well-timed, assisted episiotomy in cases of assisted deliveries, mal-presentations, or malpositions to prevent severe, extended perineal tears and hemorrhage.
  • Infection Prevention: Strictly apply aseptic techniques and Standard Precautions throughout labour and delivery to prevent puerperal sepsis.
  • AMTSL: Ensure Active Management of the Third Stage of Labour (giving oxytocin, controlled cord traction, uterine massage) to critically prevent PPH.

D. After Delivery (Puerperium / 4th Stage)

  • 4th Stage Observation: Carry out extremely close observation of the mother's vitals, uterine tone, and vaginal bleeding during the critical first 2 hours postpartum to prevent and arrest primary PPH.
  • Health Education: Educate the mother extensively on:
    • Taking a well-balanced, iron-rich diet.
    • Exclusive breastfeeding on demand.
    • Performing postnatal pelvic floor and abdominal exercises.
    • Maintaining strict personal and environmental hygiene (vulval swabbing).
    • Returning for the 6-week postnatal review.
    • Attending family planning clinics to space pregnancies.
    • Bringing the baby to the YCC for the full immunization schedule.

3. General Management of Obstetric Emergencies

The survival of the mother heavily relies on standard principles applied universally across obstetric emergencies.

The Emergency Tray / Trolley

Absolute readiness is mandatory. Every maternity unit must have a fully stocked emergency tray containing:

  • Uterotonics (for bleeding): Ergometrine, Oxytocin (Pitocin), Misoprostol.
  • Anticonvulsants & Antihypertensives: Magnesium Sulphate (for Eclampsia), Diazepam, Hydralazine, Nifedipine.
  • Shock & Resuscitation Drugs: Hydrocortisone, Dexamethasone, Adrenaline, Atropine, Aminophylline, Digoxin.
  • Diuretics & Sugars: Mannitol, Lasix (Furosemide), Dextrose 5% and 50%.
  • Analgesics/Narcotics: Pethidine, Morphine.
  • Newborn Needs: Vitamin K injection.
  • Equipment: Oxygen cylinder with masks, Ambu bags, IV giving sets, Normal Saline/Ringer's Lactate, large-bore cannulas (Size 14G/16G), needles, and syringes.

Management Principles

  1. Stay Calm & Summon Help: The midwife must remain calm, act quickly, apply her knowledge, and immediately shout for extra staff/medical help.
  2. Prioritize (ABC): Start with the most urgent life-saving need first (e.g., securing Airway/Breathing, arresting severe hemorrhage, rapid IV rehydration, or immediate delivery of the baby).
  3. Rapid Assessment: Perform rapid, targeted history taking, physical examination, and vital investigations.
  4. Apply the Nursing Process: Deliver essential care systematically based on the specific emergency (e.g., manual removal of a retained placenta, neonatal resuscitation, applying anti-shock garments).
  5. Reassurance: Actively reassure the terrified mother and her anxious relatives to prevent psychological shock.
  6. Early Referral: Stabilize and prepare the mother for immediate transport. High-Risk Pregnancies diagnosed at lower health centers must be transferred early.

📝 The Comprehensive Referral Note

A detailed referral note saves the receiving doctor crucial time. It MUST include:

  • Date and precise Time of referral.
  • Detailed personal and obstetric history of the mother (Gravida, Para).
  • General condition on arrival and specific findings upon examination.
  • Exact treatment given (e.g., "IV Normal Saline 1L given, MgSO4 4g IV given at 10:00 AM").
  • The specific obstetrical management applied so far.
  • The exact reason for the referral (The presumptive diagnosis).
  • The condition of the mother and fetus at the exact time of dispatch.

4. Complications of Obstetrical Emergencies

Obstetrical emergencies expose the mother and fetus to severe morbidity and mortality, especially if management is delayed, wrongly applied, or if facilities lack proper equipment.

Complications to the MotherComplications to the Baby
Maternal DeathStillbirth / Neonatal Death
Hemorrhagic Shock (due to APH, PPH, Intrapartum bleeding)Severe Asphyxia Neonatorum leading to permanent brain damage
Severe Anemia leading to heart failureCerebral Palsy and Mental Retardation
Puerperal Sepsis / Septicemia (due to prolonged labour, retained placenta)Birth Injuries (e.g., Erb's palsy, fractures from instrumental deliveries)
Uterine Rupture resulting in immediate hysterectomy (loss of uterus)Premature deliveries and associated complications (Respiratory Distress Syndrome)
Secondary Infertility / Sterility (due to reproductive tract damage or severe infection)Intrauterine Fetal Growth Retardation (IUGR)
Venous Thrombosis / Pulmonary EmbolismLow resistance to infections (Neonatal Sepsis)
Puerperal Psychosis (Severe mental breakdown post-trauma)Failure to thrive
Amniotic Fluid EmbolismAbortion (pregnancy wastage)

5. Pediatric Emergencies

Definition: Pediatric emergencies are acute conditions where the life of the baby or young child (from birth up to 5 years of age) is in immediate danger of death or severe, permanent complications.

List of Pediatric Emergencies

  • Neonatal Asphyxia (Asphyxia Neonatorum): Failure to initiate or sustain spontaneous breathing at birth. Often resulting from intrauterine anoxia due to Cord Prolapse, prolonged labour, or APH.
  • Cerebral Damage / Birth Trauma: Intracranial bleeding or nerve damage occurring during traumatic, obstructed, or instrumental deliveries.
  • Hemorrhagic Disease of the Newborn: Severe bleeding due to Vitamin K deficiency.

Hazards as the Child Grows (1 to 5 Years)

As children gain mobility, they are exposed to life-threatening environmental hazards:

  • Swallowed Objects and Aspiration: Choking on coins, toys, or food (e.g., groundnuts) blocking the airway.
  • Poisons: Accidental ingestion of household chemicals, paraffin (kerosene), or adult medications.
  • Burns: Severe scalding from hot cooking liquids, porridge, or falling into open cooking fires.
  • Insect/Snake Bites: Severe allergic reactions (anaphylaxis) or envenomation.
  • Trauma: Falling from heights, severe cuts, head injuries, and bone fractures.
  • Acute Diseases: Sudden onset of febrile convulsions, severe dehydration from gastroenteritis, or acute respiratory distress.

6. Causes of Neonatal and Infant Mortality

Causes of Neonatal Morbidity and Mortality (0 - 28 Days)

  • Asphyxia Neonatorum: Lack of oxygen before, during, or immediately after birth.
  • Birth Injuries: Trauma inflicted during a difficult vaginal delivery.
  • Low Birth Weight (LBW) & Prematurity: Babies weighing less than 2.5kg, leading to severe vulnerability to cold and infections.
  • Hypothermia: Dangerous drop in newborn body temperature, often due to poor wrapping or delayed skin-to-skin contact.
  • Congenital Abnormalities: Severe birth defects (e.g., heart defects, neural tube defects).
  • Neonatal Sepsis: Massive systemic infections, including pneumonia, tetanus, meningitis, and septicemia.

Causes of Infant Mortality and Morbidity in Uganda (Up to 1 Year)

Uganda faces specific systemic challenges that drive infant mortality:

  • Malaria: Endemic across the country; infants rapidly develop severe anemia and cerebral malaria.
  • Diarrhea: Caused by poor sanitation and unsafe drinking water, leading to rapid, fatal dehydration.
  • Upper and Lower Respiratory Tract Infections (URTI / Pneumonia): Acute respiratory infections are massive killers of infants.
  • Measles: Highly contagious and often fatal for malnourished or unimmunized infants.
  • Severe Malnutrition: Kwashiorkor and Marasmus weaken the immune system, making minor infections fatal.

7. Management and Prevention of Pediatric Emergencies

Management heavily depends on the specific cause, but general emergency principles must be rapidly applied using the ABCDE approach (Airway, Breathing, Circulation, Disability, Exposure):

  • Resuscitation: Immediate clearance of the airway (suctioning) and ventilation (using Ambu bags) for asphyxiated newborns within the "Golden Minute."
  • Oxygen Therapy: Administer high-flow oxygen for respiratory distress, pneumonia, or severe malaria.
  • IV Rehydration: Immediately put up an IV drip (or Intraosseous line) for severe dehydration, hemorrhagic shock, or severe burns.
  • Poisoning Management: If a poison is swallowed, induced emesis (vomiting) is ONLY done if the substance is NOT acidic/corrosive (like paraffin). If corrosive, giving milk to drink may coat and protect the stomach lining while rushing to the hospital.

Prevention of Pediatric Emergencies

  • Health Education: Educate parents extensively on childproofing the home (keeping medicines, hot liquids, and paraffin out of reach).
  • Maternal Care: Since most neonatal emergencies stem directly from maternal conditions (e.g., APH causing asphyxia), superb management of High-Risk Pregnancies is the ultimate prevention.
  • Skill Mastery: Every midwife and nurse must have up-to-date, rigorous training and mastery of Neonatal Resuscitation (Life Saving Skills).
  • Immunization: Ensure 100% compliance with the UNEPI immunization schedule to eradicate measles, tetanus, and severe pneumonias.

📚 References & Further Reading

  • Fraser, D. M., & Cooper, M. A. Myles Textbook for Midwives (Latest Edition). Churchill Livingstone Elsevier.
  • World Health Organization (WHO). Managing Complications in Pregnancy and Childbirth: A guide for midwives and doctors.
  • Ministry of Health Uganda. Uganda Clinical Guidelines (UCG) - Sections on Obstetric and Pediatric Emergencies.

Quick Quiz

Obs Emergencies Quiz

Reproductive Health - mobile-friendly and focused practice.

Privacy: Your details are used only for quiz tracking and certificates.

Obstetrical Emergencies Read More »

High Risk Pregnancies
Home > Reproductive > High Risk Pregnancies

High Risk Pregnancies

A High Risk Pregnancy (HRP) is a pregnancy that is highly likely to end up with severe complications, the death of the mother, the death of the baby, or both. A mother identified with a high-risk pregnancy must be cared for and delivered in a well-equipped health unit under the direct supervision of a doctor or senior obstetrician.

  • Risk: This is the statistical possibility that a dangerous event will occur. It is used in reference to unavoidable events (e.g., getting pregnant when one has an underlying serious medical condition like diabetes, which automatically puts the mother's and unborn child's lives in danger).
  • Risk Factors: These describe anything which actually causes or directly increases the chances of a complication. For example, a severe illness like diabetes physically increases the chances of maternal morbidity and mortality.

Categories of High Risk Mothers

A midwife must be highly vigilant during history taking and physical examination to identify mothers who fall into the high-risk category. The following is a comprehensive list of mothers who are strictly considered high risk, along with the physiological reasons why:

  • 1. Young Primigravida (Age 16 and below): Their pelvic bones are often not fully mature and developed, leading to a high risk of Cephalopelvic Disproportion (CPD), obstructed labour, and severe pre-eclampsia.
  • 2. Elderly Primigravida (Age 35 and above): Increased risk of chromosomal abnormalities (like Down Syndrome), gestational diabetes, pregnancy-induced hypertension, and prolonged labour due to rigid pelvic joints.
  • 3. Grand Multigravida (Gravida 5 and above): High risk of uterine atony leading to fatal Postpartum Hemorrhage (PPH), uterine rupture, abnormal presentations, and placenta praevia.
  • 4. Mothers with 3 or more previous miscarriages: Indicates underlying issues such as cervical incompetence, chromosomal defects, or severe systemic diseases (e.g., syphilis, severe malaria).
  • 5. Mothers of short stature (153cm / 5ft and below): Highly associated with a contracted or small pelvis, leading to CPD and obstructed labour.
  • 6. Limping mothers: A limp often indicates a history of polio, rickets, or congenital hip dysplasia, which severely distorts the shape of the pelvis, making normal vaginal delivery impossible.
  • 7. Mothers with a history of pelvic fractures: Previous trauma can alter the pelvic brim and outlet diameters, obstructing the birth canal.
  • 8. Cephalopelvic Disproportion (CPD): When the baby's head is too large to fit through the mother's pelvis, necessitating a Caesarean section.
  • 9. Multiple Pregnancy (Twins, Triplets): High risk of severe anemia, pre-eclampsia, premature labour, malpresentations, and severe PPH.
  • 10. Mothers with Intrauterine Fetal Death (IUFD): A retained dead fetus can cause severe maternal bleeding disorders (Disseminated Intravascular Coagulation - DIC) and life-threatening sepsis.
  • 11. History of PPH on previous deliveries: A mother who has bled heavily before is at a statistically much higher risk of bleeding again.
  • 12. History of retained placenta on previous delivery: Indicates a risk of abnormal placental adherence (like placenta accreta) or recurring uterine atony.
  • 13. Pre-eclampsia, Eclampsia, or history of Post-Eclamptic Toxemia: Severe hypertension threatens the mother with convulsions, cerebral hemorrhage, and fetal hypoxia.
  • 14. Underlying Medical Conditions: Mothers with cardiac diseases (heart failure during pushing), renal diseases, essential hypertension, diabetes mellitus, severe anemia, asthma, APH, or who are Rhesus negative (risk of severe fetal jaundice/hydrops).
  • 15. History of instrumental deliveries: Previous use of forceps or vacuum extractors indicates previous poor labour progress or CPD.
  • 16. History of mental illness: High risk of puerperal psychosis, severe postpartum depression, and failure to bond with or care for the newborn.
  • 17. History of premature deliveries or 2+ stillbirths: Indicates a hostile uterine environment, cervical incompetence, or untreated chronic maternal infections.

Roles of a Midwife/Nurse in High Risk Pregnancy

Aims of the Midwife

  • To actively educate the community on risk factors.
  • To educate individual mothers on their specific conditions.
  • To safely care for mothers during pregnancy (ANC).
  • To monitor and care for mothers during labour (Intranatal).
  • To care for mothers after delivery (Postnatal).

1. At the Community Level

The midwife acts as a public health advocate to educate the community about the following:

  • Value of the Girl Child: To value all children equally, ensuring the girl child is not neglected.
  • Education and Nutrition: To educate all children and provide proper, balanced nutrition to young girls to ensure healthy pelvic bone development.
  • Eradicate Harmful Practices: Teaching the extreme dangers of harmful cultural practices (like Female Genital Mutilation or early marriage) to girls before, during, and after pregnancy.
  • Transport Logistics: Encouraging village leaders to organize and provide ready transport for pregnant women in emergencies.
  • Utilization of Services: Persuading the community to abandon traditional, unsterile birth locations and utilize available health facilities.
  • Danger Signs: Teaching the community (especially TBAs and VHTs) how to accurately recognize the danger signs of pregnancy and refer mothers to health units immediately.

2. To the Mother (Individual Level)

The midwife provides specialized, individual education to the high-risk mother:

  • Preparation: The extreme importance of planning and physically preparing her body for pregnancy.
  • Family Planning: Using family planning services so as to only conceive when her body is fully healed and she is medically ready.
  • Service Utilization: Emphasizing that she must utilize all antenatal, intranatal, and postnatal services without skipping appointments.
  • Dietary Needs: Teaching her how to eat well, including how to affordably source, prepare, and properly store a balanced diet to fight anemia.
  • Self-Monitoring: Teaching her to recognize personal danger signs (e.g., bleeding, severe headaches, swollen face, loss of fetal movements).
  • Lifestyle: Strict avoidance of substance abuse (alcohol, smoking, unprescribed native herbs).

3. At the Health Centre

During Pregnancy (Antenatal Care)

Health workers must ensure the following clinical protocols are strictly followed:

  • Proper ANC: Conducting thorough physical exams, lab tests (Hb, syphilis, HIV, blood group), and accurately filling out the maternal passport.
  • Health Education: Continual counseling on proper nutrition, adequate rest, sleep, and rigorous personal hygiene.
  • Early Detection: Promptly detecting danger signs (like a sudden spike in BP or trace proteins in urine) and managing them before they escalate.
  • Emergency Care & Referrals: Stabilizing the mother and organizing rapid referrals to higher-level hospitals for specialized care.
  • Prophylactic Medication: Giving Tetanus Toxoid (TT) to prevent neonatal tetanus; Iron and Folic Acid to prevent severe anemia; Fansidar (IPTp) to prevent malaria in pregnancy; and Mebendazole for deworming.
  • Discourage Native Medicine: Strongly warning mothers against herbal oxytocics, which can cause violent, uncoordinated contractions and fatal uterine rupture.
  • Psychological Counseling: Counseling mothers not to place blame on themselves or feel guilt for their high-risk situations (such as unavoidable medical diseases or frequent childbearing).

During Labour (Intranatal Care)

  • Provide absolutely safe, clean, and sterile delivery services.
  • Show continuous kindness, emotional support, and understanding to calm the anxious mother.
  • Provide proper hydration and energy (nutrition) during early labour.
  • Strict Monitoring: Monitor mothers intensely during labour. Always use a Partograph for early detection of obstructed labour, fetal distress, or poor progress.
  • Rapid Referral: Follow proper referral systems to prevent any delay in accessing surgical medical care if the partograph crosses the alert/action lines.
  • Actively anticipate and prevent complications (e.g., active management of the third stage of labour to prevent PPH).

👶 The 9 Essential Needs of a Newborn Baby

Whether high-risk or normal, the midwife must instantly provide the 9 fundamental needs of the newborn upon delivery:

  1. Respiration: Immediate establishment and maintenance of an open airway and breathing.
  2. Warmth: Drying thoroughly and keeping the baby warm to prevent fatal hypothermia.
  3. Breastfeeding: Initiating immediate skin-to-skin contact and early exclusive breastfeeding.
  4. Infection Prevention (Cord Care): Clean cutting and sterile tying of the umbilical cord.
  5. Eye Care: Preventing neonatal blindness by instilling Tetracycline eye ointment.
  6. Immunization: Administering early vaccines (Polio 0 and BCG) at birth.
  7. Security and Love: Ensuring the baby is safely kept with the mother.
  8. Cleanliness: Maintaining high hygiene in handling the infant.
  9. Continuous Monitoring: Checking for bleeding from the cord, jaundice, or respiratory distress.

The Roles of a Husband in Safe Motherhood

Safe motherhood is not just a woman's issue. The active involvement of the husband or male partner drastically reduces maternal mortality. His roles are categorized into five crucial phases:

1. During Pregnancy

  • Empathy: To deeply understand and appreciate the physical discomfort, extreme anxiety, and severe tiredness that pregnancy causes his wife.
  • Physical Relief: Take over physically tiring tasks (e.g., digging in the field, lifting heavy jerrycans of water, washing, and scrubbing floors) to avoid exhausting the pregnant woman.
  • Childcare: Take an active role in taking care of the older children.
  • Emotional Support: Provide constant encouragement. Try not to make heavy demands on her and completely avoid criticizing her changing body or moods.
  • Education: Learn about pregnancy-related conditions alongside his wife so he can help her more effectively and recognize the critical danger signs of pregnancy.
  • Accompanying to ANC: Escort his wife to the health center for Antenatal Care and actively participate in the health education sessions.
  • Financial Provision: Understand that good nutrition and medical care are paramount. He must provide the necessary money to buy healthy food, pay for transport, and purchase needed medication.
  • Emergency Readiness: Pre-arrange and secure ready transport in case of any sudden emergency during the day or the middle of the night.

2. During Labour and Child Birth

  • Ensure all required delivery materials (mama kits, clothes, transport money) are ready.
  • Stay by her side: Stay with his wife at the hospital during labour and delivery to provide physical comfort, massage her back, and offer immense emotional support.

3. After Delivery (Puerperium)

  • Adaptation: Adapt to the new baby in his life and actively help meet the baby’s demands, especially by supporting the mother while she is breastfeeding.
  • Attention and Help: Give the mother understanding and attention. Help her with daily tasks so she can heal from the wounds of childbirth.
  • Nutrition and Health: Contribute to a happy family by ensuring the mother is fed highly nutritious, blood-building foods, and that both she and the baby receive their postnatal medical care.
  • Vigilance: Be highly aware of postnatal danger signs (like heavy bleeding, foul-smelling discharge, or high fever) that necessitate rushing back to the hospital.

4. In Family Planning

  • Birth Spacing: Ensure the mother has fully recovered from the massive physical depletion of pregnancy and birth. He must protect her from becoming pregnant for at least 2 years after the birth of the last baby.
  • Seek Advice Together: Go together with the mother to seek professional advice from the doctor or family planning clinic about the best methods of contraception.
  • Support the Choice: Give full support and cooperation when using whichever method the couple selects.
  • Male Involvement: He should bravely accept male family planning methods (like condoms or vasectomy) or fully cooperate without complaint when the woman is using a female method.

5. During Child Rearing

  • Protect the family and provide essential resources (food, clothing, shelter, school fees).
  • Actively participate in the daily upbringing and disciplining of the children.
  • Involve the wife in all major household decision-making.
  • Counsel and advise the children as teenagers, openly discussing crucial issues like sex education, when to get married, and choosing a career.
  • Gender Equality: Ensure that his daughters are given the exact same opportunities as his sons in terms of education, healthcare, and benefits.
  • Be emotionally and physically available at home for his wife and children, showing warmth and love.

Management of High Risk Factors

When an emergency arises in a high-risk pregnancy, seconds matter. The general principles applied in this management include strict preparedness, rapid action, and systemic stabilization.

1. Readiness and The Emergency Tray

The facility must be perfectly ready with everything used in the management of obstetric emergencies. The Emergency Tray must always be fully stocked, unexpired, and immediately accessible. It must contain:

Emergency Drug / ItemPrimary Obstetrical Use
Ergometrine / Pitocin (Oxytocin)To instantly arrest severe bleeding (Postpartum Hemorrhage).
Diazepam / Magnesium SulphateTo stop and prevent severe convulsions in Eclampsia.
Hydrocortisone / DexamethasoneFor severe shock, severe asthma, or to mature fetal lungs in premature labour.
MannitolAn osmotic diuretic used to reduce dangerous cerebral edema (brain swelling).
Digoxin / Lasix (Furosemide)To manage acute heart failure or severe pulmonary edema (fluid in lungs).
Dextrose 5% and 50%To correct severe maternal or neonatal hypoglycemia and provide rapid IV energy.
Vitamin KTo prevent or treat severe hemorrhagic disease in the newborn.
Aminophylline / AdrenalineFor severe asthmatic attacks, cardiac arrest, or anaphylactic shock.
AtropineTo correct dangerous bradycardia and dry up excessive respiratory secretions.
Pethidine / MorphinePotent narcotics to manage extreme pain and severe maternal shock.
EquipmentOxygen cylinders, IV Normal Saline, large-bore needles, syringes, Ambu bags, and resuscitation masks.

2. Immediate Actions (The Nursing Process)

  • Stay Calm: The midwife/nurse must be calm, quick, and knowledgeable. Shout and summon for extra help immediately.
  • Prioritize (ABC): Start with the most urgent, life-saving need first (e.g., clearing the airway, arresting massive hemorrhage, establishing IV lines for rapid rehydration, or urgent delivery of the baby).
  • Rapid Assessment: Perform quick general history taking, examination, and essential investigations while simultaneously treating.
  • Systematic Care: Apply essential care systematically based on the emergency (e.g., preparing for a vacuum delivery, manual removal of a retained placenta, or CPR for the newborn).
  • Reassurance: Continuously reassure the terrified mother and her panicking relatives. Keep them informed.

⚠️ Attention: The Referral Note

Early detection and referral are paramount. Some high-risk mothers are cared for in the maternity center during pregnancy but referred at full term for hospital delivery. Others are referred on the very first contact. If an emergency transfer is needed, the midwife must prepare a detailed referral note containing:

  • Exact time of arrival and time of referral.
  • Detailed personal and obstetrical history of the mother.
  • Her general condition upon arrival.
  • All findings discovered upon physical and vaginal examination.
  • Exact treatment and drugs given (with dosages and times) plus obstetrical management provided.
  • Clear reasons for the referral and her exact condition at the moment of transport.

Prevention of High Risk Pregnancies

Preventing high-risk pregnancies and their complications requires a tightly coordinated effort between the midwife, the husband, and the community at large.

  • Midwife Competence: The midwife/nurse must be highly knowledgeable on exactly how to identify and deal with HRPs.
  • Continuous Medical Education: She must actively update herself on the latest guidelines and protocols for managing modern obstetrical conditions.
  • Facility Readiness: The midwife must ensure her maternity center is perfectly equipped with drugs, sterile supplies, and an organized transport plan to deal with such cases efficiently and without fatal delays.
  • Community Empowerment: Educating families to delay early marriage, stop adolescent pregnancies, space births through family planning, and ensure women give birth in hospitals under skilled supervision.

Quick Quiz

Risk Pregnancies Quiz

Reproductive Health - mobile-friendly and focused practice.

Privacy: Your details are used only for quiz tracking and certificates.

High Risk Pregnancies Read More »

delays in Safe Motherhood
Home > Reproductive > Safe Motherhood

Safe Motherhood

Introduction to Safe Motherhood: Every single minute of every day, somewhere in the world (most often in a developing country), a woman dies from complications related to pregnancy or childbirth. That equates to a minimum of 515,000 women dying every year.

  • 99% of maternal deaths occur in the developing world, making maternal mortality the health statistic with the largest disparity between developed and developing nations.
  • For every woman who dies, 30 to 50 women suffer severe injury, infection, or disease.
  • Pregnancy-related complications are among the leading causes of death and disability for women aged 15–49 in developing countries.

A woman's death is more than a personal tragedy. Children lose their primary caregiver, communities lose her unpaid and paid labor, and nations suffer an enormous cost to their economic and social development.

Definition & Origin of Safe Motherhood

Safe Motherhood Definition: This means ensuring that all women receive the exact care they need to be safe and healthy throughout pregnancy, childbirth, and the postpartum period. Safe motherhood ensures that no woman, fetus, or child should die or be harmed by pregnancy or birth.

It encompasses a series of initiatives, practices, protocols, and service delivery guidelines designed to ensure that women receive high-quality gynecological, family planning, prenatal, delivery, and postpartum care. It begins with the fundamental assurance of basic safety living as a girl and a woman in society.

  • Origin: The Safe Motherhood Initiative (SMI) officially started in 1987 at an international conference held in Nairobi, Kenya.
  • Initial Goal: The conference marked the beginning of a global initiative to reduce maternal mortality by 50% by the year 2000.

History and Evolution of Safe Motherhood (SMI)

The Safe Motherhood Initiative did not happen overnight; it evolved progressively from early global concerns into a highly targeted, worldwide movement.

  • Early Efforts (1930s): According to AbouZahr (2003), the League of Nations noted and expressed deep concern regarding maternal mortality as early as the 1930s, especially concerning rapid industrialization and vertical medical programs.
  • The UN Decade for Women (1976-1985): Efforts culminated during this decade, bringing women's overall health to the global stage.
  • The Alma Ata Conference (1978): The WHO launched a comprehensive approach to health known as Primary Health Care (PHC), which strongly included maternal health.
  • The Setback of the 1980s: The comprehensive PHC approach was short-lived. It was compromised by the introduction of Selective PHC (SPHC) in the 1980s. SPHC focused heavily on vertical programs (like family planning) while actual safety during pregnancy and childbirth was tragically neglected.
  • The Turning Point (1985): Advances in statistical techniques unearthed grim insights. The WHO, supported by UNFPA, invested in community studies revealing that over 500,000 maternal deaths were occurring annually (99% in developing nations).
  • Official Launch (1987): In February 1987, the WHO, UNFPA, and World Bank jointly sponsored the first international conference on Safe Motherhood in Nairobi, Kenya. Dr. Hafdan Mahler (then director of WHO) declared: "...something can, should—indeed must—be done, starting with the commitment of heads of states and governments."

3 Key Strategies of the 1987 Initiative (McGowan, 2017)

  1. Strengthening community-based health care.
  2. Building the capacity of referral-level facilities.
  3. Developing a rapid alarm and transport system to clearly link community and referral-level care.

Modern Integration: Safe motherhood has since been fully integrated into all global agendas. This includes the Millennium Development Goals (MDGs: 2000-2015) and the Sustainable Development Goals (SDGs: 2015-2030). Under SDG Goal 3 (target 3.1), the target is to reduce the global maternal mortality ratio to less than 70 per 100,000 live births by 2030.

⚠️ Points for Attention: The Dark Period of the 1980s

The shift from comprehensive PHC (1978) to Selective PHC (1980s) was a dark period for maternal survival. Global funding focused heavily on preventing pregnancies (family planning) rather than keeping women safe while they were actually delivering babies. The 1987 Nairobi conference corrected this fatal oversight.

Current Statistics & Scope of the Problem

According to the WHO (2017), the worldwide Maternal Mortality Rate (MMR) stands at 295 per 100,000 live births. Annually, approximately 585,000 to 600,000 women die of pregnancy-related complications (99% in developing countries, 1% in developed countries).

  • Developed Countries: 11 per 100,000
  • Low-Income Countries: 462 per 100,000
  • Sub-Saharan Africa: 196 per 100,000
  • Uganda: 336 (to 343 based on recent specific country stats) per 100,000

Annual Scope of the Global Problem

  • 180-200 million pregnancies per year.
  • 75 million unwanted pregnancies.
  • 50 million induced abortions.
  • 20 million unsafe abortions.
  • 1 maternal death results in 30 maternal disabilities.

Developing vs. Developed Countries

Developing CountriesDeveloped Countries
Weak health systemsAvailability of robust data systems
Substandard quality of careHigh professional expertise
Ineffective health servicesAccess to cost-effective technologies
Inadequate obstetric careEnabling political conditions
Unregulated fertilityHigh awareness
High rates of infectionsStrong commitment to act
Illiteracy & IgnoranceAbility to access affordable health services
Early marriage-
Poverty & Malnutrition-

The State of Uganda

Uganda has the third fastest-growing population in the world. The systemic challenges and statistics are critical to understanding the local safe motherhood context:

  • Total Fertility Rate: 6.9
  • Maternal Mortality Ratio (MMR): 343 per 100,000
  • Infant Mortality Rate (IMR): 97 per 1,000
  • Child Mortality Rate: 147 per 1,000
  • Unmet Need for Contraception: 28.4%
  • Primary Education Completion: Only 34%
  • Early Pregnancy: 70% of first pregnancies occur by age 19.

Systemic Challenges in Uganda

  • While the Constitution guarantees women's rights, practical implementation takes time.
  • Low levels of education for women and girls.
  • Political and economic policies (e.g., World Bank and IMF policies) often do not favor African realities.
  • Per capita spending on health is only $5, far less than the $40 recommended by the World Bank.
  • Political will is often unfavorable to women's health (e.g., Sexual and Reproductive Health and Rights - SRHR services in school curriculums are still deemed unacceptable).
  • The generally low status of women combined with extreme poverty.

Global Initiatives: ICPD and The Mother Baby Package

Following the 1987 Nairobi conference, global efforts continued to expand, spearheaded by the WHO, the United Nations Population Fund (UNFPA), the World Bank, and the United Nations Development Program (UNDP).

  • The 1994 ICPD Conference (Cairo): During the Program of Action at the International Conference on Population and Development (ICPD) in 1994, a major global consensus was reached. It was agreed that meeting the reproductive health needs of women and men is a critical requirement for human and social development.
  • Integration into Primary Health Care: The conference firmly affirmed that reproductive healthcare is not a separate, isolated issue; rather, it is an integral component of Primary Health Care (PHC) and must be provided within that context. The elements and components of reproductive health have a profound, direct impact on the course and outcome of pregnancy. Therefore, the health service requirements for addressing them are closely related.
  • The WHO Mother Baby Package: It was during this 1994 conference that consensus was built to adopt a comprehensive strategy that addresses all aspects of reproductive health. This provided an opportunity to develop an integrated approach to safe delivery, which led directly to the creation of the WHO Mother Baby Package.

The "Making Pregnancy Safer" Strategy

After about 5 years of implementing the Mother Baby Package, the WHO and its global partners recognized the need to further improve maternal health and drastically reduce maternal mortality. This led to the introduction of the "Making Pregnancy Safer" strategy.

This strategy heavily emphasizes the importance of specific health sector interventions. If these six interventions are well implemented, they have the proven capacity to significantly reduce maternal mortality in any country:

  • 1. Advocacy: Continuously raising awareness and speaking up for women's health at the community, national, and international political levels.
  • 2. Partnerships: Building strong alliances between governments, health workers, donors, and non-governmental organizations to pool resources.
  • 3. Improving National Capacity: Training more midwives, equipping hospitals, and strengthening the overall national healthcare system to handle obstetric emergencies.
  • 4. Standard Setting and Tool Development: Creating clear, evidence-based clinical guidelines, protocols, and manuals for midwives and doctors to follow uniformly.
  • 5. Research and Development: Continuously studying maternal health trends to find new, cost-effective technologies and medical solutions to save lives.
  • 6. Monitoring and Evaluation: Keeping strict records and analyzing maternal data to see if the implemented programs are actually working and saving lives.

⚠️ Attention: Maternal Death as a Human Rights Issue

What is known worldwide about adverse maternal health is that a country’s overall economic wealth is not the only important determinant. According to national and international human rights treaties, safe motherhood is considered a fundamental human rights issue. Therefore, maternal death is a tragic reflection of a "social disadvantage," not merely a "health disadvantage."

Aims of Safe Motherhood

Note: Maternal and child health promotion is one of the key foundational commitments embedded in the WHO constitution.

The Safe Motherhood initiative is a global effort. It aims to improve women's health through deep social, community, and economic interventions. To achieve this, it relies on its partners: Government agencies, NGOs, and other local groups and individuals. The primary aims include:

  • Hygienic and Accepted Medical Practices: To ensure that all deliveries are conducted safely, hygienically, and strictly according to accepted medical practices. This prevents iatrogenic complications (complications caused or exacerbated by poor care and dirty environments).
  • Prompt Identification & Management: To identify obstetric complications promptly and manage them appropriately, either by treating the mother immediately at the facility or referring her to a higher level of care without delay.
  • High Quality & Culturally Appropriate Care: Provision of high-quality care that respects the mother's culture. This ensures necessary follow-up and strong linkages with other critical services, including antenatal care, post-partum care, family planning, post-abortion care, and the treatment of STIs.
  • Enhance Quality of Life: To deeply enhance the overall quality and safety of girls' and women's lives through the adaptation of a combination of health-related and non-health-related strategies (like education and economic empowerment).

The Pillars of Safe Motherhood

The Safe Motherhood initiative is built upon a "house" of foundational structural pillars and key components:

  • 1. Antenatal Care: Effective care is essential to detect preexisting conditions, prevent complications where possible, and ensure that serious conditions are treated appropriately and quickly.
  • 2. Essential / Emergency Obstetric Care: Pregnancy is a period of potential risk for any woman (roughly 15% of normal pregnancies develop sudden complications). High-quality emergency care must be available to all women.
    • Basic Emergency Obstetric Care (BEmOC): Includes basic first aid, IV antibiotics, oxytocic drugs, sedatives/anticonvulsants for eclampsia, manual removal of the placenta, and manual removal of retained products.
    • Comprehensive Emergency Obstetric Care (CEmOC): Includes ALL BEmOC services, PLUS Surgery (Caesarean sections), Anaesthesia, and Blood transfusion capabilities.
  • 3. Family Planning: Individuals and couples must have the information and services to plan the timing, number, and spacing of pregnancies to prevent unwanted pregnancies and unsafe abortions.
  • 4. Postnatal Care: The critical first six weeks after childbirth. Most maternal and infant deaths occur during this time, yet it remains the most neglected period for the provision of quality care.
  • 5. Abortion Care: Comprehensive abortion care includes safe abortion, post-abortion care, and family planning. (Note: Uganda currently only permits post-abortion care legally).
  • 6. Equity for Women: Fairness of treatment according to respective needs. This includes equal treatment or equivalent treatment regarding rights, benefits, obligations, and opportunities.
  • 7. STD/HIV Control: Prevent, detect, and treat STDs and HIV during pregnancy to prevent mother-to-child transmission (PMTCT) and protect maternal immunity.
  • 8. Primary Health Care (PHC): Essential healthcare based on scientifically sound and socially acceptable methods, making universal healthcare accessible to all.
  • 9. Communication for Behavior Change (SBCC/C4D): An interactive process to develop communication strategies promoting positive health behaviors appropriate to community settings.

❓ Applied Question: BEmOC vs CEmOC

Scenario: A rural health center is fully stocked with IV antibiotics, oxytocin for bleeding, magnesium sulfate for eclampsia, and the staff can manually remove a stuck placenta. However, they do not have an operating theater or a blood bank. Is this facility classified as BEmOC or CEmOC?

Answer: It is a BEmOC (Basic Emergency Obstetric Care) facility. To be classified as CEmOC (Comprehensive), a facility MUST have the capacity to perform surgery (like Caesarean sections) and administer blood transfusions.

Components and Requirements for Safe Motherhood

The 6 Core Components of Safe Motherhood

  • Pre-conception care: Health and education before a woman even gets pregnant.
  • Antenatal care: Close monitoring and education during the 9 months of pregnancy.
  • Emergency obstetric care (EmOC): The ability to perform life-saving interventions (like C-sections or blood transfusions) when unexpected complications arise.
  • Care of the newborn: Immediate resuscitation, warmth, and infection prevention for the baby.
  • Postpartum care: Critical monitoring of the mother for bleeding and sepsis during the 6 weeks after delivery.
  • Post-abortion care: Treating complications of miscarriage or unsafe abortions and providing family planning.

The 3-Way Strong Strategy (Requirements)

Achieving safe motherhood and permanently reducing maternal mortality strictly requires this 3-way strong strategy:

  1. Access to Contraception: All women must have easy access to modern contraception to avoid unintended, high-risk pregnancies.
  2. Skilled Attendance at Birth: All pregnant women must have access to a trained, skilled health worker (midwife or doctor) at the exact time of birth.
  3. Access to Emergency Care: All women who develop sudden complications must have timely access to quality emergency obstetric care.

The Roles of the Community in Safe Motherhood

Safe motherhood cannot be achieved by midwives alone within the hospital walls. The community must actively give support in several practical ways to make motherhood safer:

  • Share the Workload: Family and community members must share household chores (like fetching water or farming) so that the pregnant mother can avoid heavy physical work that could trigger premature labour.
  • Encourage Diet and Rest: Actively encourage the pregnant mother to eat a highly nutritious, balanced diet and to rest much more than usual, especially during the exhausting last three months of pregnancy.
  • Ensure Medication Adherence: Encourage and remind mothers to take their iron/folic acid (non-pills) or other prescribed routine medications exactly as provided by the midwife.
  • Assist with Childcare: Relatives or neighbors should help with looking after the older children so that the mother has the freedom and time to go for her antenatal care visits and to safely deliver in the hospital.
  • Transport Readiness: The community leaders and families must establish transport readiness (e.g., saving money, identifying a vehicle or ambulance) well in advance for rapid emergency referral in case of obstetrical complications.
  • Use of Maternity Waiting Areas: Strongly encourage high-risk mothers to travel early and use maternity waiting areas near the hospital, especially if they were advised to do so by the midwife during antenatal care.
  • Safe Motherhood Groups: Create, inform, and heavily motivate community-based safe motherhood groups (like Village Health Teams) to continuously educate the village on maternal danger signs.

The Road Map to Safe Motherhood & Foundational Core

Safe motherhood is founded on freedom from discrimination, active participation, valuing the girl child, and ensuring access to care. The "Road Map" ensures maternal health is maintained throughout the life cycle:

  • Childhood: Female children must have good nutrition for adequate growth and pelvic bone development (preventing future obstructed labour). They must be fully immunized against killer diseases.
  • Adolescence: Girls should be educated about safe sexuality before experimentation to prevent early, unplanned pregnancies and STIs.
  • Community & Family Support: A woman needs to be valued emotionally and physically. She should be relieved from heavy physical work during pregnancy. Communities must help organize referral transport systems.
  • Antenatal to Puerperium: Mothers must be encouraged to attend ANC early. Traditional Birth Attendants (TBAs) must be educated to identify at-risk cases and refer them to hospitals instantly.

Global Initiatives & Conferences

  • 1994 ICPD (Cairo): The International Conference on Population and Development established that reproductive health is an integral component of primary health care and a critical requirement for human development. This birthed the WHO Mother Baby Package.
  • Making Pregnancy Safer Strategy: Five years after the Mother Baby Package, WHO introduced this strategy, emphasizing: Advocacy, Partnerships, Improving national capacity, Standard setting, R&D, and Monitoring/Evaluation.
  • Social Disadvantage: Safe motherhood is a human rights issue. A maternal death is a reflection of a "social disadvantage, not merely a health disadvantage."

10 Priorities for Safe Motherhood (Action Messages)

During the 10th anniversary of the SMI, ten critical action messages were articulated summarizing the priorities needed to overcome economic, legal, social, and cultural barriers:

  1. Advance Safe Motherhood Through Human Rights: Preventing maternal death is social justice. Women have rights to life, health, privacy, liberty, and equality (free from discrimination and coercion).
  2. Empower Women, Ensure Choices: Maternal deaths are rooted in women's powerlessness and unequal access to employment, finances, and education. Legal reform and community mobilization are essential.
  3. A Vital Economic and Social Investment: National development plans must include safe motherhood. In developing countries, basic maternal and newborn care can cost as little as US$3 per person, per year.
  4. Delay Marriage and First Birth: Adolescent childbearing carries immense risks. Community education must encourage delaying marriage until women are physically, emotionally, and economically prepared.
  5. Every Pregnancy Faces Risks: Any woman can develop life-threatening complications. ANC programs should not waste resources solely on "risk-scoring," but must ensure emergency care is ready for all women.
  6. Ensure Skilled Attendance at Delivery: The single most critical intervention is ensuring a skilled health worker with midwifery skills is present at every birth, backed by emergency transport.
  7. Improve Access to Quality Reproductive Health Services: Health systems must address clinical, interpersonal, and logistical problems to overcome cultural customs that prevent women from seeking care.
  8. Prevent Unwanted Pregnancy & Address Unsafe Abortion: With 75 million unwanted pregnancies annually, unsafe abortion is the most neglected and easily preventable cause of maternal death. Client-centered family planning is vital.
  9. Measure Progress: Because maternal mortality is difficult to measure perfectly, alternative indicators must be used (e.g., recording the proportion of births attended by skilled personnel).
  10. The Power of Partnership: Reducing maternal mortality requires long-term commitment between governments, NGOs, donors, and community leaders.

⚠️ Points for Attention: Priority #5 (Risk Scoring)

Priority #5 marks a massive shift in public health. Historically, clinics tried to "score" women into low-risk and high-risk categories. We now know that every pregnancy faces risks, and emergencies (like postpartum hemorrhage) can happen to completely healthy women. Readiness for emergency care at delivery is far more important than risk-scoring.

Causes of Maternal Deaths

Direct Causes (Contribute to 75% of all maternal deaths):

  • Severe bleeding (Hemorrhage): 31%
  • High blood pressure during pregnancy (Eclampsia): 20%
  • Infections (Sepsis): 1% to 15% globally depending on the region
  • Complications from delivery (Obstructed labor): 7%
  • Unsafe abortion

Indirect Causes (Contribute to ~25%):

  • The Three Delays: (1) Delay in seeking care, (2) Delay in reaching care, (3) Delay in receiving care.
  • Accessibility issues and extreme poverty.
  • Harmful cultural practices.

Human Rights and Safe Motherhood

Preventing maternal death is fundamentally an issue of social justice and human rights.

  • The Right to Life: Article 6 of the Political Covenant states every human has an inherent right to life. Maternity is a social function, not a disease. Emergency obstetric care must be accessible to preserve life.
  • Rights Relating to Pregnancy and Childbirth: Women are entitled to special protection, paid maternity leave, and must not suffer employment discrimination.
  • Rights Relating to Discrimination: Neglecting maternity care constitutes sex discrimination. For example, requiring a husband's spousal consent for maternal care (which men do not need for their own care) is highly discriminatory.
  • Fertility by Choice: Article 16 of the Women's Convention grants women the right to decide freely on the number and spacing of children. Denying family planning coerces women into motherhood.
  • Rights to Health (Sexual & Reproductive): Entitles women (including HIV-positive women needing PMTCT) to the highest attainable standard of health via functioning, accessible facilities.
  • Rights to Privacy, Liberty, and Security: Women must be empowered to decide for themselves when to seek health care without the cruel/degrading requirement of spousal permission.
  • Rights to Education and Information: Crucial for raising awareness of safe motherhood and identifying danger signs.

⚠️ Points for Attention: Human Rights Violation

If a woman dies because society deemed her unworthy of a $5 transport fare to a clinic, or because her husband refused to give "permission" for her to leave the house, her death is a severe human rights violation, not just a medical failure.

Enablers and Preventing Factors of Safe Motherhood

Enablers of Safe MotherhoodPreventing Factors (Barriers)
Antenatal care provided directly in the village.No trained midwives available to the community.
A good, fast system of emergency referral.Untrained TBAs handling complicated deliveries.
Safe motherhood committees driving community ownership.No working relationships with community leaders.
Maternity waiting homes for women living far away.No transport available for emergencies.
Male involvement and deployment of Village Health Teams (VHTs).Severe poverty and poor road infrastructure (especially in rain).
Mobile health (mHealth) reminders and elimination of user fees.Drug/blood stock-outs and ingrained cultural myths against medicine.

📋 Assignment & Framework: The 3-Delay Model

Prompt: Discuss the 3-delay model as it relates to access to maternal and newborn care by women and girls.

Concept Breakdown (The 3 Delays):

  • Delay 1 (Deciding to seek care): Driven by a lack of knowledge of danger signs, cultural beliefs, reliance on traditional healers, or women lacking the financial/decision-making autonomy to leave the house without permission.
  • Delay 2 (Reaching the facility): Driven by vast geographical distances, poor road conditions, lack of ambulances/transportation, or total inability to pay for transport.
  • Delay 3 (Receiving quality care): Driven by understaffed clinics, poorly trained workers, lack of essential equipment/drugs, lack of a blood bank, or poor staff attitude resulting in lethal neglect.

Test yourself: If a woman arrives at a clinic in active labor but bleeds to death because the clinic has no IV oxytocin or blood transfusions available, which Delay caused her death? Answer: Delay 3.

Quick Quiz

Safe motherhood Quiz

Reproductive Health - mobile-friendly and focused practice.

Privacy: Your details are used only for quiz tracking and certificates.

 Safe Motherhood Read More »

Integration of Reproductive Health Services
Home > Reproductive Health > Integration of Reproductive Health Services

Integration of Reproductive Health Services

Integration of Reproductive Health Services (RHS) is a comprehensive healthcare approach where multiple health services are made available to clients simultaneously during a single visit. The ultimate goal is to provide a holistic, convenient, and cost-effective "One-Stop Shop" for clients, maximizing the use of available resources while dramatically reducing missed opportunities for healthcare interventions.

In this detailed module, we will explore the definitions, driving factors, immense benefits, core principles, and the various modes of delivering integrated reproductive health services in the community.

1. Definition and Concept of Integration

Integration in healthcare is not just a policy; it is a client-centered philosophy. It can be defined in several comprehensive ways:

  • Holistic Approach: It is an approach in which healthcare providers proactively use opportunities to engage clients in addressing broader health and social needs, rather than solely focusing on the primary reason for the health encounter.
  • Proximity and Accessibility: It is a phenomenon or process where several services are made available to clients or groups of people so that those needing specific Reproductive Health Services (RHS) can access them within their immediate vicinity (e.g., offering Family Planning alongside Safe Motherhood and Cervical Cancer Screening).
  • Consolidation of Services: It is the process of providing a wide variety of RHS by either one or more competent service providers within one single facility on a daily basis.
  • Resource Maximization: In order to maximize the use of scarce resources, Sexual and Reproductive Health Services (SRHS) should be provided as an integrated health care package that is highly convenient for both clients and service providers. Clients must be able to receive/access various SRHS during one single visit at a given static facility or outreach health unit.

Integration provides an anticipatory assessment. It helps providers plan and evaluate services strictly relevant to the client’s actual desires, current needs, and potential future risks.

⚠️ Attention: The "One-Stop Shop" Concept & Referrals

When an integration approach is applied, the primary goal is to meet more than one unique need during a single encounter. Services are offered at the same facility, during the same operating hours. If the needed services are beyond the capacity of the facility or the skills of the attending provider, an effective and timely referral system must immediately be effected. Coordinated care is useless without a strong referral backup.

2. Primary Reasons for Integration of RHS

Why do Ministries of Health and global health bodies heavily advocate for service integration? The reasons include:

  • Simultaneous Availability: To make various critical services available at the exact same time, preventing the client from having to make multiple expensive trips.
  • Geographical Reach: To help reach deeply remote communities who may not be able to frequently access distant RHS facilities.
  • Specialized Assistance: To ensure people with specific, complex reproductive-related problems are immediately assisted, and those with complicated cases are swiftly referred for specialized attention.
  • Community Awareness: To drastically create awareness, improve health-seeking behaviors, and increase the frequency and quality of community contact with healthcare providers.

3. Factors That Promote Successful Integration

For integrated services to run smoothly and sustainably, several foundational factors must be strengthened:

  • Capacity Building (Training): This involves continuously improving the skills and ability of the already existing staff (e.g., training a midwife to screen for cervical cancer) and recruiting more skilled staff to counterbalance the increased workload.
  • Improving Infrastructures: The government and developmental partners must improve transport and communication networks, as well as upgrade health centers and referral systems, to improve client turn-up and accessibility.
  • Sustaining Commodities: Increasing the range of available commodities and ensuring their sustained availability. This is achieved through a constant, timely, and unbroken supply chain of RHS items to meet the overwhelming number of clients.
  • Supervision, Monitoring & Evaluation: Constant and timely integrated supervision is required to rigorously ascertain the success of RHS programs and identify gaps immediately.
  • Facilitating Effective Referrals: Establishing strong networks across services. This helps address clients who need specialized care, ensuring they are treated within the shortest time possible without being lost in the system.
  • Community Sensitization: Aggressive sensitization about the existence of integrated services to improve healthcare-seeking behaviors and make the public fully aware of the comprehensive services available to them.

4. Comprehensive Benefits of Integration

The integration of services creates a powerful ripple effect of benefits categorized into three main groups: for the clients, for the providers, and for the healthcare service itself.

Benefits for the Clients

  • Convenient and Time-Saving: Clients spend less time and money traveling because multiple needs are addressed in one trip.
  • Enhanced Confidentiality: Privacy is deeply respected because sensitive information is shared with only one primary provider rather than a whole sequence of different clinic staff.
  • Perceived Completeness of Care: The service is perceived to be whole and complete because all of the client's reproductive health needs (e.g., immunization for the baby, family planning for the mother) are addressed simultaneously.
  • Improved Relationships: Fosters deep trust and improves client-provider relations.
  • Increased Client Satisfaction: Clients leave feeling comprehensively cared for and valued.

Benefits for the Providers

  • Better Distribution of Duties: Allows for more effective sharing of tasks among the multidisciplinary team.
  • Accessible Resources: Clinical resources, guidelines, and equipment become centrally accessible to every provider in the integrated unit.
  • Increased Confidence: As providers learn to handle multiple services, their clinical confidence and competence grow. Clients also develop increased confidence in the providers' abilities.
  • Balanced Workload: The overall workload is spread out more evenly over all service hours, reducing isolated bottlenecks (e.g., long queues for just one specific service).

Benefits for the Health Service / Facility

  • Accessibility and Availability: Dramatically increases the overall accessibility of essential services.
  • Improves Quality of Care: Comprehensive care naturally elevates the overall quality standard of the facility.
  • "One-Stop Shop": Creates an available, accessible, and user-friendly environment.
  • Efficiency: Service delivery becomes highly efficient, effective, and quick.
  • Reduces Missed Opportunities: A mother coming for her child's measles vaccine can be offered a Pap smear or Family Planning—opportunities that would otherwise be completely missed.
  • Maximizes Resource Utilization: Ensures maximum utilization of available resources (e.g., staff time, diagnostic equipment, clinic space).

5. Core Principles and Steps for Integration of RHS

Integrating services requires careful planning and systematic execution. Health managers and midwives should follow these foundational principles:

Step 1: Build on Existing Opportunities

  • Thoroughly assess the existing health services currently offered at the clinic, particularly focusing on Reproductive Health services.
  • Analyze the type and age demographics of clients being served, as well as the average daily client load.
  • Identify the specific strengths, bottlenecks, and limitations of the current services and the modes in which they are offered.

Step 2: Involve Other Stakeholders

  • Hold inclusive meetings with clinical supervisors, colleagues, and Health Unit Management Committees (HUMC).
  • Review personnel tasks comprehensively and make a detailed list of competencies for each cadre of staff.
  • Draw a strategic work plan and boldly re-allocate services according to the providers' training, skills, and professional interests.

Step 3: Reorganize Services and Infrastructure

Physical space and workflow must be optimized for integration to work smoothly:

  • Create Smooth Client Flow: Serve clients strictly on a first-come, first-served basis. Prioritize the very ill clients who need immediate emergency care. Ensure clients do not have to queue twice (e.g., queuing for records, then queuing again for FP, then again for immunization). Eliminate unnecessary delays.
  • Optimize Waiting Areas: Provide reading materials on Reproductive Health issues. Provide a television or radio to help educate clients while they wait and to reduce boredom. Conduct scheduled health talks by providers and trained peer educators.
  • Upgrade Consultation Rooms: Ensure 100% privacy and visual/auditory confidentiality. Keep rooms well-equipped with all necessary supplies to minimize sending the client to other rooms (minimizing internal referrals).
  • Include Recreation/Youth Space: Where possible, provide a recreation room to allow for group discussions, peer education, and indoor games. This is specifically vital for creating Adolescent-Friendly Services.

Step 4: Orient the Community to Create Demand

  • Conduct aggressive client recruitment activities in the catchment area.
  • Identify and proactively offer RHS to young persons who visit the facility for other unrelated services (e.g., malaria treatment).
  • Put up highly visible notices and posters in public places about the new integrated services offered at the health center.
  • Work closely with local community leaders (LCs), religious leaders, and cultural heads to reach the masses.
  • Liaise with Community Health Workers / Village Health Teams (VHTs) to spread the news door-to-door and formally refer clients for services.
  • Link up with peer educators to demystify reproductive health taboos.

🧠 Key Pillar of Integration

Counseling and IEC (Information, Education, and Communication) form the absolute backbone of all reproductive health services. Without proper communication, clients will not accept or understand the integrated services offered to them.

6. Modes of Reproductive Health Service Delivery

Integrated services can be delivered through various innovative channels to ensure maximum population coverage:

1. Community Outreaches

Taking the services directly to the community via mobile clinics:

  • Health promotion and education.
  • Routine Immunization (UNEPI).
  • Antenatal Care (ANC).
  • Family Planning (FP) provision.
  • STI and HIV/AIDS screening, counseling, and management.
  • Malaria prevention (ITN distribution) and treatment.
  • Treatment of minor ailments and routine deworming.

2. Static Clinics (Health Facilities)

Providing all the outreach services mentioned above, plus specialized services that require fixed equipment:

  • Adolescent Health (Youth-friendly corners).
  • Male-Friendly Reproductive Health Services.
  • Infertility counseling and management.
  • Screening for Reproductive Health Cancers (e.g., VIA for Cancer of the Cervix, Clinical Breast Exams, Prostate, and Testicular cancer screening).

3. Community-Based Services (via VHTs / CHWs)

Empowering locals to provide basic services within their villages:

  • Community distribution of oral contraceptives and condoms.
  • Distribution of Iron and Folic Acid supplements for pregnant mothers.
  • Distribution of anti-malarials.
  • Emergency delivery services and immediate referral protocols.
  • Home-based care and follow-up (e.g., for HIV-positive clients, TB DOTS, and postpartum mothers).

4. Social Marketing

Using commercial marketing strategies to achieve public health goals:

  • Widespread health promotion and education campaigns (Radio, TV, Billboards).
  • Subsidized provision of family planning commodities (e.g., socially marketed condoms like Protector or Life Guard).
  • Provision of subsidized medical supplies such as Mama Kits, Insecticide-Treated Nets (ITNs), and anti-malarials through local shops and pharmacies.

7. Disadvantages and Challenges of Integration

While integration is highly beneficial, it comes with practical implementation challenges that health systems must aggressively mitigate:

  • Increased Workload: It heavily increases the workload on individual healthcare workers, especially in rural settings where the number of staff is already severely limited.
  • Provider Fatigue (Tiresomeness): Service providers experience severe burnout and fatigue because they have to spend a significantly greater amount of time serving each client comprehensively.
  • High Financial Cost: Reorganizing clinics, training staff in multiple disciplines, and ensuring a constant supply chain is highly costly. It becomes a massive challenge where financial support or government funding is very poor.
  • Logistical & Geographical Barriers: It is extremely difficult to perform integrated outreach programs in areas with harsh geographical barriers, impassable roads, flooding, or lack of reliable transport for the medical teams.
  • Increased Client Waiting Times (Initially): Because each consultation takes longer (as the provider addresses multiple needs), clients further back in the queue may experience longer waiting times unless the facility is optimally staffed.

📚 References & Further Reading

  • Ministry of Health Uganda (MoH). National Sexual and Reproductive Health and Rights (SRHR) Policy Guidelines. Kampala, Uganda.
  • World Health Organization (WHO). Integration of sexual and reproductive health and rights in health systems.
  • Myles, M., & Fraser, D. M. Myles Textbook for Midwives. Churchill Livingstone Elsevier. (Sections on Community Midwifery and Public Health).
  • UNFPA Guidelines on Integrated Reproductive Health Services and Family Planning programming.

Integration of Reproductive Health Services Read More »

Want notes in PDF? Join our classes!!

Send us a message on WhatsApp
0726113908

Scroll to Top