Dysmenorrhea is a medical term used to describe painful menstrual cramps that occur just before or during menstruation (the monthly shedding of the uterine lining).
OR
Dysmenorrhea refers to painful menstrual periods.
Nearly 50% of all women have some degree of pain associated with their periods. About 10% are unable to perform their normal activities because of this pain.
Dysmenorrhoea can occur at any age, though uncommon in the first 6 months after the onset of menses and relatively uncommon in the years prior to menopause. The most common ages for this problem to occur are in the late teens and early twenties.
Types of dysmenorrhoea
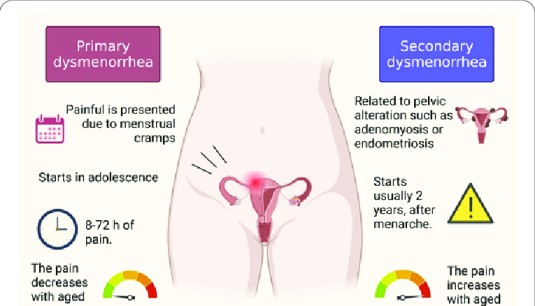
Primary dysmenorrhoea.
Primary dysmenorrhea refers to painful menstruation that starts a few years after puberty and usually no exact cause can be identified.
Cause
The exact cause of primary dysmenorrhea is not fully understood, but it is believed to be related to the release of certain chemicals called prostaglandins in the uterus at the time of menstrual period. The prostaglandin causes contractions of the muscle wall of the uterus, which are called menstrual cramps.
Secondary dysmenorrhoea
Secondary dysmenorrhoea is the type of menstrual pain with a known organic cause.
Secondary dysmenorrhea means pelvic pain caused by a disorder or disease.
Common Causes of Secondary Dysmenorrhoea
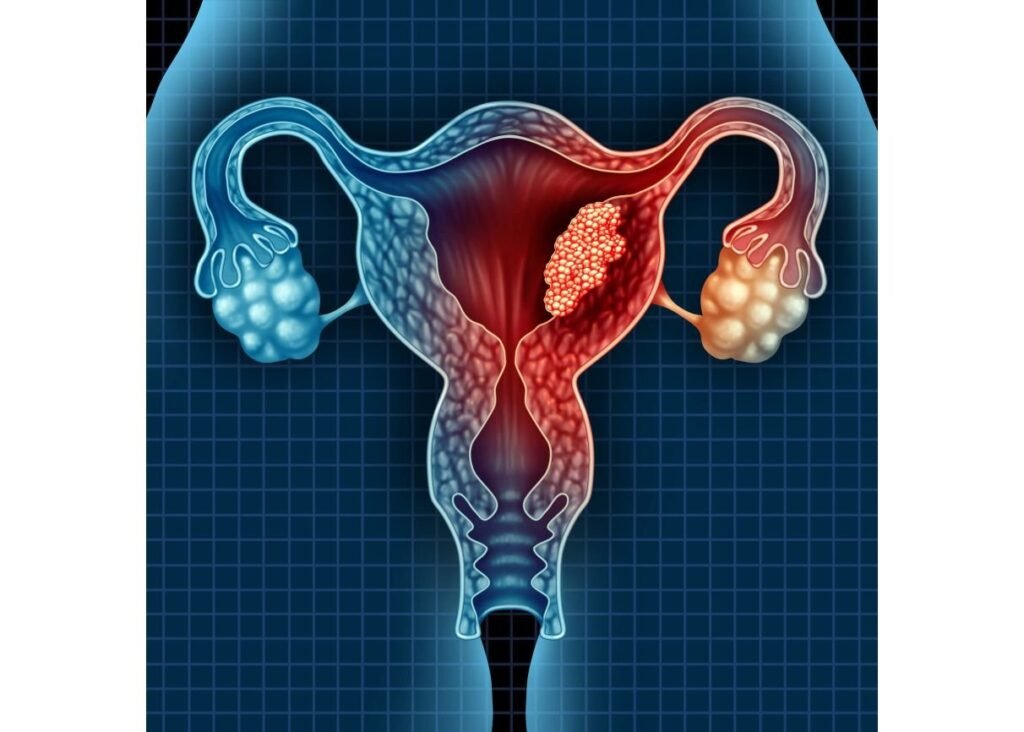
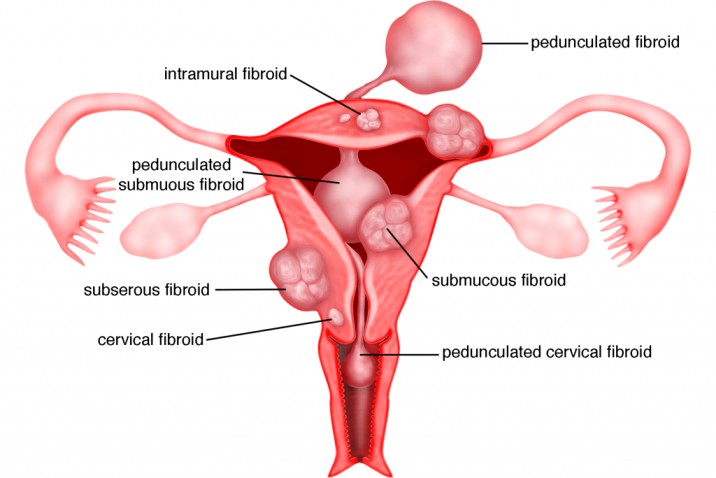
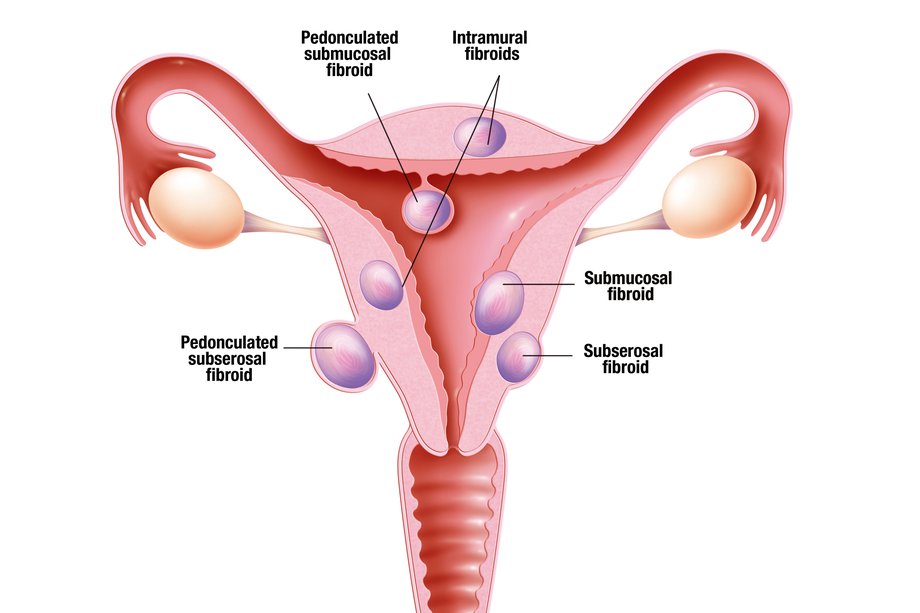
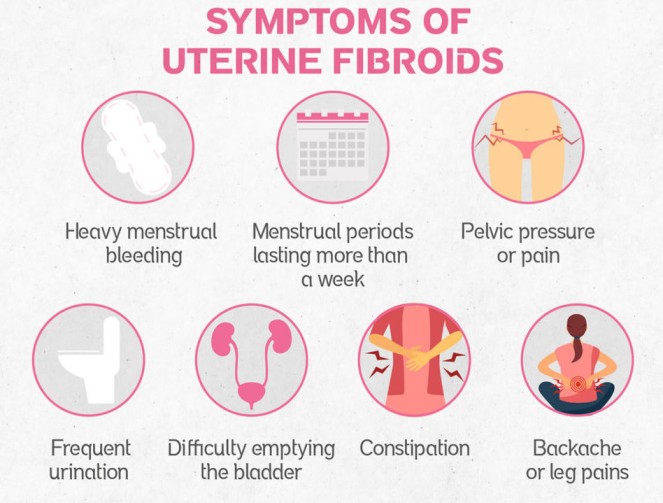
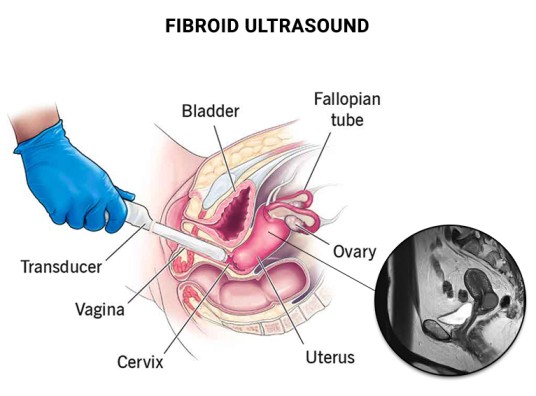
Uterine Fibroids: Noncancerous growths in the uterus.
Endometriosis: The presence of endometrial tissue outside the uterus.
Adenomyosis: The occurrence of endometrial tissue within the muscular walls of the uterus.
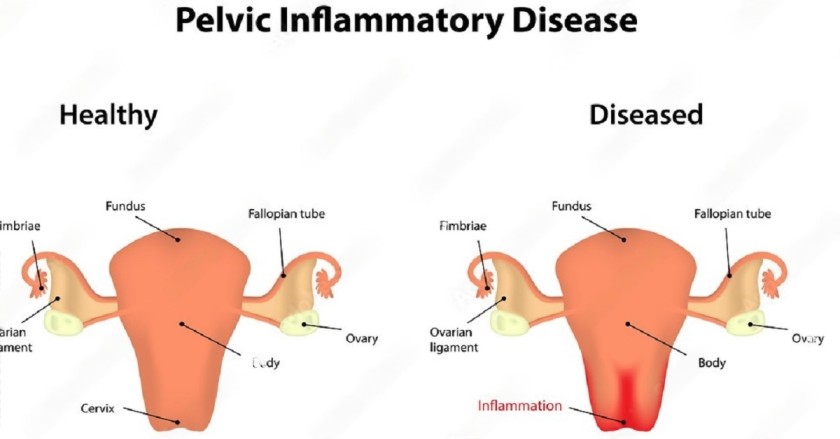
Chronic Pelvic Inflammatory Disease (PID): Long-term inflammation of the female reproductive organs.
Endometrial Polyps: Abnormal tissue growth on the inner lining of the uterus.
Leiomyomata: Benign tumors of the uterine muscle.
Intrauterine Device (IUD) Use: Complications related to the use of contraceptive devices placed in the uterus.
Signs and Symptoms of Dysmenorrhoea
Women with dysmenorrhea tend to begin experiencing symptoms approximately 12 hours before the onset of menses. Common presenting symptoms of dysmenorrhoea include:
Cramping pain in the lower abdomen: Lower abdominal pain (LAP) is a hallmark symptom, usually occurring 3-4 days or even a week before menstruation. The intensity of the pain, ranging from mild to colicky or crampy, extending to the back, thighs and legs, may either improve or exacerbate with the onset of menstruation.
Bilateral Lower Quadrant Pain: The pain associated with secondary dysmenorrhea often extends to both lower abdominal quadrants.
Backache: Patients may experience lower back pain.
Menorrhagia: Characterized by excessive menstrual bleeding.
Painful Coitus (Dyspareunia): Discomfort or pain during sexual intercourse.
Infertility: Difficulty conceiving or achieving pregnancy.
Nausea: Some individuals may experience feelings of nausea.
Headache: Headaches are a common symptom associated with dysmenorrhea.
Vomiting: In severe cases, dysmenorrhea can lead to vomiting.
Fatigue: Fatigue is a general feeling of tiredness or lack of energy that may accompany dysmenorrhea.
Dizziness: Some individuals may experience dizziness or lightheadedness.
Constipation or Diarrhoea: Dysmenorrhea can be associated with bowel changes, including diarrhoea or constipation.
Fainting: In severe cases, dysmenorrhea may lead to fainting.
Fever: Although less common, some individuals may experience a mild fever during dysmenorrhea.
Predisposing factors
Narrow Cervical Os (Stenosis): During menstruation, the uterus contracts to shed its lining. If the cervical os is narrow, it can result in increased tension during these contractions, leading to pain.
Reduced Blood Supply to the Endometrium (Ischaemia): Inadequate blood supply to the endometrium can contribute to the development of primary dysmenorrhea.
Hormonal Imbalance: Fluctuations in hormone levels, particularly prostaglandins, can lead to increased uterine contractions and inflammation, resulting in pain.
Retroverted Uterus: A retroverted uterus, where the uterus is tilted backward, can cause increased tension and discomfort during menstruation.
Psychological or Social Stress: Emotional stress, fear, or anxiety can exacerbate the perception of pain during menstruation.
Advertisements
Diagnosis
History taking: It is through history taking, asking about the nature of pain, duration and when it occurs. This is often confirmatory.
Physical examination: It is also through physical examination to rule out pelvic tumours, endometriosis which is often absent.
Management of Dysmenorrhoea
Aims of Management
Alleviating pain and discomfort associated with menstruation.
Identifying and addressing any underlying causes or contributing factors.
Minimizing the impact of dysmenorrhoea on daily activities and quality of life.
History taking
Take a detailed gynaecological history, including age, parity, first day of the last menstrual period, age of menses onset, length and regularity of cycles, and duration of flow.
Take a pain history to include severity, duration, character, location, radiation, and the relationship of pain to menarche, menses, coitus, bowel movements, voiding, and any other associated symptoms.
Document previous known or suspected pelvic problems.
Review past obstetric history, including first-trimester losses.
Review the past history for other organ system problems that can present with pelvic pain.
Review pelvic infection history, with special attention to recent or past STIs, including the history of STIs among current or former partners.
Review contraceptive history with special attention to past or present IUD use and oral contraception. Document any changes in symptoms with particular contraceptive use.
Review surgical history, including surgical procedures involving the cervix, Caesarean delivery, gynaecological procedures, and other abdominal procedures.
General observation
TPR/BP and careful examination of the reproductive system, including a complete gynecologic examination with cervical testing (abdominal, vaginal, and rectal examination), laparoscopy, and blood tests for progesterone and oestrogen.
Primary dysmenorrhea treatment
Begin treatment 2 days before menstruation begins and continue until 2 days after the period has stopped.
Avoid additive drugs since this treatment is for a long period.
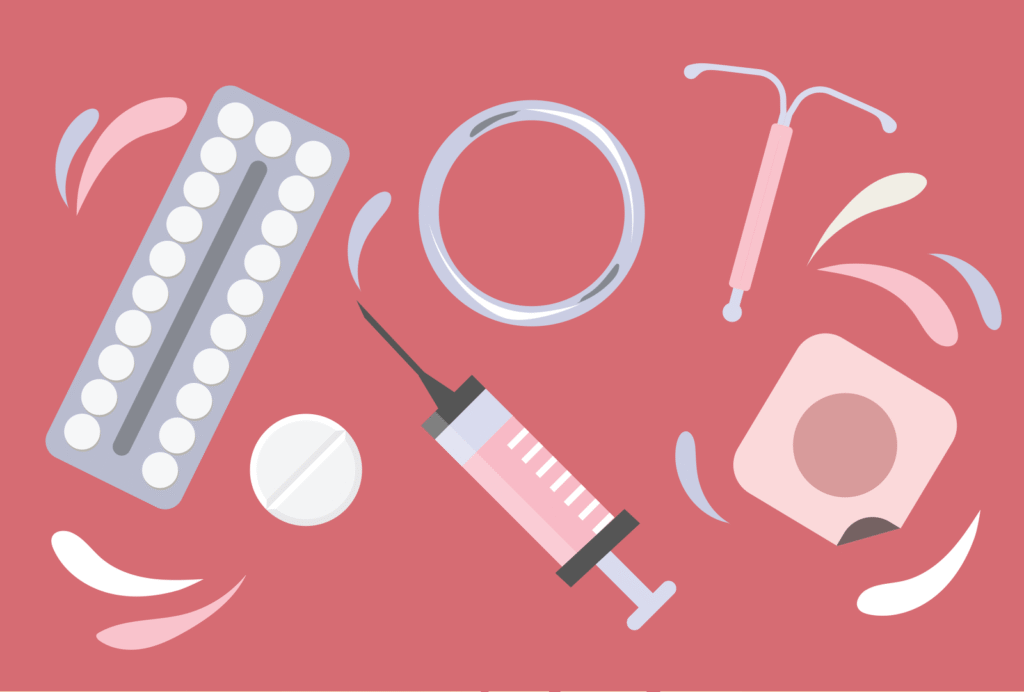
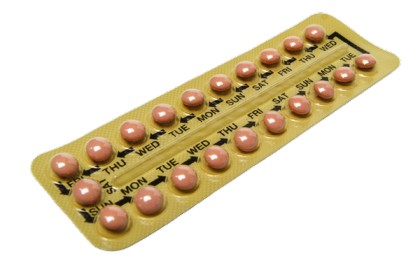
Contraceptive drugs like COCs may be given to suppress ovulation and relieve pain. Usually given for 4-6 months, and many get permanent relief after this treatment has been stopped.
Dilation and Curettage (D&C) may be of help to remove necrotic tissue of the endometrium, but usually not encouraged since it increases the risk of infections.
Cervical stenosis can be treated by surgical widening of the canal.
Effective counselling is important since pain is usually psychological to avoid drug dependence and abuse.
Natural processes like childbirth or ageing can contribute to the reduction of pain as uterine muscles relax.
NSAIDs should be taken one day before onset of symptoms and continue for 2-3 days. All the listed NSAIDs should not be given to patients with active peptic ulcer disease.
Combined Oral Contraceptives (COCs)
Pilplan plus, Microgynon
COCs suppress ovulation leading to a decrease in the production of progesterone concentration, which is needed in the production of prostaglandin. They are recommended for cases that have failed to respond to NSAIDs. COCs should be given for at least 3 months (3 cycles).
Depot Progestogens
Depo provera, Injecta plan
Depot progesterone acts by suppressing ovulation and thus relieving dysmenorrhoea.
Secondary dysmenorrhea treatment
Management is according to the cause of dysmenorrhea.
For cases of causes of secondary dysmenorrhea, surgical measures (e.g Dilatation and curettage and presacral neurectomy, hysterectomy, etc.) can be the best strategy (treatment is determined by the cause).
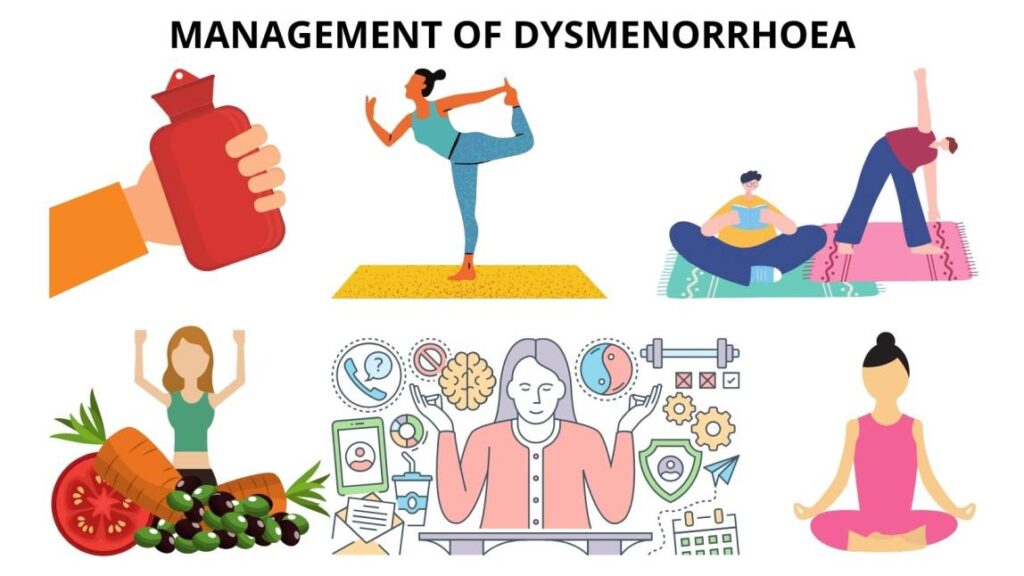
Lifestyle and Complementary Management:
Encourage enough rest, sleep, exercises, hygiene, and a good diet.
Explore alternative therapies such as hypnotherapy and acupuncture.
Nursing Management
Nursing Diagnosis: Acute pain related to increased uterine contractility evidenced by verbalization of the girl or woman.
Nursing Interventions:
Warm the abdomen to cause vasodilation and reduce spasmodic contractions.
Massage the painful abdominal area to reduce pain through therapeutic touch.
Perform light exercises to improve blood flow to the uterus and enhance muscle tone.
Implement relaxation techniques to reduce pressure and induce relaxation.
Administer analgesics as prescribed to block nociceptive receptors.
Nursing Diagnosis: Ineffective individual coping related to emotional stress evidenced by the patient’s verbalization.
Nursing Interventions:
Assess the patient’s understanding of the condition, as anxiety is influenced by knowledge.
Provide opportunities for the patient to discuss and identify coping mechanisms.
Ensure the patient gets periods of sleep or rest to promote relaxation.
Nursing Diagnosis: Risk for imbalanced nutrition less than body requirements related to nausea and vomiting.
Nursing Interventions:
Provide the patient with periods of sleep or rest for overall relaxation.
Encourage small, frequent feeds that are easily tolerated.
Administer antiemetic drugs like promethazine to block emetic centres.
Nursing Concerns
Assess the severity and characteristics of pain, including location, intensity, and duration.
Monitor vital signs and assess for signs of complications.
Evaluate menstrual patterns, duration, and heaviness of bleeding.
Assess the impact on the patient’s quality of life, emotional well-being, and daily activities.
Nursing Interventions
Provide pain management through prescribed medications.
Apply heat therapy and educate the patient on proper techniques.
Teach relaxation techniques, deep breathing exercises, and guided imagery.
Encourage rest in a comfortable position during painful episodes.
Educate the patient about the condition, its management, and treatment options.
Collaborate with the healthcare team for appropriate management.
Offer emotional support, acknowledging the patient’s pain and distress.
Habitual abortion refers to the occurrence of spontaneous abortion in three or more consecutive pregnancies.
Recurrent abortion is the consecutive loss of 3 or more fetuses weighing less than 500g.
It usually occurs before 20 weeks of gestation and the risk of further abortion increases with further pregnancy loss.
Approximately 1% of women experience this, with an increased risk of further abortion with each pregnancy loss. The high incidence suggests underlying causes.
Immunological factors: Women with a history of pregnancy loss lack immunological G (1gG) locking agent (rhesus incompatibility).
Endocrine factors: Hypersecretion of Luteinizing hormone may affect the oocyte or endometrium, leading to errors in implantation.
Polycystic ovaries in mothers increase the risk of early pregnancy loss.
Infections (TORCHES): Toxoplasmosis, Rubella, Syphilis, Herpes Simplex Virus, and Cytomegalovirus.
Structural abnormalities:
Uterine abnormalities like bicornuate uterus.
Cervical incompetence.
Management of Habitual Abortion
Mothers should be referred to specialized clinics for screening services.
The treatment of recurrent abortion depends on the cause.
Recurrent abortion due to cervical incompetence is treated with cervical suture/ cerclage at the 14th week of pregnancy and remains in place until the 38th week of pregnancy.
Specific treatment for any identified cause, e.g., cervical cerclage at 14 weeks using Shirodkar’s or McDonald’s method.
An absorbable suture is inserted at the level of the cervical os, remaining until 38 weeks or the onset of labour when it is removed.
Advertisements
CRIMINAL ABORTIONS
Criminal abortions are intentionally performed to end pregnancy, violating the law.
Implements like knives, sticks, and oxytocin drugs are used, often leading to septic abortion.
Treatment
Treatment follows the protocol for septic abortion.
At the medical Centre.
Mother is received and put in bed.
Counselling but she must be sent to the hospital
She should be started on Antibiotics for example ceftriaxone 1g stat IV or any other antibiotics available but in large doses.
Resuscitate the mother depending on her condition
Refer to hospital for further management
A full report will be received plus the general examination of the mother.
Re-assurance is necessary
Advertisements
At the Hospital.
The mother is admitted and preferably isolation done due to the fear of infection
Doctor is informed, Meanwhile the following should be done:
Histories are obtained from the mother.
General examination will be done and Vaginal examination too.
If sepsis has set in, she will be put on IV drugs immediately (antibiotics) like Gentamycin 160 mg o.d for 5/7 and metronidazole 500 mg 8 hourly for 5/7 then the evacuation of the products.
Dangers of Criminal Abortions:
Death due to haemorrhage.
Pelvic Sepsis.
Pelvic peritonitis.
General peritonitis.
Sterility.
Acute renal failure.
THERAPEUTIC ABORTION
Therapeutic abortion consists of evacuating the uterus and is undertaken as a treatment to save the life of the mother.
It is performed only by a doctor, with the consent of the woman and her husband.
Amenorrhoea refers to absence of menstruation which occurs in females during their reproductive age.
Types of Amenorrhoea
1. Primary amenorrhoea.
Primary amenorrhoea is failure to menstruate by the age of 16 in the presence of normal secondary sexual development.
or
The absence of menses by age 14 in the absence of normal secondary sexual characteristics.
Causes of Primary Amenorrhoea
1. Excessive Weight Loss: Reduction in body weight due to factors like restrictive diets or eating disorders which can lead to Disruption of hormonal balance crucial for menstruation.
2. Excessive Exercise or Stress: Intense physical activity or chronic stress may disrupt the normal hormonal fluctuations necessary for the menstrual cycle.
3. Physiological Delay: Family History: A delay in menstruation initiation, reported through family history, may contribute to a genetically influenced delay in onset.
4. Imperforate Hymen: The hymen, a thin membrane at the vaginal opening, is imperforate, obstructing menstrual blood outflow, hence retention of menstrual blood in the vagina.
5. Eating Disorders: Conditions like anorexia nervosa or bulimia may lead to nutritional deficiencies impacting reproductive hormones.
6. Thyroid Dysfunction: Disorders affecting the thyroid gland can disrupt the hormonal balance necessary for regular menstrual cycles.
7. Genetic Factors: Certain genetic syndromes or chromosomal abnormalities can impact reproductive development, delaying the onset of menstruation.
8. Chronic Illnesses: Long-term illnesses affecting various body systems can interfere with the hormonal balance required for menstruation.
9. Anatomical Abnormalities: Structural abnormalities in the reproductive organs such as Uterine or Ovarian Issues may hinder the normal menstrual process.
10. Hormonal Imbalances: Abnormalities in hormones like FSH (Follicle Stimulating Hormone) or LH (Luteinizing Hormone) crucial for puberty and menstruation.
11. Tumors or Growths: Non-cancerous growths or tumors affecting the ovaries or pituitary gland can disrupt hormonal balancing.
12. Medication Side Effects: Prolonged use or abrupt discontinuation of certain medications, such as hormonal contraceptives, may impact menstrual patterns.
13. Celiac Disease: Celiac disease, affecting nutrient absorption, may lead to disruptions in hormonal balance affecting menstruation.
2. Secondary amenorrhoea.
Secondary amenorrhoea may be defined as absence of menstruation for 6 months in women with established menstrual cycles.
Pregnancy should be ruled out in a patient who presents with secondary amenorrhoea.
Causes of Amenorrhoea
Normal physiology:
Pregnancy: During pregnancy, high levels of estrogen and progesterone maintain the endometrium, leading to amenorrhea.
Lactation: After delivery, prolactin is secreted in large quantities, partially suppressing LH production and preventing ovulation, resulting in amenorrhea.
Abnormal physiology:
Functional hypothalamic amenorrhea: Lower levels of FSH and LH due to hypothalamic dysfunction can lead to secondary amenorrhea. This condition may exclude organic diseases and exhibit abnormal GnRH secretion, low/normal LH concentrations, absent follicular development, and anovulation.
Premature Ovarian Failure: Accelerated atresia and dysfunction of follicular maturation can cause premature ovarian failure, leading to secondary amenorrhea.
Birth control pills: Hormonal birth control can affect menstrual cycles and cause secondary amenorrhea.
Malnutrition: Inadequate nutrition can disrupt hormone levels and lead to secondary amenorrhea.
Psychogenic factors: Emotional stress and psychological factors can impact hormonal balance, potentially causing secondary amenorrhea.
Infections (e.g., PID): Infections like pelvic inflammatory disease can disrupt normal reproductive function, leading to secondary amenorrhea.
Polycystic ovarian syndrome: PCOS can cause hormonal imbalances, leading to irregular menstrual cycles and potential secondary amenorrhea.
Emergency contraceptive pills: These pills can affect hormone levels and disrupt the menstrual cycle, potentially leading to secondary amenorrhea.
Diabetes mellitus: Poorly controlled diabetes can impact hormone levels and lead to secondary amenorrhea.
Resistant ovarian syndrome: This condition can lead to hormonal imbalances and disrupt the menstrual cycle, potentially causing secondary amenorrhea.
Radiation: Full doses of radiation can disrupt normal ovarian function, leading to secondary amenorrhea.
Drugs: Certain medications, especially hormonal contraceptives, can impact hormone levels and cause secondary amenorrhea.
Head injury: Traumatic head injuries can disrupt normal hormonal regulation, potentially leading to secondary amenorrhea.
Debilitating diseases: Conditions such as tuberculosis (TB), HIV/AIDS, and diabetes mellitus can disrupt normal hormonal balance, potentially leading to secondary amenorrhea.
Tumors of the pituitary gland, hypothalamus, ovaries, and uterus: Tumors in these reproductive and endocrine organs can disrupt normal hormonal function, leading to secondary amenorrhea.
Early onset of menopause: Premature menopause can cause secondary amenorrhea.
Idiopathic: In some cases, the cause of secondary amenorrhea may be unknown or unidentifiable.
Advertisements
Diagnosis and Investigation
Amenorrhoea is diagnosed by taking a proper history (history of change in weight, presence of stress, questions about excessive weight, presence of excessive body or facial hair)and physical examination.
The laboratory investigations are carried out to help identify the cause of amenorrhea and to rule out other causes.
Laboratory Investigations
Investigation
Remarks
Luteinizing hormone (LH)
LH is slightly elevated in the case of polycystic ovary syndrome.
Follicle stimulating hormone (FSH)
FSH is usually very high in the case of premature menopause.
Total testosterone levels
Testosterone level is slightly raised in polycystic ovary syndrome.
Thyroid stimulating hormone (TSH)
Helps to rule out hypothyroidism as a cause of amenorrhea.
Measurement of prolactin levels
High levels of prolactin are associated with hyperprolactinemia.
HCG test
It is used to rule out pregnancy.
Signs and Symptoms of Amenorrhoea
Cessation of Menses: The cessation of menstrual cycles is a primary and defining symptom of amenorrhea. It can be either primary (absence of menstruation by the age of 16) or secondary (absence of menstruation for three consecutive cycles in a woman who previously had regular periods).
Complaints of Infertility: Many women with amenorrhea may experience difficulties in conceiving (infertility). The absence of regular menstrual cycles can indicate underlying hormonal imbalances or reproductive system disorders, affecting the ability to conceive.
Vaginal Dryness and Decreased Libido: Hormonal imbalances associated with amenorrhea, such as low oestrogen levels, can lead to changes in vaginal moisture and lubrication, resulting in vaginal dryness. Additionally, decreased oestrogen levels may contribute to a reduced libido or interest in sexual activity.
Recent Excessive Weight Loss or Weight Gain: Amenorrhea can be linked to changes in body weight. Sudden and significant weight loss, as seen in eating disorders or excessive exercise, can disrupt the hormonal balance, leading to amenorrhea. Conversely, rapid weight gain, especially in conditions like polycystic ovary syndrome (PCOS), can also impact menstrual regularity.
Presence of Acne and Hirsutism: Hormonal disorders such as PCOS, characterized by elevated androgen levels, may present with symptoms like acne (skin condition) and hirsutism (excessive hair growth, especially in male-pattern areas). These symptoms can be indicative of hormonal disturbances contributing to amenorrhea.
Galactorrhea (Breast Milk Discharge): In some cases, elevated prolactin levels, a hormone responsible for milk production, can lead to galactorrhea (spontaneous discharge of milk from the breasts), which may accompany amenorrhea.
Pelvic Pain or Headaches: Certain underlying conditions causing amenorrhea, such as pituitary tumors or ovarian cysts, may present with symptoms like pelvic pain or headaches.
Mood Changes and Fatigue: Hormonal imbalances associated with amenorrhea can influence mood, leading to mood swings or changes. Fatigue may also be experienced due to disruptions in hormonal regulation.
Advertisements
Management of Amenorrhoea
This will depend on the cause. It may be medical, surgical, or psychological.
Nursing Management:
Assessment: Conducting a comprehensive evaluation of the woman’s medical and menstrual history, as well as performing a physical examination to identify the underlying cause of amenorrhea.
Emotional Support: Offering empathetic and non-judgmental support to address any emotional distress associated with the condition.
Education: Providing information on menstrual health, reproductive anatomy and physiology, and the potential causes and treatment options for amenorrhea.
Lifestyle Modifications: Encouraging women to adopt a healthy lifestyle, including regular exercise, balanced nutrition, stress reduction, and sufficient sleep, as these factors can contribute to hormonal balance regulation.
Contraception Counselling: Discussing contraceptive methods and family planning options to prevent unintended pregnancies.
Medical Management: Medical management of amenorrhea encompasses treating the root cause identified through investigations done. Various medical management options include:
Hormone Therapy: If hormonal imbalance, such as polycystic ovary syndrome or hypothalamic dysfunction, is determined as the cause of amenorrhea, hormone therapy may be prescribed to regulate hormone levels and restore menstruation.
Medications: Certain medications like progestins or combined oral contraceptives may be prescribed to induce menstruation or regulate the menstrual cycle.
Treatment of Underlying Conditions: If amenorrhea is a result of an underlying medical condition, such as a thyroid disorder or a pituitary tumour, appropriate medical treatment will be initiated to address the specific condition.
Hyperprolactinemia is treated by administration of bromocriptine 2.5mg 2-3 times daily which reduces prolactin levels which results into resuming of menstruation. Bromocriptine is an ergot alkaloid which directly opposes prolactin secretion. Radiotherapy is reserved for those patients who fail to respond to medical therapy.
Amenorrhoea due to polycystic ovary syndrome (PCO) Recommend Metformin 500mg 3 times daily which reduces insulin resistance.
Surgical Management: Surgical management is rarely required for the treatment of amenorrhea. However, in certain cases, surgery may be necessary to address structural abnormalities or correct anatomical issues contributing to the condition. For example:
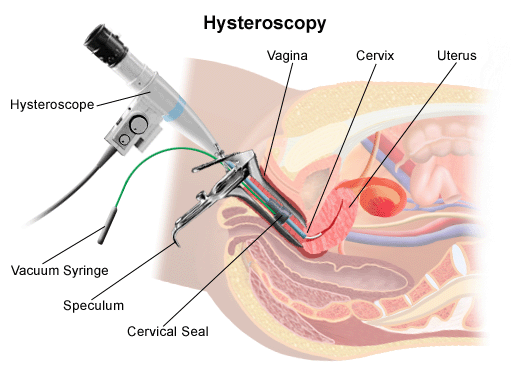
Hysteroscopic Surgery: This minimally invasive procedure involves the insertion of a thin, illuminated tube called a hysteroscope through the vagina and cervix to visualize and treat abnormalities within the uterus, such as polyps or adhesions.
Imperforate hymen is treated by incision and drainage. Very large amount of blood may be released, and if the septum is particularly thick, some form of plastic operation may be required.
Surgical Intervention: In some instances, surgical intervention may be essential to correct structural abnormalities in the reproductive organs or to remove tumours or cysts that are interfering with normal menstruation.
Psychological Management: Psychological management plays a crucial role in providing support for women with amenorrhea, as it significantly impacts their emotional well-being. It involves:
Counselling: Offering psychological counselling or referring women to mental health professionals who can assist them in coping with the emotional distress associated with amenorrhea.
Support Groups: Suggesting participation in support groups or facilitating connections with other women who have faced similar challenges to foster a sense of community and validation.
Body Image and Self-esteem: Addressing concerns related to body image and promoting a positive self-image by emphasizing that amenorrhea does not define femininity or a woman’s worth.
NB; Management of gynaecology conditions can be in the maternity centre and hospital. In the maternity centre investigations and operations may not be done from that place.
The maternity centre can manage some cases e.g. pregnancy, stress, lactational causes of amenorrhoea however the diagnosis of some causes of amenorrhoea that involves investigations are referred to the hospital.
Hormonal family planning refers to the use of hormonal methods to prevent pregnancy.
Hormonal contraceptive refers to birth control methods that act on the endocrine system (hormones).
These methods involve the use of hormones, usually synthetic versions of those naturally produced by the body, to regulate a woman’s menstrual cycle and prevent ovulation (the release of an egg from the ovaries). By preventing ovulation, hormonal methods make it difficult for sperm to fertilize an egg and thus prevent pregnancy.
These include;
Oral contraceptive pills
Implants
Injectable contraceptive
Emergency contraceptive pills
Hormonal Methods:
i. Oral Pills:
Method
Description
Combined Oral Contraceptives
Pills containing both oestrogen and progestin hormones
Progesterone-Only Pills
Pills containing only progestin hormone
Emergency Contraceptive Pills
Pills taken after unprotected sex to prevent pregnancy
ii. Implants:
Method
Description
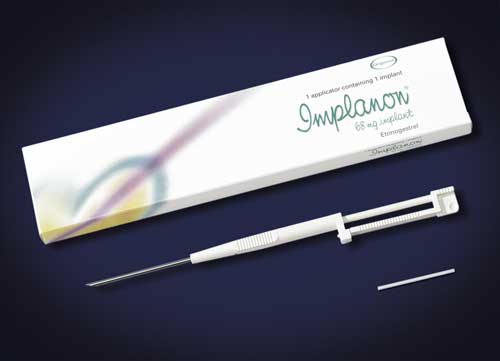
Implanon (1 Rod Capsule)
Subdermal contraceptive rod
Jadelle (2 Rod Capsules)
Subdermal contraceptive rods
Norplant (6 Rod Capsules)
Subdermal contraceptive rods
iii. Injectable Contraceptives:
Method
Description
Depo Provera
Injectable contraceptive administered every three months
Injector Plan
Injectable contraceptive
Sayana Press
Injectable contraceptive
Noristrate
Injectable contraceptive
iii. Emergency Contraceptives:
Emergency Contraceptive
Mechanism of Action
Lofemenal/Microgynon 4BD for 1 day (Low Dose COC)
Inhibits ovulation, thickens cervical mucus
Eugynon (High Dose COC) 2BD for 1 day
Inhibits ovulation, thickens cervical mucus
Regular POP (Ovrette/Microval) at Recommended Dose
Alters cervical mucus, inhibits sperm function
Levonorgestrel 2 stat
Delays ovulation, inhibits fertilization
Postinar 2 BD for 1 day
Alters cervical mucus, inhibits sperm function
Vikela/Levonelle-2/Norlevo Plan B
Delays ovulation, inhibits fertilization
Oral Contraceptive Pills
There are two main types of hormonal oral contraceptive formulations:
Combined hormonal contraceptive methods which contain both oestrogen and progestin thus, they are called combined oral contraceptives (COCs)
One which contains only progesterone or one of its synthetic analogues (Progestins) thus, it is called progestogen-only pills (POPs) method.
(i) Combined Oral Contraceptive Pills (COC)
Combined oral contraceptives contain both oestrogen and progesterone. It achieves effects of both hormones. Oestrogen suppresses ovulation and progesterone creates unfavourable conditions for egg transport and thickening of the cervical mucus to impair sperm entrance into the canal.
Examples
Lo-femenal
Pill Plan (Duofen)
Microgynon
Mechanism of Action:
Combined methods work by:
Suppressing ovulation (estrogenic effect)
Thickening cervical mucus, making it difficult for sperm to penetrate the uterus
Making the endometrium unsuitable for implantation of a fertilized egg (thin and atrophic due to constant progestogenic action)
Reducing sperm transport in the upper genital tract (fallopian tubes).
Effectiveness:
92 – 99.9% effective, depending on user compliance.
In very young women, typical effectiveness can be as high as 95.3%.
Failure rates decline with the duration of use and age of the user.
Failures may be due to method failure, client error, incomplete information from service providers, drug interactions, severe vomiting/diarrhoea, or expired pills.
Advantages:
Very effective if taken correctly.
Effective immediately.
Easily reversible.
Few side effects.
Convenient and easy to use.
Does not interfere with intercourse.
Causes regular and predictable periods.
May improve anemia.
Reduces dysmenorrhea and premenstrual tension.
Protects against ovarian and endometrial cancer, and some causes of PID.
Reduces the risk of ovarian cysts, benign breast disease, and ectopic pregnancy.
Can be provided by trained non-medical staff.
Disadvantages:
Effectiveness depends on daily pill intake, requiring strong motivation.
Increases chances of promiscuity.
Can cause Candida vulvitis and vaginitis.
May lead to thromboembolism and benign/malignant liver tumors.
Requires regular and dependable supply.
Reduces breast milk, especially in the first 6 months after delivery.
Not the most appropriate choice for lactating women unless no other method is available and there is a high risk of pregnancy.
Indications:
Women requiring a highly effective method.
Women wanting an easily reversible method.
Non-breastfeeding women or breastfeeding women after 6 months.
Women who are anaemic with heavy menstrual bleeding.
Women with a history of ectopic pregnancy.
Nulliparous women.
Women with a history of benign, functional ovarian cysts.
Women with a family history of ovarian cancer.
Women with menstrual cycle symptoms or irregular menstrual cycles.
Contraindications:
Absolute contraindications include cardiovascular diseases, liver disease, pregnancy, undiagnosed per vaginal bleeding, and oestrogen-dependent neoplasms.
Relative contraindications include obesity, varicosities, epilepsy, asthma, mood disorders, nursing mothers in the first 6 months, smoking, and gallbladder disease.
Side Effects:
Major side effects include hypertension, venous thromboembolism, and cholestatic jaundice.
Minor side effects can be due to oestrogen, progestin, or both, including nausea, vomiting, headache, leg cramps, weight gain, chloasma & acne, breakthrough bleeding, hypomenorrhea, amenorrhea, leucorrhea, and decreased libido.
Danger Signs of COCs:
Acute abnormal pain.
Severe headaches with blurred vision.
Pain in the chest with difficulty in breathing.
Pain in the calf muscles.
Indications for Withdraw:
Severe migraine.
Visual disturbance.
Sudden chest pain.
Severe cramps.
Excessive weight gain.
Severe depression.
Patient wanting pregnancy.
Awaiting major surgery.
Drug Interaction:
Decreases effectiveness of methyldopa, oral anticoagulants, and oral hypoglycemics.
Increases effectiveness of B blockers, corticosteroids, diazepam, aminophylline, and alcohol.
Other drugs that increase COC metabolism include phenobarbitone, antiepileptics (except sodium valproate and clozapine), rifampicin, griseofulvin, spironolactone, and ketoconazole.
WHO Medical Eligibility Criteria for Contraceptive Use.
Category 1: A condition for which there is no restriction for use of the contraceptive
Category 2: A condition where the advantages of using the method generally outweigh the theoretical or proven risks
Category 3: A condition where the theoretical or proven risk outweigh the advantages of using the method.
Category 4: A condition that represents unacceptable health risk if the contraceptive is used.
Who can use only if more appropriate methods are not available (WHO class3)
Women with high BP (greater than 160/100 but less than 180/110) and no vascular disease.
Women with symptomatic gall bladder disease.
Women age 35 yrs or older and light smokers (under 20 cigarettes a day)
Women taking drugs for epilepsy or anti-TB.
Women with unexplained vaginal bleeding (only if serious problem suspected)
Women who are fully b/feeding (6 wks to 6 months postpartum)
Women who are not b/feeding who are less than 3 weeks postpartum.
Women with h/o breast cancer and no current evidence of the disease.
Who should not use COCs (WHO Class 4)
Women with hypertension: blood pressure diastolic above 110 mm Hg. The health risk/benefit ratio is dependent upon the severity of the condition
Women with current or history of cardiac disease (heart disease or stroke). Among women with underlying vascular disease due to thrombosis, the increased risk of thrombosis with COCs should be avoided;
Women with thrombo-embolic disease (current and a history of or major surgery with prolonged immobilization). The increased risk of venous thromboembolism associated with COCs should have little impact on healthy women, but may have a big impact on women otherwise at risk for it;
Women within 2 weeks of child birth (Postnatal) and within 4 weeks or elective surgery;
Women with known or suspected cervical cancer. Theoretical concern that COC use may affect prognosis of the existing disease. In general, treatment of these conditions renders a woman sterile;
Women who are pregnant. As no method is indicated, any health risk is considered unacceptable. However, there is no known harm from COCs;
Women with undiagnosed breast lumps or breast cancer. Breast cancer is a hormonally sensitive tumor. The risk for progress of the condition may be increased among women with current or past history of breast cancer;
Women who are taking long-term drugs that could affect the pill’s efficacy. Commonly used liver enzyme inducers are likely to reduce the efficacy of COCs. Drugs which affect liver enzymes are the antibiotic rifampicin (note that other antibiotics will not affect pill efficacy), other drugs where another method should be used are: —griseofulvin, and anticonvulsants (such as phenytoin, carbamazepine, barbiturates, and primidone).
Women with severe headache (recurrent, including migraine with focal neurological symptoms). Focal neurological symptoms may be an indication for an increased risk of stroke( or cerebrovascular accident (CVA) is sudden damage to brain tissue caused either by a lack of blood supply or rupture of a blood vessel . The affected brain cells die and the parts of the body they control or receive sensory messages from ceaseto function.)
Women who are retarded or forgetful.
Women with sickle cell disease, as they have increased risk of thrombosis;
Women with trophoblast disease (current trophoblastic tumor)
Women who are to undergo major elective surgery with prolonged bed rest.
Client Information
Start between 1 st and 7 th day of monthly period
Take pills daily at the same time – at bed time if possible
Do not miss taking the pill any day
If you start after the 7 th day of monthly period; you need to use another FP method such condoms or to abstain from sex for one week.
Contraception is 7 days after initiation
You will have your monthly period when you are taking the brown pills. Do not stop taking the pills.
If a client misses, they should do the following:
If you miss one white pill, take it as soon as you remember, then continue normally.
If you miss 2 white or more days in a row; take two pills each day until all missed pills are taken and you are back on schedule. You must also use a condom for the next 7 days.
If you miss the brown pill, no worry. Just skip and continue
If you keep forgetting – may need to change method
ii) Progesterone Only Pills (POP)
Progestin-Only Pills are oral contraceptive pills which contain synthetic progestin and are taken orally every day at the same time of day to prevent pregnancy.
Mechanism of Action:
Reduces the frequency of ovulation.
Thickens cervical mucus, making it difficult for sperm to penetrate the uterus.
Partially inhibits ovulation.
Types of POPs available in Uganda:
Microval: 35 white pills, each containing 0.03 mg Levonorgestrel.
Ovrette: 28 yellow pills, each containing 0.075 mg Norgestrel.
Effectiveness:
Depends on user compliance.
Very effective if used correctly (83%-99%).
Crucial to take POPs at the same time every day, as effectiveness decreases even with a few hours’ delay.
In lactating women, POPs are nearly 100% effective, and they do not alter the quantity of milk.
Advantages of POPs:
Do not suppress lactation.
No estrogenic side effects.
Suitable for women with hypertension, thrombotic, cardiac, and sickle cell diseases.
Can be started at any time of the menstrual cycle and in the early postpartum period.
Decreased menstrual cramps.
Decreased amount of bleeding during periods.
Decreased severity of anaemia.
Do not increase blood clotting.
Some protection against pelvic inflammatory disease (progestins make cervical mucus thicker, reducing the likelihood of infection reaching the uterus and tubes).
Disadvantages of POPs:
Amenorrhea.
Must be taken at the same time every day.
Irregular periods, including spotting or bleeding between periods.
Prolonged or heavy vaginal bleeding.
For women who have had ectopic pregnancy, POPs do not prevent ectopic pregnancy as well as intrauterine pregnancy.
For women with a history of ovarian cysts, POPs do not protect against the development of future ovarian cysts.
Indications:
Women of any reproductive age or parity seeking pregnancy protection.
Breastfeeding women (6 weeks or more postpartum).
Post-abortion women (may start immediately).
Women who smoke.
Women with high blood pressure, blood clotting problems, or sickle cell disease.
Women unable to take Combined Oral Contraceptives (COCs) but want to take Pills.
Who should not use POPs (Class 3):
Women breastfeeding and less than 6 weeks postpartum.
Women with jaundice.
Women taking anti-epileptic and anti-TB medication.
Women with unexplained vaginal bleeding.
Women with breast cancer.
Women concerned about changes in their menstrual bleeding pattern.
Women unable to remember taking a pill every day (no more than 3 hours late).
Who should not use POPs (Class 4):
Women known or suspected to be pregnant.
Women who are known or suspected to be pregnant. POPs should not be initiated if a woman is pregnant. However, there is no known harm to mother or fetus if POPs are used during pregnancy;
Signs of problems from POPs warranting immediate return to clinic
Severe lower abdominal pain.
Heavy bleeding (twice as long and as much).
Migraine headaches, repeated very painful headaches, or blurred vision.
Signs of problems from POPs warranting immediate return to clinic:
Advertisements
Severe lower abdominal pain.
Heavy bleeding (twice as long and as much).
Migraine headaches, repeated very painful headaches, or blurred vision.
Client Instructions:
Start between the 1st and 7th day of the monthly period.
If started after the 1st day of bleeding, abstain from intercourse or use another method for the next 48 hours.
Take pills daily at the same time.
Do not miss taking the pill any day.
Return to the clinic for more pills before finishing the last pack.
Severe diarrhoea or vomiting reduces pill effectiveness. Use a backup method or abstain from sex while taking the pills and for 48 hours after.
If client misses taking pills:
If more than 3 hours late, take it as soon as remembered and the next pill at the usual time. Use a backup method or abstain for the next 48 hours.
If miss two or more days, take one as soon as remembered, continue as usual, and use a backup method or abstain for the next 48 hours.
If consistently forgetting, consider another method and seek counseling.
Contraindications:
Pregnancy: Progestin-Only Pills (POPs) should not be initiated if a woman is pregnant.
Unexplained vaginal bleeding: POPs are contraindicated in cases of unexplained vaginal bleeding, and immediate medical attention is advised to determine the cause.
Recent history of breast cancer: Women with a recent history of breast cancer are advised against using POPs due to potential hormonal interactions that could affect cancer progression.
Arterial diseases: Individuals with arterial diseases, such as a history of stroke or cardiovascular issues, should avoid POPs as they may pose additional risks to vascular health.
Thromboembolic diseases: Those with a history of thromboembolic diseases, involving blood clotting, are at an increased risk when using POPs, making it a contraindicated option.
Active hepatic diseases: Presence of active liver diseases is a contraindication, as POPs can impact liver function, and their use might exacerbate hepatic conditions.
Hypertension: Women with hypertension are advised against using POPs, as the hormonal components may contribute to increased blood pressure.
Side Effects:
Amenorrhea: Some women may experience amenorrhea (absence of menstruation) as a side effect of POPs, which is generally considered a normal response to hormonal changes.
Spotting: Spotting, or irregular bleeding between periods, can occur, and individuals should be aware that this is a common side effect that usually diminishes with time.
Prolonged or heavy bleeding: While some may experience prolonged or heavy bleeding, this side effect should be discussed with a healthcare provider to ensure it is not indicative of an underlying issue.
Lower abdominal pain: Lower abdominal pain may occur.
Weight gain or loss: Changes in weight, either gain or loss, may be observed.
Jaundice: Jaundice, characterized by yellowing of the skin or eyes, is a rare but serious side effect.
Nausea and vomiting: Nausea and vomiting may occur initially but often subside.
Headache with blurred vision: Headaches with blurred vision may be experienced.
Excessive hair growth: Some individuals may notice changes in hair growth patterns.
Breast fullness or tenderness: Breast fullness or tenderness is a common side effect that usually resolves over time.
High blood pressure: An increase in blood pressure may occur in some individuals
Implants
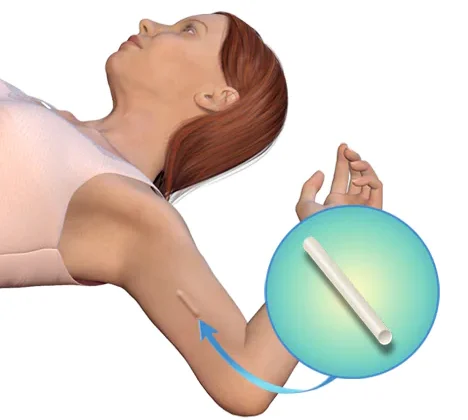
Implants are small, flexible rods or capsules that are inserted under the skin of a woman’s upper arm.
These implants release a steady, low dose of hormones (usually a progestin hormone) into the bloodstream over an extended period. The most common types of contraceptive implants include Implanon, Jadelle, and Norplant.
Implants are considered a reversible form of contraception, and their effectiveness is not dependent on user compliance once inserted. They are suitable for women who want a reliable, long-term birth control option without the need for daily or frequent intervention.
Types:
Implanon: A single rod capsule effective for 3 years.
Jadelle: Two rods of levornogestrel each 75mg capsules providing protection for 5 years.
Norplant: Consists of 6 rods each with 36mg levornogestrel capsules labelled for 5-7 years.
Modes of Action:
The hormonal release from these implants serves to prevent pregnancy by thickening the cervical mucus within 24 hours, hindering sperm entry into the uterus, inhibiting ovulation (the release of eggs from the ovaries), and altering the uterine lining to make it less receptive to a fertilized egg. Implants are highly effective and offer long-term contraception, ranging from three to seven years, depending on the specific type.
Insertion: Inner aspect of non dominant arm, 6 – 8 cm above elbow fold under local anesthesia. This is at day1, immediate after abortion or 3weeks postpartum.
Removal: Approximately 3 to 5 years
Advantages:
Very effective within 24 hours after insertion.
Easily reversible with no delay in returning to fertility after removal.
Reduces frequency and intensity of sickle cell crises.
Highly effective for long-term contraception.
Shares benefits with Depo Provera.
Common Side Effects and Disadvantages:
Changes in menstruation patterns.
Spotting.
Rare instances of heavy bleeding.
Amenorrhea.
Does not protect against STIs, including HIV/AIDS.
Discomfort in the hand after insertion.
Possible weight changes (overweight or weight loss).
Minor surgical procedure required for both insertion and removal.
Indications:
Breastfeeding post-partum mothers.
Adolescents.
Post-abortion contraception.
Women with sickle cell disease.
Women awaiting surgical contraception.
Women on treatment, e.g., ARVs.
Contraindications:
Serious problems with the heart or blood vessels.
Breast cancer history.
Liver diseases leading to jaundice.
Pregnancy.
Signs and Problems Requiring Medical Attention:
Soreness at the site of insertion.
Capsules coming out.
Severe headaches.
Heavy bleeding, exceeding the usual amount and duration.
Pregnancy.
Missed period after several regular cycles.
Injectable Contraceptives
Examples
Depo Provera (Depo Medroxyprogesterone acetate (DMPA), single dose of 150 mg I.M every 12 weeks. (Injecta Plan)
Sayana Press 104mg, 0.65ml Subcutaneously
Noristerat (Norethisterone) 200mg every 8 weeks for 24 weeks, then every 12 weeks.
Norigynon/Mesigyna (50 mg norethindrone enanthate plus 5 mg estradiol valerate) ; Both given monthly.
These contraceptives contain a single type of hormone, progestin.
Depo Provera
Depo Provera is a hormone used for contraception. It is given by injection and its effects will last for three months at a time.
Mode of Action
Inhibits ovulation.
Thickens cervical mucus, hindering sperm entry.
Thins the uterine lining, reducing chances of fertilized egg implantation.
Indications
Breastfeeding mothers after 6 weeks or immediately if not breastfeeding.
Women needing long-term contraception.
Known/suspected HIV-positive women.
Women with sickle cell disease.
Women unable to use COC due to oestrogen content.
Women awaiting surgical contraception.
Advantages
Very effective.
Does not suppress lactation.
Easy to remember return dates.
Private usage.
No oestrogen-related side effects.
Reduces sickle cell crisis frequency.
Non-interference with sex.
Disadvantages
Changes in menstrual bleeding.
Spotting (common in the first 3 months).
Amenorrhea (common after 1st injection and after 9-12 months).
Prolonged heavy vaginal bleeding.
Weight changes.
Irreversible injection.
Delayed return of fertility.
Loss of libido.
Does not protect against STIs/HIV/AIDS.
Management
Depo Provera 150mg deep IM into deltoid or buttock muscle.
No rubbing to avoid increased absorption.
Advise abstinence or backup FP method for the first 7 days after injection.
Return for the next dose 12 weeks after the injection.
Sayana Press
Sayana Press is a contraceptive injection that women can give to themselves to prevent pregnancy. It’s given under the skin, at the front upper thighs or abdomen. The injection releases medication that runs through your bloodstream over a period of 13 weeks.
Sayana press ® is a single-dose container with 104 mg Medroxyprogesterone acetate (MPA) in 0.65ml suspension (104mg) formulated for subcutaneous.
It is administered subcutaneously into the anterior thigh or abdomen or arm.
The efficacy of Sayana press depends on adherence to the recommended dosage schedule of administration.
Composition
Single-dose container with 104 mg Medroxyprogesterone acetate (MPA) in 0.65ml suspension.
Administration
Subcutaneously into the anterior thigh, abdomen, or arm
Emergency contraception (EC) serves as a preventive measure for unintended pregnancies following unprotected sexual intercourse, condom rupture, missed pills, or sexual assault.
It should be regarded as an emergency measure and not as a routine contraceptive method. EC does not terminate pregnancy. It encompasses hormonal, anti-progestin, and other methods.
Types
Emergency Contraceptive Pills (ECP)
Progesterone-Only Pills Regimen
When to Start?
EC should be initiated within 3 -5 days or 72 -120 hours, with earlier administration being more effective, following unprotected sexual intercourse. Intrauterine contraceptive devices (IUCDs) with copper introduction, within a maximum period of 5 days, can prevent conception after accidental unprotected sexual exposure.
Mechanism of Action
Prevents implantation
Failure rate is about 1%
Effectiveness is over 99% in preventing pregnancy
NOTE:
Post-coital contraception is solely for emergency use and is not effective if used regularly, except for copper IUCDs.
Women seeking emergency contraception should also be counselled about regular contraceptive options, promoting consistent and correct usage.
Referral to relevant services, such as HIV counselling, testing, post-exposure prophylaxis (PEP), and treatment for sexually transmitted infections (STIs), is essential.
Specialized services for sexual and gender-based violence should also be considered.
Basic Steps of Client Care for ECP
Greet and introduce yourself.
Maintain a respectful attitude.
Ensure confidentiality of the discussion.
Explain different ECP options, including usage, side effects, and the need for referral or follow-up.
Encourage questions from the client.
Discuss regular contraception options.
Conduct counselling with active client involvement, reassurance of confidentiality, and in a private and supportive environment.
Examples of ECP:
Ethinyl estradiol 2.5mg b.d X 5/7
Conjugated oestrogen 15mg b.d X 5/7
Levonorgestrel 0.75mg stat and after 12 hours.
Mifepristone 600 mg stat – single dose.
Copper IUDs inserted within 5 days.
Others: Postinor, Microgynon, Eugynon.
Indications
Unprotected sexual intercourse
Rape survivors
Contraceptive method failure
Missed contraceptive pills or injections
Delay in taking pills
Sexual assault or first-time intercourse
Contraindications
Pregnancy
After 120 hours or 5 days of unprotected sex
Emergency Contraceptive
Dosage
Mechanism of Action
Lofemenal/Microgynon 4BD for 1 day (Low Dose COC)
4 tablets once
Inhibits ovulation, thickens cervical mucus
Eugynon (High Dose COC) 2BD for 1 day
2 tablets twice
Inhibits ovulation, thickens cervical mucus
Regular POP (Ovrette/Microval) at Recommended Dose
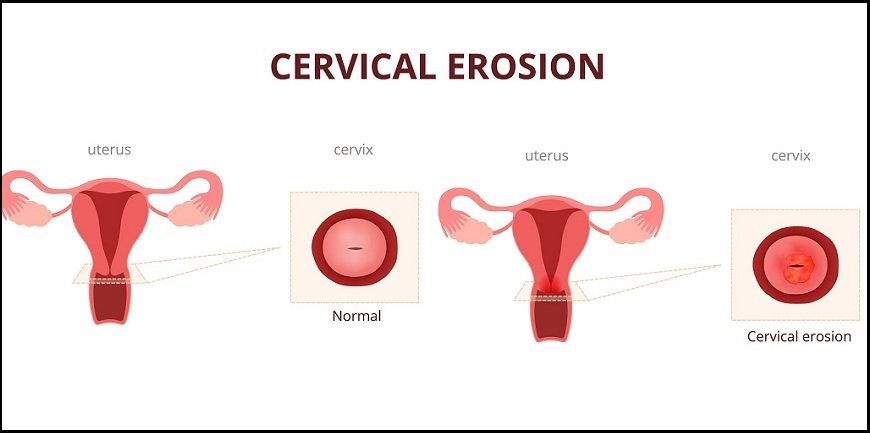
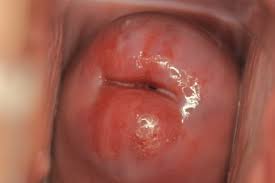
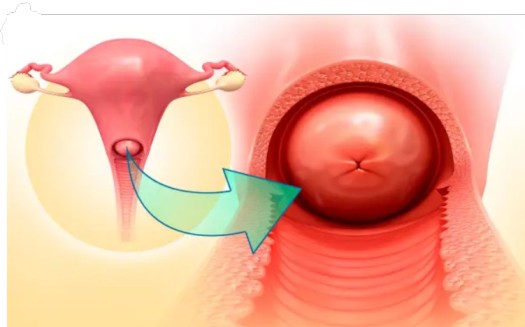
Cervical ectropion is a condition where cells from inside the cervix form a red, inflamed patch on the outside the cervix.
Cervical ectropion is a condition in which there is a raw-looking area on the cervix.
Cervical ectropion happens when cells from inside the cervical canal grow onto the outside of the cervix. These cells are called glandular cells. Glandular cells are red, so the area may look red. Cervical ectropion is sometimes called cervical erosion or cervical ectopy.
This is a benign (non-cancerous) condition and does not lead to cervical cancer.
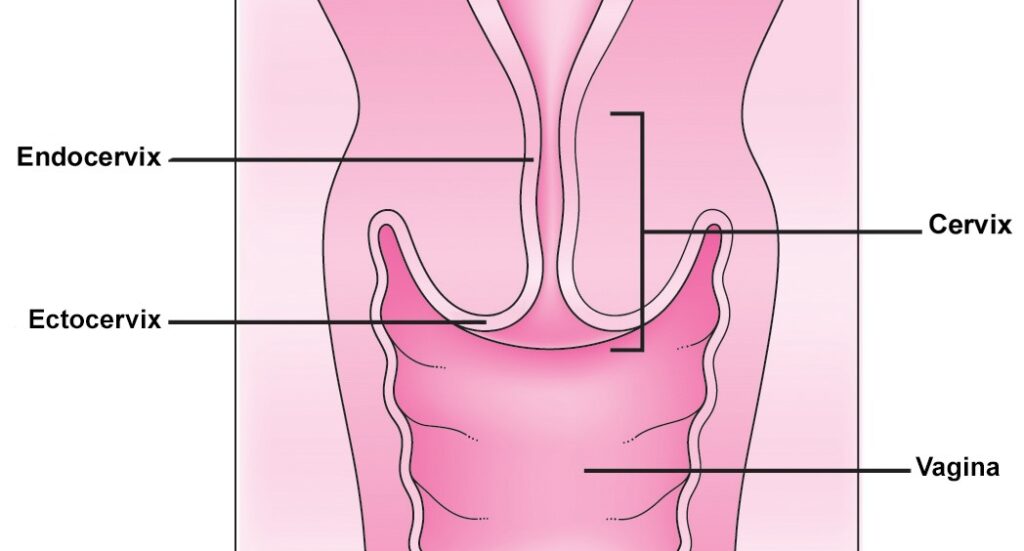
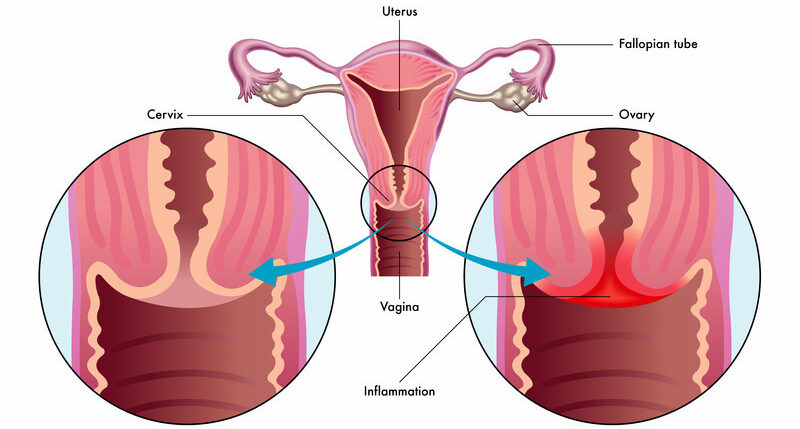
The cervix is the lower portion of the uterus. It is composed of two regions; the ectocervix and the endocervical canal.
Endocervical canal (endocervix) – the more proximal, and ‘inner’ part of the cervix. It is lined by a mucus-secreting simple columnar epithelium.
Ectocervix – the part of the cervix that projects into the vagina. It is normally lined by stratified squamous non-keratinized epithelium. A cervical ectropion is the presence of everted endocervical columnar epithelium on the ectocervix. This change is thought to be induced by high levels of oestrogen and does not represent metaplasia.
Etiology
The most common cause of a Cervical Ectopy is hormonal changes. Women who are taking oral contraceptives often have cervical ectopy. This is thought to be a response to high levels of oestrogen in the body. The cells which line the inside surface of the cervix often travel and sit on the exterior surface of the cervix. This can be seen when examination with a speculum is performed.
It is thought that cervical ectropion is induced by high levels of oestrogen. Therefore, factors that increase the risk of ectropion are related to those that increase levels of oestrogen:
Use of the combined oral contraceptive pill
Pregnancy
Adolescence
Menstruating age (it is uncommon in postmenopausal women)
Clinical Features of Cervical Erosion
Cervical ectropion is most commonly asymptomatic. It can occasionally present with post-coital bleeding, intermenstrual bleeding, or excessive discharge (non-purulent). On speculum examination, the everted columnar epithelium has a reddish appearance – usually arranged in a ring around the external os.
Advertisements
Unexpected Vaginal Bleeding: Cervical ectropion can lead to unexpected vaginal bleeding, which may occur spontaneously or be triggered by factors like sexual intercourse. The raw area on the cervix, exposed due to ectopy, is more susceptible to irritation and bleeding.
Spotting or Blood-Streaked Discharge: Women with cervical ectropion may experience spotting or a discharge with streaks of blood. This is a result of the fragile blood vessels in the exposed glandular cells, which can rupture easily, causing small amounts of bleeding.
Common Occurrence During or After Sexual Intercourse: Bleeding is often associated with sexual intercourse. The friction and pressure exerted during penetration can irritate the raw area on the cervix, leading to bleeding. This may not happen every time but can be a recurring issue for some women.
Association with Vaginal Infections (Thrush or Bacterial Vaginosis): Presence of vaginal infections such as thrush or bacterial vaginosis can exacerbate the symptoms of cervical ectropion. These infections cause additional irritation to the already sensitive area, leading to increased risk of bleeding.
Possibility of Asymptomatic Cases: Some women may have cervical ectropion without experiencing noticeable symptoms. The condition may only be identified during routine examinations, such as Pap smears.
Investigations of Cervical Erosion.
Cervical erosion/ectropion is diagnosed through a clinical examination. The main role of any investigation is to exclude other potential diagnoses:
Pregnancy test: To rule out pregnancy as a cause of cervical erosion
Triple swabs – if there is any suggestion of infection (such as purulent discharge), endocervical and high vaginal swabs should be taken. (A triple swab refers to the collection of three separate swab samples from different areas of the reproductive system during a medical examination)
Cervical smear – to rule out cervical intraepithelial neoplasia. If a frank lesion is observed, a biopsy should be taken (note that biopsies are not performed as routine).
Advertisements
Management of Cervical Erosion
Cervical ectropion is not a harmful condition and does not usually require treatment unless symptomatic.
First-line treatment is to stop any oestrogen-containing medications – most commonly the combined oral contraceptive pill. This is effective in the majority of cases.
If symptoms persist, the columnar epithelium can be ablated, using cryotherapy or electrocautery. This will result in significant vaginal discharge until healing is completed.
Medication to acidify the vaginal pH has been suggested, such as boric acid pessaries.
Mostly cervical erosion is present in women who do not have any symptoms and thus no specific treatment is advised.
There are three different versions of cauterization therapy:
Diathermy: This uses heat to cauterize the affected area.
Cryotherapy: This uses very cold carbon dioxide to freeze the affected area. A 2016 Study found this to be an effective treatment for women with cervical ectropion who were experiencing a lot of discharge.
Silver nitrate: This is another way to cauterize the glandular cells.
After the treatment, the doctor may recommend that a woman avoids sexual activity and using tampons for up to 4 weeks. After this time, her cervix should have healed.
If a woman experiences any of the following after the treatment, she should go back to the doctor:
Discharge that smells bad
Heavy bleeding (more than a average period)
Ongoing bleeding
CERVICAL POLYPS
Cervical polyps are benign growths protruding from the inner surface of the cervix.
They are benign tumours arising from the endocervical epithelium and may be seen as smooth reddish protrusion in the cervix.
Advertisements
They are usually asymptomatic, but a very small minority can undergo malignant change. They are estimated to be present in 2-5% of women.
Types of Cervical Polyps
Ectocervical Polyps:
Location: Ectocervical polyps originate from the outer surface of the cervix, protruding into the vaginal canal.
Characteristics: These polyps typically emerge from the stratified squamous non-keratinised epithelium of the ectocervix. Due to their external location, they are readily visible during routine gynecological examinations.
Appearance: Ectocervical polyps often present as finger-like or grape-like growths extending from the cervix. Their appearance may vary in size, and they are usually distinguishable by their pedunculated or stalk-like structure.
Symptoms: While ectocervical polyps are frequently asymptomatic, they can cause abnormal vaginal bleeding, spotting, or post-coital bleeding when symptoms are present. Their visibility facilitates diagnosis during speculum examinations.
Endocervical Polyps:
Location: Endocervical polyps develop within the endocervical canal, the more proximal and inner part of the cervix.
Characteristics: These polyps arise from the mucus-secreting simple columnar epithelium lining the endocervical canal. Unlike ectocervical polyps, their location within the canal makes them less visible during routine examinations.
Appearance: Endocervical polyps are less noticeable externally but may be detected through imaging techniques like ultrasound or hysteroscopy. They may obstruct the cervical canal, leading to symptoms like infertility or irregular bleeding.
Symptoms: Similar to ectocervical polyps, endocervical polyps may cause abnormal bleeding or spotting. However, their impact on fertility or interference with cervical smears may be more pronounced due to their location.
Clinical Features of Cervical Polyps
Often asymptomatic, identified only through routine cervical screening.
Advertisements
Abnormal vaginal bleeding:
Menorrhagia (heavy menstrual bleeding)
Intermenstrual bleeding (bleeding between periods)
Post-coital bleeding (bleeding after sex)
Post-menopausal bleeding
Increased vaginal discharge
Rarely, large polyps can block the cervical canal, causing infertility.
On speculum examination, cervical polyps are usually visible as polypoid growths projecting through the external os.
Aetiology
The aetiology of cervical polyps remains unknown. Some of the risk factors are:
Premenopausal women
Multigravida
Sexually transmitted infections
Previous history of cervical polyps
Chronic cervicitis.
Chronic inflammation
Abnormal response to oestrogen (cervical polyps are associated with endometrial hyperplasia)
Localized congestion of the cervical vasculature
Investigations
The definitive diagnosis for a cervical polyp is histological examination after its removal. Therefore, the main role of any other investigations is to exclude alternative causes of the symptoms:
Triple swabs – if there is any suggestion of infection (such as purulent discharge), endocervical and high vaginal swabs should be taken.
Cervical smear – to rule out cervical intraepithelial neoplasia (CIN). Sometimes the polyp can prevent the smear being taken, in which case the smear should be repeated after the polyp has been removed.
Management
Cervical polyps have a small (less than 0.5%) risk of malignant transformation – and so it is common practice to remove them whenever they are identified (even if asymptomatic).
Polyps are easily removed in the doctor’s office, without anaesthesia.
They’re simply held and twisted off gently or taken off with polypectomy forceps or ring forceps. Any resulting bleeding can be cauterized with silver nitrite. They’re then sent to the laboratory to make sure that there’s no sign of cancer.
If the polyps is infected antibiotics may be prescribed.
Larger polyps, or those that are more difficult to access can be removed by diathermy loop excision in the colposcopy clinic, or under general anaesthesia if the base of the polyp is broad.
Any excised polyps should be sent for histological examination to exclude malignancy. They have a recurrence rate of 6-12%.
Advertisements
CERVICAL TRAUMA
Cervical trauma refers to any injury occurring on the cervix.
Etiology
It is caused by
Childbirth: Trauma during childbirth, especially prolonged or difficult deliveries, can result in cervical injuries.
Rough Sexual Intercourse: Forceful or rough sexual activities may cause trauma to the cervix.
Surgical Procedures: Gynaecological surgeries or procedures involving the vaginal canal can lead to cervical trauma.
High Vaginal Fluid Acidity: Elevated acidity levels in vaginal fluids can contribute to irritation and potential trauma.
Tampon Usage: Improper or forceful tampon insertion and removal may cause cervical injuries.
Criminal Abortion: Unregulated and unsafe abortion practices, including the use of inappropriate instruments, can result in cervical trauma.
Gynaecological Procedures: Certain medical interventions, such as dilation and curettage (D&C), may pose a risk of cervical trauma.
Clinical Features
Dyspareunia: Pain during sexual intercourse is a common symptom of cervical trauma.
Postcoital Bleeding: Bleeding following sexual activity is a notable clinical feature.
Vaginal Bleeding: Unexplained or persistent vaginal bleeding may indicate cervical trauma.
Lower Abdominal Pain: Discomfort or pain in the lower abdominal region can be associated with cervical injuries.
Investigations
Speculum Examination: A thorough examination using a speculum helps visualize any visible signs of trauma.
High Vaginal Swab: Swabs may be taken to assess for infections or abnormal discharge.
Cryotherapy: In some cases, cryotherapy may be used to evaluate and treat cervical trauma.
History Taking: Understanding the patient’s medical history and the context of the symptoms is crucial.
Advertisements
Management
Antibiotics: Prescribe broad-spectrum antibiotics to prevent or address potential infections resulting from cervical trauma.
Analgesics: Provide analgesic medications to manage pain associated with cervical trauma. Nonsteroidal anti-inflammatory drugs (NSAIDs) or other suitable pain relievers may be recommended.
Restrictions for Sexual Intercourse: Emphasize the importance of abstaining from sexual activity until the cervical trauma has adequately healed. Educate the patient on the potential risks of premature resumption of sexual intercourse.
Rest and Sleep: Advice on sufficient rest and sleep to support the body’s natural healing processes. Stress the importance of avoiding activities that could strain the pelvic region during the recovery period.
Follow-up Examinations: Schedule regular follow-up examinations to monitor the progress of cervical healing. Adjust the management plan based on the findings.
Pelvic Floor Exercises: Recommend simple pelvic floor exercises to promote muscle tone and support the healing of cervical tissues.
Hygiene Practices: Emphasize proper hygiene practices to prevent infections in the healing cervix.
Avoidance of Vaginal Products: Instruct the patient to refrain from using irritant vaginal products, such as douches, tampons or harsh soaps, during the recovery phase.
Psychological Support: Acknowledge the potential psychological impact of cervical trauma and provide emotional support. Encourage open communication about any concerns or anxieties related to the injury.
Patient Education: Educate the patient about the causes of cervical trauma and preventive measures. Provide information on recognizing warning signs that may necessitate immediate medical attention.
Monitoring for Complications: Monitor for any signs of complications, such as persistent bleeding, worsening pain, or signs of infection.
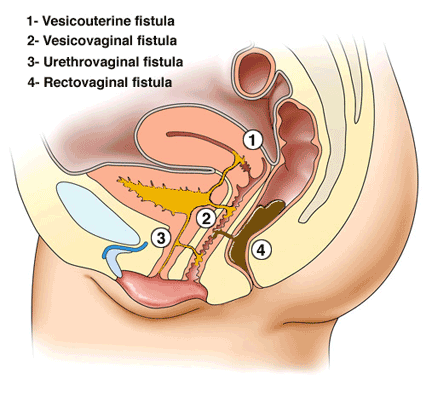
Vaginal Fistula is an abnormal communication (opening) of the vagina and the neighbouring -pelvic organs as a result of obstetrical causes e.g. delivery.
Urogenital Fistula: Abnormal communication between the urinary (ureters, bladder, urethra) and genital (uterus, cervix, vagina) systems.
A fistula is an abnormal communication between two or more epithelial surfaces.
Types of vaginal/obstetric fistula
Vaginal Fistula: A general term for a fistula formed within the vaginal wall.
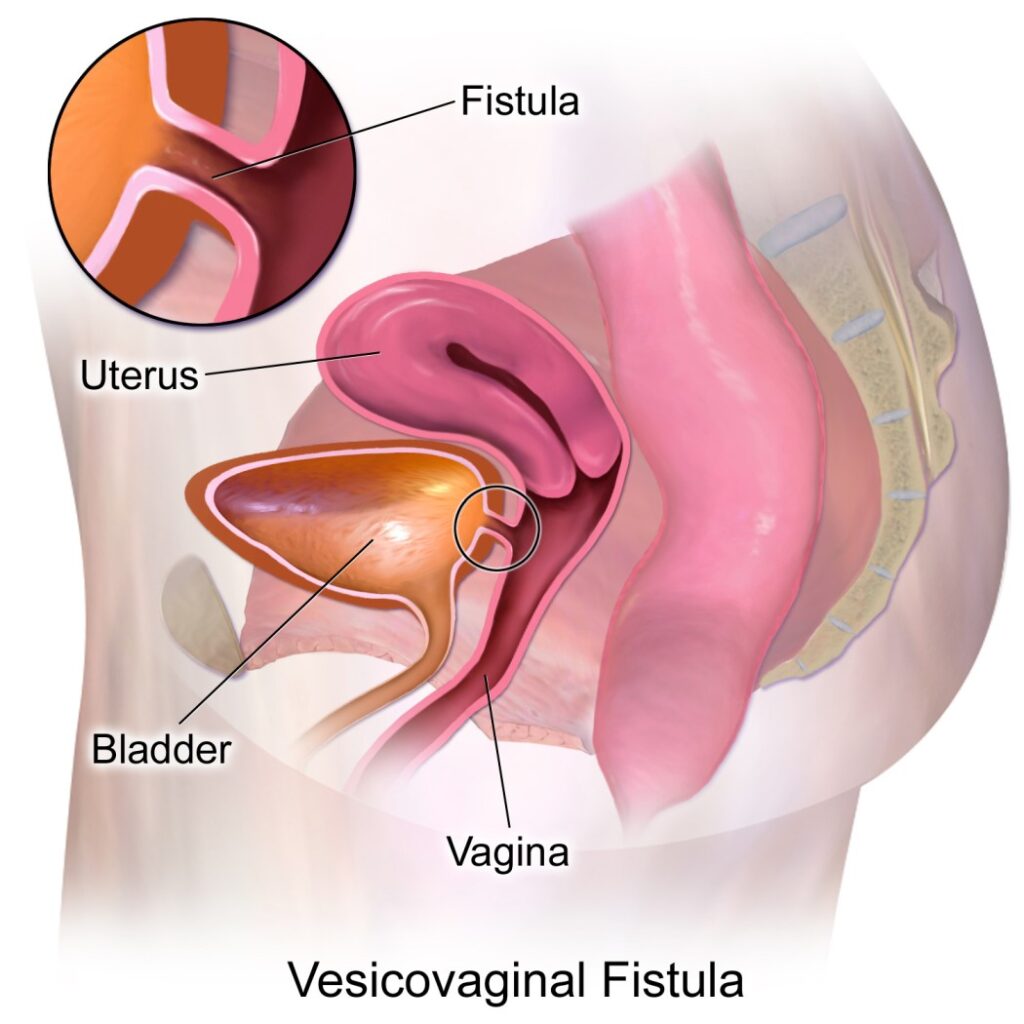
Vesicovaginal Fistula (VVF): When a vaginal fistula extends into the urinary tract, it is specifically referred to as vesicovaginal fistula. The most common type of urogenital fistula, occurring between the bladder and vagina.
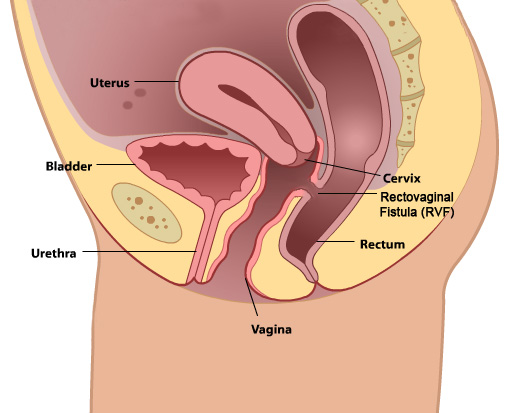
Rectovaginal Fistula (RVF): If the vaginal fistula opens into the rectum, it is termed a rectovaginal fistula.
Colovaginal Fistula: An occurrence where a vaginal fistula communicates with the colon.
Enterovaginal Fistula: When the opening of a vaginal fistula connects with the small bowel.
Anatomical Communications
Organ
Ureter
Bladder
Urethra
Vagina
Ureterovaginal
Vesicovaginal
Urethrovaginal
Cervix
Ureterocervical
Vesicocervical
Urethrocervical
Uterus
Ureterouterine
Vesicouterine
Not reported
General Causes of Urogenital Fistula
Obstetric Conditions/Procedures
Prolonged, Obstructed Labor: Prolonged pressure of the foetal head against the pelvic tissues during obstructed labour can cause ischemia and necrosis of the vaginal wall and bladder. This necrosis can create a fistula, typically between the bladder and vagina (vesicovaginal fistula).
Caesarean Section (Especially Repeat Cesareans): Surgical incisions through the bladder or close to the bladder during caesarean sections can cause direct injury or lead to ischemia. This can result in a vesicovaginal fistula if the bladder is inadvertently cut or damaged.
Bladder is Cut: Accidental incision into the bladder while performing the surgery.
Bladder Wall Sutured: Suturing the bladder wall during closure of the uterus can cause damage.
Adherent Bladder: In women with previous caesarean scars, the bladder may adhere to the uterine scar and tear during separation.
Caesarean Hysterectomy: This procedure involves the removal of the uterus following a caesarean delivery. The close proximity of the bladder to the uterus increases the risk of bladder injury. Damage to the bladder during this surgery can create a vesicovaginal fistula.
Operative Vaginal Delivery: Use of forceps or vacuum during delivery can cause trauma to the vaginal and bladder tissues. This trauma can lead to tissue necrosis and the development of a fistula.
Ruptured Uterus: Uterine rupture can involve the bladder, especially in patients with previous scars where the bladder is adherent.
Bladder Cut or Sutured: During repair of the uterus or hysterectomy, the bladder may be inadvertently cut or sutured.
Symphysiotomy: During the procedure to widen the pelvis, the bladder and urethra, if not properly displaced, can be damaged. This damage can lead to a vesicovaginal or urethrovaginal fistula.
Cervical Cerclage: Placement of a stitch around the cervix to prevent premature birth can sometimes cause damage to surrounding tissues if not properly placed. This damage can lead to a fistula between the cervix and bladder.
Gynaecological and Urological Procedures
Hysterectomy: Removal of the uterus can sometimes damage the bladder or ureters due to their proximity. This can result in vesicovaginal or ureterovaginal fistulas.
Myomectomy: Removal of fibroids from the uterus can inadvertently damage the bladder or ureters. This can lead to vesicovaginal or ureterovaginal fistulas.
Loop Excision of Cervix: Treatment for cervical dysplasia involves removing abnormal cervical tissue, which can sometimes damage nearby structures. This can create a fistula if the bladder is unintentionally injured.
Voluntary Interruption of Pregnancy: Procedures to terminate pregnancy can sometimes cause trauma to the bladder or ureters. This trauma can result in fistula formation.
Anterior Colporrhaphy: Surgery to repair a cystocele (bladder prolapse) can sometimes damage the bladder. This can lead to a vesicovaginal fistula.
Periurethral Bulking: Injection of materials around the urethra to treat incontinence can sometimes cause trauma. This can result in a urethrovaginal fistula.
Urethral Diverticulum Repair: Surgery to remove a diverticulum from the urethra can cause damage to surrounding tissues. This can result in a urethrovaginal fistula.
Ureteral Wall Stent: Placement of stents in the ureters can sometimes cause trauma to the ureters or bladder.This trauma can result in a ureterovaginal or vesicovaginal fistula.
Insertion of Shirodkar Stitch: Placement of a cervical stitch to prevent preterm birth can damage the bladder if not done carefully. This can create a vesicocervical fistula
Dilatation and Curettage (D&C): The procedure, especially during pregnancy termination, can cause trauma to the bladder or urethra. This trauma can result in the formation of fistulas.
Manchester Operation: Surgery for uterine prolapse can cause damage to the bladder or urethra. This can result in a vesicovaginal or urethrovaginal fistula.
Pelvic/Medical Conditions
Endometriosis: Abnormal growth of endometrial tissue can invade the bladder or ureters. This invasion can create fistulas due to chronic inflammation and tissue damage.
Gynecologic Cancers: Tumours from cancers like cervical, uterine, or ovarian cancer can invade the bladder or ureters. Surgical removal or the tumour itself can cause fistula formation.
Cervical Cancer (Stage 4): Advanced cancer can invade the bladder tissues. This invasion can create a vesicocervical fistula
Pelvic Irradiation: Radiation therapy for pelvic cancers can cause tissue necrosis in the bladder and surrounding areas. This necrosis can lead to vesicovaginal fistulas.
Infections (Tuberculosis, Lymphogranuloma Venereum): These infections can cause chronic inflammation and tissue damage in the urinary and genital tracts. This damage can lead to the formation of fistulas.
Intrauterine Device (IUD): IUDs can sometimes perforate the uterus and migrate, causing damage to the bladder. This can lead to a vesicovaginal fistula.
Retention of Vaginal Foreign Object: Forgotten or unrecognized foreign objects such as tampon, diaphragm, cervical cap, pessary in the vagina can cause chronic inflammation and tissue damage. This can result in fistula formation.
Accidental Trauma: Blunt or penetrating trauma to the pelvic region can cause direct injury to the bladder or urethra. This injury can lead to the formation of a fistula.
Sexual Trauma: Violent or forced sexual activity can cause severe trauma to the vaginal and bladder tissues. This trauma can result in vesicovaginal fistulas.
Mitomycin C Instillation: Chemotherapy agent used for bladder cancer can cause severe bladder irritation and necrosis. This necrosis can lead to fistula formation.
Bladder Stone: Large bladder stones can cause chronic irritation and erosion into the bladder wall. This erosion can create a vesicovaginal fistula.
Advertisements
Risk Factors of Fistula
Poverty: Limited access to healthcare can lead to poor management of obstetric and gynecological conditions, increasing the risk of fistulas.
Malnutrition: Poor nutritional status can weaken tissues, making them more susceptible to damage during childbirth or surgery.
Lack of Education: Deficient knowledge about prenatal care and safe childbirth practices increases the risk of complications leading to fistulas.
Early Childbirth: Young mothers often have smaller pelvic dimensions, increasing the risk of obstructed labour and subsequent fistula formation.
Lack of Healthcare: Inadequate access to skilled medical care during childbirth can result in prolonged obstructed labour or mismanaged surgical procedures.
High Parity: Multiple pregnancies can increase the risk of uterine and bladder prolapse, leading to a higher risk of fistula formation during childbirth or surgical procedures.
Prolonged Labour without Medical Assistance: Lack of timely medical intervention can lead to obstructed labor, increasing the risk of ischemic injury to the bladder and adjacent tissues.
Inadequate Prenatal Care: Poor prenatal care can result in undiagnosed or poorly managed conditions like fetal macrosomia or malpresentation, which can complicate delivery and increase fistula risk.
Pre Existing Medical Conditions: Conditions such as diabetes or hypertension can impair wound healing and tissue resilience, increasing susceptibility to fistulas.
Previous Pelvic Surgeries: Scar tissue from prior surgeries can complicate new procedures and increase the risk of bladder or urethral injury.
Use of Harmful Traditional Practices: P ractices like female genital mutilation or the Gishiri cut can cause direct injury to the urinary and genital tracts, leading to fistula formation.
Symptoms of Urogenital Fistula
Continuous Urinary Leakage: Persistent and unexplained leakage of urine from the vagina following recent surgery, a difficult vaginal delivery, or local trauma. The continuous passage of urine through the vaginal opening is due to an abnormal connection (fistula) between the bladder or urethra and the vagina.
Recurrent Cystitis or Pyelonephritis: Frequent bladder infections or kidney infections. The abnormal passage allows urine to stagnate and become infected, leading to recurrent urinary tract infections.
Unexplained Fever: Persistent fever without an obvious cause. Chronic infections related to the fistula can cause systemic symptoms such as fever.
Hematuria: Presence of blood in the urine. Trauma or infection around the fistula site can lead to bleeding into the urinary tract.
Flank, Vaginal, or Suprapubic Pain: Pain in the sides (flank), vagina, or above the pubic bone (suprapubic). Inflammation, infection, and ongoing leakage of urine can cause significant pain in these areas.
Abnormal Urinary Stream: Changes in the usual pattern of urination. The fistula can disrupt the normal flow of urine, leading to an abnormal urinary stream.
Vaginal, Vulvar, and Perineal Irritation: Irritation or discomfort in the vaginal, vulvar, and perineal areas. Constant exposure to urine can irritate these tissues, leading to inflammation and discomfort.
Foul Ammoniacal Odour: A strong, unpleasant smell resembling ammonia. Bacterial activity in the urine leads to the production of ammonia, causing a foul odour.
Severe Perineal Dermatitis: Severe skin irritation and inflammation in the perineal area. Continuous contact with urine can lead to dermatitis, characterized by redness, swelling, and irritation of the skin.
Greenish-Gray Phosphate Crystals in the Vagina and Vulva: Presence of greenish-gray deposits on vaginal and vulvar surfaces.Bacterial action on urea in urine leads to an alkaline environment, causing phosphate crystals to precipitate and deposit in the affected areas.
Social Isolation, Disrupted Sexual Relations, Depression, Low Self-Esteem, Insomnia: Emotional and psychological distress due to the condition. The constant leakage of urine and associated symptoms can lead to significant social and emotional impacts, including isolation, difficulties in sexual relationships, depression, low self-esteem, and sleep disturbances.
Diagnostic Signs and Examination Findings
Patient History
History of Prolonged and Obstructed Labor: Key indicator of potential fistula development.
Mother Reports Leakage of Urine: Continuous leakage without control is a classic sign of fistula.
Physical Examination
No Palpable Bladder on Abdominal Palpation: Indicates that urine does not accumulate in the bladder but leaks out.
Urine Smell: The patient often has a characteristic smell of urine.
Signs of UTI and Low-Grade Fever: Recurrent infections due to urine leakage.
Vulva Inspection: Visible dribbling of urine from the vagina.
Speculum Examination: Visible defect with urine escaping through it.
Diagnostic Tests
Methylene Blue or Gentian Violet Test: Injection of methylene blue or gentian violet dye into the bladder via a catheter. The presence of dye leaking into the vagina confirms the fistula.
Soft Tissue X-ray and Cystography: Show defects and injuries in the bladder.
Creatinine Content in Vaginal Fluid: High levels indicate urine leakage.
Cystoscopy: This endoscopic examination allows direct visualization of the bladder and urethra, helping to locate the exact anatomical origin of the fistula.
Soft Tissue X-ray: Helps to visualize the defect and confirm the presence of a fistula.
Speculum Examination: Direct visual inspection using a speculum to identify and assess the fistula.
Digital Examination: Manual examination to feel the fistula and surrounding tissues.
Subtraction Magnetic Resonance Fistulography: A specialized imaging technique that can provide detailed visualization of the fistula.
Endocavitary Ultrasound: Transrectal or transvaginal ultrasound, potentially with Doppler or contrast agents, to visualize the fistula. Transvaginal sonography can clearly show the exact site, size, and course of the fistula.
Biopsy: If malignancy is suspected, a biopsy of the affected tissue is taken for histologic examination to rule out cancer.
Advertisements
VESICO-VAGINAL FISTULA
Vesicovaginal fistula or VVF is an abnormal fistulous tract extending between the bladder (vesico) and the vagina that allows the continuous involuntary discharge of urine into the vaginal vault.
OR: It is the abnormal opening of the vagina and the urinary bladder.
Pathology of a urinary fistula
If the cause is a tear, urine escapes at once but the wound may not become infected immediately and primary union can occur in one week or two provided the urinary stream is diverted.
If the cause is pressure necrosis, the affected area will form a slough which eventually drops out leaving a fistula.
If the fistula is large (over 2 cm diameter) spontaneous healing is unlikely and scar tissue gradually forms a dense white ring round the edge of the fistula even fixing it to the pubic ramus.
Urinary fistula has a natural tendency to close by granulation, fibrosis, and contraction.
Types of VVF
Simple fistula: Only about 20% of obstetric fistulas can be defined as simple. Simple fistulas are less than 3 cm in diameter with no or only mild scarring and do not involve the urethra.
Complex fistula: A complex obstetric fistula can be described as being larger than 3 cm, involving the urethra and associated with reduced vaginal capacity from significant scarring and/or a reduced bladder volume. Sometimes the defect may be urethrovaginal, but more commonly both the urethra and bladder are involved and therefore the fistula is called a urethro-vesicovaginal.
Management of vesico – vaginal fistula
If the woman is very ill and the fistula is small and does not involve the urethra: she can be managed conservatively while treating the cause of the illness.
Small fistula: Small vesico-vaginal fistulas can often be repaired with a high chance of success. A catheter is passed into the bladder and left in place for several days to keep the bladder empty while the tissues heal.
For larger fistulas: If the tissues are badly damaged or if the fistula involves the urethra or if the tissues are very scarred and inflexible, delayed repair or reconstructive surgery may be needed.
With the conservative treatment of the large fistulae, a catheter is passed into the bladder through the urethra and left in place for several days to keep the bladder empty while the tissues heal.
Any indwelling catheter should be left in place for 2 to 3 weeks following the repair.
Insertion of the catheter: A catheter is inserted through the urethra to continuously drain urine from the bladder.
If urine is not draining, the catheter may be blocked. If the bladder is not emptying because the bladder muscle is not contracting, the catheter may be blocked or the catheter may have been inserted through the side of the urethra. If the catheter is in the vagina and not in the bladder, urine will not be draining from the catheter.
In the Health Center
Mother is encouraged on personal hygiene and referred to the hospital.
In Hospital
Mother is admitted to a gynaecological ward.
Doctor is informed and will carry out a gynaecological examination:
Genital examination with fingers, no instruments used for fear of enlarging the opening.
May carry out a speculum examination.
A self-retaining catheter is passed and the mother is kept on continuous bladder drainage as dripping of urine prevents healing.
Give a balanced diet including iron, vitamin supplements, and if necessary, blood transfusion to restore her general health.
Most fistulas will close spontaneously within 6 weeks as long as there is continuous bladder drainage, good health, and control of infections.
Use of antiseptic vaginal douches to clear any smell.
At the end of puerperium, a patient is assessed by means of speculum examination.
Previously, enough time was to be given to allow the tissue to heal and strengthen sufficiently.
Thereafter, a mother would be asked to go home and return for surgery after 3 months. Today, it can be repaired as soon as it is diagnosed.
During the resting and waiting time for the surgery, the following are necessary:
Reassurance
Plenty of rest
Good diet with high protein and vitamins for quick healing
Hygiene/vulva toilet
Wearing pads at all times and frequently changing them.
Use of a barrier cream to prevent excoriation of the skin, e.g., Zinc and Castor oil
Mother is put on continuous bladder drainage.
Actual Treatment
Repair the fistulae as soon as the patient is first seen.
Perform the necessary examination under anaesthesia to establish where urine is coming from and the appropriate position for repair.
This can be done together with the injection of dye through a catheter into the urinary bladder to observe where the opening is, as the dye will be seen coming out of it.
Then the fistulae can be repaired surgically.
Care After Repair
Care is similar to that for any mother after an operation or obstructed labour.
Mother is nursed in a supine position to prevent excessive pressure on the suture site.
Continuous bladder drainage to rest the bladder and allow proper healing.
Plenty of fluids to flush the bladder and prevent pressure on the wound. Any blood clot or debris is washed out, preventing urine stasis and urinary tract infections.
Maintain a fluid balance chart.
Observe the amount of urine passed and its colour, especially for blood clots which may block the catheter.
Bed is observed daily for wetness.
Remove the catheter after 2 weeks if the bed is dry. If the catheter remains in place, it might prevent a small area from healing or closing yet, and with time it might close.
Continuous bladder drainage to prevent the bladder from over-distending, ensuring proper healing. The catheter is kept in place for at least 2 weeks or until there is no more leakage of urine.
If urine continuously leaks onto the bed and very little or no urine is draining into the bag, chances are that the bladder repair has almost completely broken down, necessitating a repeat repair.
Inspect the bed to ensure it is dry.
Ensure there are no blood clots or debris blocking the catheter, ensuring free drainage of urine.
Plenty of fluids to prevent the formation of debris that could block the catheter.
Bladder training to release urine at increasing intervals to allow the bladder to regain its capacity and muscles to regain their tone.
If after 2 weeks all urine is draining into the catheter and the bed is dry, continue bladder training for 5 days.
Advertisements
Post-Operative Catheter Care
Catheter must drain freely at all times; if it becomes blocked, the operation may fail.
Catheter strapped to the mother’s thighs.
Patients must not lie on the catheter.
Catheter or tubing must not be twisted.
Drainage tubing must go into a basin or bucket at the side of the bed. Urine must be draining at all times.
Patient must drink fluids freely as soon as she has recovered from the anaesthetic.
Urine should be very pale, almost like water; if not, the patient should drink more.
If the catheter stops draining or the patient complains of a full bladder, the catheter must be removed immediately.
It must be irrigated to unblock it.
If irrigation fails, the catheter must be changed, usually by the doctor.
Apply Vaseline around the thighs.
Advice on Discharge
No coitus for at least 3-6 months.
Rest and take prescribed drugs.
Maintain vulva hygiene.
Come back for review.
Continue feeding well.
Next mode of delivery should be ELECTIVE C/S.
Complications of VVF
Recurrent fistula: If a fistula is closed and urine is allowed to accumulate in the bladder, the pressure may tear the repair and a new fistula may develop.
Sepsis: If a woman develops fever or sepsis, she must be given antibiotics.
Social problems: The social stigma attached to a woman with a VVF can be severe and prolonged. The constant wetness and odour of urine are offensive to the woman and those around her. She may be abandoned by her husband and family and may become an outcast.
Permanent conditions: Despite surgery, the woman may still leak urine. This can be because the tissues are scarred and cannot stretch, because the urethra is damaged, or because the bladder cannot empty.
If the woman has been leaking urine for months or years, the bladder may be too small or damaged to store the normal amount of urine.
Fertility: damage to the cervix and the uterus and if there is an infection in the uterus, the woman may not be able to conceive and carry a pregnancy to term.
Prevention of VVF
Community health education.
Emphasis on antenatal care.
Training traditional birth attendants: they should learn how to recognize prolonged labour and refer the woman for emergency care.
Timely referral of the woman: to a hospital for an emergency c/s if needed.
Government support: it should be provided to improve facilities and personnel.
RECTO-VAGINAL FISTULA
Recto-vaginal fistula is the connection between a woman’s rectum and vagina. The opening allows stool and gas to leak from the bowel into the vagina.
Causes
Complications during childbirth: During difficult delivery, the perineum can tear, or when performing an episiotomy to deliver the baby.
Inflammatory bowel disease (IBD): Conditions such as Crohn’s disease and ulcerative colitis cause inflammation in the digestive tract and can increase the risk of developing a fistula in rare cases.
Cancer or radiation to the pelvis: Cancer in the vagina, cervix, rectum, uterus, or anus can cause a recto-vaginal fistula. Radiation to treat these cancers can also create a fistula.
Surgery: Surgery on the vagina, rectum, perineum, or anus can cause an injury or infection that leads to an abnormal opening.
Infections due to HIV.
Sexual assault.
Signs and Symptoms
Passing stool or gas from the vagina.
Trouble controlling bowel movements.
Smelly discharge from the vagina.
Repeated vaginal infections.
Pain in the vagina or the area between the vagina and anus (perineum).
Dyspareunia (painful intercourse).
Risk Factors
Mother with prolonged labor.
Mother with obstructed labor.
Episiotomy during labor.
Women with infections such as an abscess or diverticulitis.
Women having cancer of the vagina, cervix, rectum, uterus, or anus, or radiation to treat these cancers.
Women who have undergone a hysterectomy or other surgeries to the pelvic area.
Diagnosis
History taking: The doctor will ask about symptoms and perform a physical examination.
Physical examination: With a gloved hand, the doctor will check the vagina, anus, and perineum. A speculum may be inserted into the vagina to open it up so the doctor can see the area more clearly. A proctoscope can help the doctor see into the anus and rectum.
Tests:
Anorectal or transvaginal ultrasound: A wand-like instrument is inserted into the anus and rectum, or into the vagina. An ultrasound uses sound waves to create a picture from inside the pelvis.
Methylene enema: A tampon is inserted into the vagina, then a blue dye is injected into the rectum. After 15 to 20 minutes, if the tampon turns blue, one has a fistula.
Barium enema: A contrast dye helps a doctor see the fistula on an X-ray.
CT scan: Uses powerful X-rays to make detailed pictures inside the pelvis.
MRI: Uses strong magnets and radio waves to make pictures from inside the pelvis. It can show a fistula or other problems with the organs, such as a tumor.
Management
Surgery: The main treatment for a fistula is surgery to close the abnormal opening. However, surgery can’t be performed if there is an infection or inflammation. The tissues around the fistula need to heal first.
The doctor might decide to wait for three to six months for an infection to heal and to see if the fistula closes on its own. Antibiotics are given to treat an infection or infliximab (Remicade) to bring down inflammation if the patient has Crohn’s disease.
While waiting for surgery:
Take antibiotics and analgesics.
Keep the area clean. Wash the vagina gently with warm water if you pass stool or a foul-smelling discharge. Use only gentle, unscented soap. Pat the area dry.
Use unscented wipes instead of toilet paper after visiting the bathroom.
Apply talcum powder or a moisture-barrier cream to prevent irritation in the vagina and rectum.
Wear loose, breathable clothing made from cotton or other natural fabrics.
If leaking stool, wear disposable underwear or an adult diaper to keep the feces away from the skin.
Advertisements
Surgery options:
Vaginal repair: Usually done when the fistula is in the lower half of the vagina or near the perineum.
Abdominal repair: Used by a general surgeon when repairing a recto-vaginal fistula arising in the vault after hysterectomy or radiotherapy.
During surgery, the doctor will take a piece of tissue from somewhere else in the body and make a flap or plug to close the opening.
The surgeon will also fix the anal sphincter muscles if they are damaged.
Some women will need a colostomy if a fistula is large and if continuing malignant tissue is suspected.
Complications
Recto-vaginal fistula can affect sex life.
Trouble controlling the passage of stool (faecal incontinence).
Repeated urinary tract or vaginal infections.
Inflammation of the vagina or perineum.
Abscess in the fistula.
Another fistula after the first one is treated.
Prevention
Health education to women on regular ANC services.
Early detection of associated risks and appropriate referral should be made.
Proper monitoring of labour using the partograph.
Skilled attendance at all births.
RELATED QUESTION
Objectives
Define obstetrical fistula.
Define fistula.
General causes of fistula.
General signs and symptoms of fistula.
Classifications of fistula.
Define VVF and RVF.
Investigations of VVF.
Management of VVF and RVF.
Prevention of VVF.
Complications of VVF.
Fistula
Obstetrical fistula: An opening or passage between organs of the genital tract and the urinary tract.
Fistula: An abnormal communication between two organs.
Classifications of Fistula
Vesico-vaginal fistula: Between bladder and vagina.
Recto-vaginal fistula: Between rectum and vagina.
Vesico-uterine fistula: Between bladder and uterus.
Urethro-cervical fistula: Between urethra and cervix.
Uretero-cervical fistula: Between ureter and cervix.
General Causes of Fistula
Obstetrical causes:
Poorly performed episiotomy.
Instrumental delivery (e.g., vacuum extractor and forceps delivery).
Operations such as caesarean sections.
Prolonged labor due to narrowing of pelvis.
Obstructed labor due to compressions from fetal head and symphysis pubis.
Gynecological causes:
Injuries caused during operations (e.g., hysterectomy and myomectomy).
Criminal abortion (e.g., use of sticks and other sharp objects).
Traumatic causes:
Direct trauma on the bladder or rectum due to road traffic accidents.
Falls on sharp pointed objects.
Radiation:
Common during treatment of cancer of the genital organs by radiotherapy rays.
Infections:
Infections like tuberculosis (e.g., tuberculosis of vagina may infiltrate normal tissues or cells).
Malignancy:
Abnormal growth of tissues in the vagina, cervix, bladder, and vagina.
General Signs and Symptoms of Fistula
History taking:
A mother may give a history of prolonged labor or obstructed labor leading to the rupture of the uterus.
Passage of urine:
Passage is kept open by chronic inflammations leading to continuous passage of urine in the vagina.
No bladder is felt on abdominal palpation since all urine escapes as soon as it reaches the bladder.
On vulva inspection:
Urine is seen dribbling from the vagina.
On speculum examination (e.g., Casco’s), the bladder mucosa may be seen prolapsed through fistula.
Complete wetness of the underwear due to continuous dribbling of urine.
Signs of urinary tract infections (e.g., syphilis, candida, and gonorrhea) may occur.
Other signs and symptoms:
Stool: Faeces will be seen in the vagina during recto-vaginal fistula.
Pain: The mother will feel pain during fistula.
Excretion of the vagina: Offensive smell which may be due to infections and itching of the vulva.
Vesico-Vaginal Fistula
Definition: An abnormal communication between the bladder and the vagina.
Investigations of VVF
Retrograde pyelography: Used to visualize the ureter.
Intravenous urography: Used to visualize the abnormalities of ureter and bladder.
Ultrasound scanning: Used to examine the interior of hollow organs.
Cystography: In complex fistula where lateral view of uterine cavity may be seen.
Management of VVF
Surgery:
Done after 3 months following delivery in case of old VVF.
If fistula is recognized within 24 hours, it may be repaired immediately if it is small.
Aims of management:
To relieve pain.
To relieve anxiety.
To promote quick recovery.
To prevent complications.
Management in the health center:
Receive the mother and relatives.
Offer a seat for them.
Take personal history.
Take gynecological history and call for an ambulance if it is a surgical condition.
Fill the referral form while reassuring the mother and accompanying her to the hospital, observing the vitals to rule out other bacterial infections.
Hand over the mother to the nurse/midwife on duty and give a report about the mother.
Hospital management:
The nurse on duty receives the mother and takes vital observations to rule out other abnormalities.
Admit the mother to the gynecological ward, have her sign a consent form, and call the doctor.
The nurse takes a brief history and continues taking vitals as the doctor comes.
The doctor carries out a genital examination and speculum examination.
Self-retaining catheter is passed, and she is kept on continuous bladder drainage as dripping urine prevents wetting of the linen.
The mother is put on appropriate antibiotics to treat any bacterial infection as prescribed by the doctor.
Encourage the mother to eat nutritious foods which are light and can easily be digested.
Most fistulas will close spontaneously within 6 weeks as long as there is continuous bladder drainage, good health, and control of infections.
In case of swelling or vaginal discharge due to sloughing of necrotic tissue, antiseptic vaginal douches are given (e.g., vaginal douche syringe to suck the fluid).
At the end of the puerperium, the patient is assessed by use of speculum.
Allow enough time for tissue healing and strengthening before scheduling surgery after 3 months.
Remove the catheter at 6 weeks if it is no longer needed; if urine continues to drip, prepare the mother for surgery.
Reassure the mother before taking her to the theater for operation.
Advertisements
Pre-Operative Management
The mother should have plenty of rest and sleep.
Encourage a nutritious diet with light, high-protein, and vitamin-rich foods to aid healing.
Maintain hygiene with vulva toileting three times a day.
Teach the patient about the condition, signs, and symptoms, and to wear a pad at all times, changing frequently to avoid infections.
Reassure the mother to relieve anxiety.
Administer drug therapy (antibiotics for bacterial infections and pain killers for pain relief).
Take vital observations to rule out other abnormalities.
Prepare the mother for operation by bathing, shaving, dressing in theater gown, and informing the theater nurse.
Accompany the mother to the theater and hand her over to the theater nurse with the necessary forms and details.
Prepare a post-operative bed for the patient’s return from the theater.
Post-Operative Management
The patient is received by qualified nurses from the theater with all necessary information.
Vital observations are taken to confirm the mother’s condition.
The mother is taken to the gynecological ward and placed on a post-operative bed.
Position the mother in a comfortable position (e.g., prone position) to relieve pressure on the bladder.
Special Nursing Care
Record vital observations (TPR/BP) every 15 minutes, 1 hour, 2 hours, and 4 hours for the first 24 hours.
Keep the mother on complete bladder drainage for 14 days.
Maintain a fluid balance chart, ensuring the correct rate and amount of ordered fluids.
Check the level, color, and care of the urine drainage bag and catheter.
Administer antibiotics (e.g., Ampicillin 1g every 6 hours and Gentamycin 160mg once daily) for prophylaxis.
Encourage plenty of oral fluids to prevent stenosis.
General Nursing Care
Hygiene:
Change linens daily and perform vulva swabbing twice a day.
Pay attention to perineal hygiene and provide bed baths.
Rest the bowel for 4 days to prevent pressure on the pelvic floor, using roughages and suppositories to ease defecation.
Bladder training:
From the 15th day post-operation, perform dye tests and release the catheter alternately if the test is negative:
15th day: 30 minutes
16th day: 1 hour
17th day: 2 hours
18th day: 3 hours
19th day: 4 hours
If all is well within 8 hours, the catheter is completely removed if the bed is dry.
Diet:
Encourage a nutritious diet to repair worn-out tissues.
Psychological care:
Counsel the mother about the operation and provide psychological support.
On discharge, advise the mother to avoid sex for 3-6 months and to seek antenatal care if she becomes pregnant again.
Ensure perineal hygiene.
Educate the mother about family planning, nutritious diet, and bowel and bladder care.
Prevention of Vesico-Vaginal Fistula
Early referral of a mother identified with obstructed labor to a hospital.
Encourage all primigravidae to deliver in properly supervised maternity units.
Identify complete perineal tears promptly.
Do not allow any mother to go into the second stage of labor with a full bladder.
Administer broad-spectrum antibiotics to prevent bacterial infections.
Complications of Vesico-Vaginal Fistula
Psychological trauma due to stress.
Divorce leading to breakage of marriage.
Necrosis of the skin around the thigh.
Keloids (tumors in scars).
Bladder Training Post-Operatively for Vesico-Vaginal Fistula
Bladder training is a critical part of post-operative care for patients who have undergone surgery for vesico-vaginal fistula. The goal is to gradually restore normal bladder function and control.
Bladder Training Schedule:
Starting from the 15th day after the operation, a structured bladder training program is implemented. This involves intermittent removal of the catheter to allow the bladder to fill and empty on its own, helping to strengthen the bladder muscles and improve control.
15th Day:
Remove the catheter for 30 minutes.
During this time, the patient should try to void naturally.
Reinsert the catheter after 30 minutes to drain any residual urine and prevent over-distension of the bladder.
16th Day:
Remove the catheter for 1 hour.
Encourage the patient to drink fluids and attempt to void naturally.
Reinsert the catheter after 1 hour.
17th Day:
Remove the catheter for 2 hours.
Continue to monitor the patient’s ability to void and ensure adequate fluid intake.
Reinsert the catheter after 2 hours.
18th Day:
Remove the catheter for 3 hours.
Observe the patient’s ability to control urination and the amount of urine voided.
Reinsert the catheter after 3 hours.
19th Day:
Remove the catheter for 4 hours.
This extended period allows the patient to test their bladder control for a longer duration.
Reinsert the catheter after 4 hours.
20th Day Onwards:
If the patient is able to control urination and the bed remains dry, the intervals without the catheter can be gradually increased.
Eventually, if there are no issues with leakage or retention, the catheter can be removed completely.
Patient Monitoring: Throughout the bladder training process, closely monitor the patient for signs of urinary retention, infection, or discomfort.
Fluid Intake: Encourage the patient to drink plenty of fluids to promote regular urination and prevent dehydration.
Hygiene: Maintain good perineal hygiene to prevent infections, especially during periods when the catheter is removed.
Reassurance: Provide reassurance and support to the patient, as they may experience anxiety or discomfort during the initial stages of bladder training.
Documentation: Keep detailed records of the patient’s fluid intake, urine output, and any symptoms or issues that arise during the training period.
Purpose of Bladder Training:
Strengthen Bladder Muscles: Gradually increasing the time the bladder holds urine helps strengthen the bladder muscles, improving control.
Prevent Incontinence: Regular intervals of voiding help in regaining control over urination and reduce the risk of incontinence.
Help in Recovery: Bladder training is a key part of the overall recovery process, ensuring the patient can return to normal bladder function as soon as possible.
Breast cancer occurs when cells in the breast grow and divide uncontrollably, forming a mass of tissue known as a tumour.
Breast cancer can invade nearby tissues and travel to other body parts, forming new tumours, a process called metastasis.
Clinical Manifestations
Early Signs of Breast Cancer
Asymptomatic: Sometimes, breast cancer shows no symptoms at all, especially in the early stages. This means you might not notice anything unusual.
Size and Shape Changes: A noticeable change in the size or shape of the breast.
Lump: A mass or lump that may be as small as a pea.
Persistent Lump or Thickening: A lump or thickening in or near the breast or underarm that persists through the menstrual cycle.
Skin Changes: Dimpling, wrinkling, scaliness, or inflammation of the skin on the breast or nipple.
Redness: Redness of the skin on the breast or nipple.
Distinct Area: An area distinctly different from other areas on either breast.
Nipple Discharge: Blood-stained or clear fluid discharge from the nipple.
Others;
Unilateral nipple discharge: When fluid, which could be clear, bloody, or another color, leaks from only one nipple.
Change in breast size: One breast might become noticeably larger or smaller than the other, or there could be a change in the overall size of the breast.
Nipple or skin retraction: The nipple may become inverted or pulled inward, or there may be dimpling or puckering of the skin on the breast.
Local lymphadenopathy: Swollen or enlarged lymph nodes in the armpit or collarbone area, indicating possible spread of cancer.
Skin changes-orange-like appearance (Peau d’orange): The skin on the breast might take on an orange peel-like appearance, due to changes caused by cancer cells blocking lymph vessels.
Nipple or skin ulceration: Sores or ulcers on the breast or nipple that do not heal or go away.
Breast pain: Persistent or unusual pain in the breast, although breast cancer does not cause pain in its early stages.
Symptoms of metastasis: If the cancer has spread to other parts of the body, symptoms may include bone pain, shortness of breath, jaundice, or neurological symptoms like headaches or seizures.
Risk Factors
Age: Being 55 or older increases the risk of breast cancer.
Sex: Women are much more likely to develop breast cancer than men.
Family History and Genetics: A family history of breast cancer increases the risk especially if close relatives like mother, sister, or daughter have had it. About 5% to 10% of breast cancers are due to inherited abnormal genes like the BRCA1 and BRCA2 genes.
Smoking: Tobacco use is linked to many cancers, including breast cancer.
Alcohol Use: Drinking alcohol increases the risk of certain types of breast cancer.
Obesity: Obesity increases the risk of breast cancer and recurrence.
Radiation Exposure: Prior radiation therapy, especially to the head, neck, or chest, increases risk.
Early onset menarche: Starting menstruation at a young age, usually before age 12.
Late menopause: Continuing menstruation later in life, usually after age 55.
Delayed first pregnancy (after 30 years of age): Not becoming pregnant for the first time until after the age of 30.
Null parity: Never having given birth to a child.
Family history (maternal or paternal) BRCA1 and BRCA2 genes: A family history of breast cancer,
History of breast biopsy: Previous biopsies or other breast procedures may indicate increased risk.
Use of Hormonal therapy for more than 4 years: Long-term use of hormone replacement therapy (HRT), which involves taking oestrogen and progesterone to relieve symptoms of menopause.
Stages of Breast Cancer
Staging helps describe the extent of cancer by determining the size, location, and spread of the tumour.
Stage 0: Non-invasive; cancer has not broken out of the breast ducts.
Stage I: Cancer cells have spread to nearby breast tissue.
Stage II: Tumour is smaller than 2 cm and has spread to underarm lymph nodes or is larger than 5 cm without spreading to underarm lymph nodes.
Stage III: Cancer has spread beyond the breast to nearby tissues and lymph nodes but not to distant organs (locally advanced breast cancer).
Stage IV: Cancer has spread to distant organs such as bones, liver, lungs, or brain (metastatic breast cancer).
Diagnosis/Investigations:
History Taking: About family history of breast cancer,medical history, and any other symptoms.
Self Breast Examination and Breast Examination: For any lumps, changes in size or shape, or other abnormalities.
Mammogram: Special X-ray of the breasts that can detect changes or abnormal growths, even before they can be felt. It’s a common screening tool for breast cancer.
Ultrasonography: Also known as ultrasound, Uses sound waves to create images of breast tissues. It helps in diagnosing lumps or other abnormalities found during a physical examination or mammogram.
Positron Emission Tomography (PET) Scan: This test uses special dyes to highlight areas of the body with abnormal metabolic activity, which can indicate the presence of cancer cells.
Magnetic Resonance Imaging (MRI): MRI uses magnets and radio waves to produce detailed images of breast structures. It’s especially useful for evaluating the extent of the disease in the breast.
TNM System: This is a staging system used to describe the extent of the cancer based on the size of the tumour (T), whether it has spread to nearby lymph nodes (N), and whether it has metastasized to other parts of the body (M).
Full Blood Count: This blood test helps assess the overall health and can indicate if there are any abnormalities or signs of infection or inflammation.
Renal and Hepatic Profile: Blood tests to assess the function of the kidneys and liver, as metastatic breast cancer can spread to these organs.
Chest X-Ray: This test may be done to check for any signs of metastasis to the lungs.
Biopsy (Preferably Fine Needle Aspiration): A biopsy is the definitive way to diagnose breast cancer by analyzing a sample of breast tissue under a microscope. Fine needle aspiration is a less invasive biopsy method often used for initial diagnosis.
Advertisements
Management of breast Cancer
Management depends on the tumour’s location and size, lab test results, and whether the cancer has spread.
Stage 0 (Cancer in situ):
Young Women: Conservative surgery only, such as lumpectomy.
Advanced Age: Mastectomy only.
Early Stage (Stage I and II):
Surgery: Modified radical mastectomy and lymphadenectomy for advanced age, and simple mastectomy or wide local lumpectomy for young age.
Hormonal Therapy: Tamoxifen 20 mg orally daily for 5 years, but may cause retinal damage. Blocks hormones that fuel certain cancers.
Chemotherapy:
Cyclophosphamide: 30 mg/kg IV single dose.
Fluorouracil: 300-1000 mg/m2 IV, given every 4 weeks based on patient response.
Paclitaxel: 6mg/ml in combination with Cisplatin 1mg/ml.
Late Cancer (Stage III and IV):
Hormonal Therapy: Same as for early stage, Tamoxifen 20mg orally daily for 5 years, but may cause retinal damage.
Chemotherapy: same as for early stage.
Radiation Therapy: Uses high-energy rays to kill cancer cells.
Immunotherapy: Helps the immune system fight cancer.
Targeted Drug Therapy: Uses drugs to target specific cancer cells.
Types of Breast Cancer Surgery
Lumpectomy (Partial Mastectomy): Removal of the tumour and some surrounding tissue, often followed by radiation therapy.
Mastectomy: Removal of the entire breast.
Axillary Lymph Node Dissection: Removal of multiple lymph nodes.
Modified Radical Mastectomy: Removal of the entire breast, underarm lymph nodes, and chest wall muscles if the cancer has spread. Reconstruction may be an option.
Mastectomy
Mastectomy is a planned surgical procedure involving the removal of the breast tissue.
There are different types of mastectomy:
Partial Mastectomy: Removal of lumps with surrounding normal tissue.
Simple Mastectomy: Removal of breast tissue with node biopsy.
Extended Simple Mastectomy: Removal of breast tissue, axillary tail, and nodes.
Total Mastectomy: Complete removal of the breast leaving the pectoralis muscle intact.
Radical Mastectomy: Removal of breast, skin, muscle, and nodes.
Modified Radical Mastectomy: Removal of breast, skin, muscles, and nodes with subsequent skin grafting.
Pre-operative Care
Admission: Patient admitted to a surgical ward.
History Taking: Record medical, surgical, and gynaecological history.
Observations: Vital signs monitoring, general examination. And the doctor is informed.
Investigations: Various tests including urinalysis, blood tests, and imaging.
Patient Education: Inform the patient about the surgery, its purpose, complications, and anaesthesia side effects.
Informed Consent: Obtain consent from the patient.
Preparation: IV line, blood booking, catheterization, pre-medications administration, and changing into hospital gown
Feeding: No feeds or drinks on the day of the operation
Rest and sleep: Ensure enough rest and sleep i.e. minizing noise, reducing bright light.
Morning at the day of the operations
IV line is put up
Booking for blood in the laboratory
Catheterisation of the patient
Administration of pre-medications
Helping the patient to change into hospital gown
Removal of all ornaments from the patient and keep them properly.
Continuous counselling to relieve anxiety
Preparation of patients medical document
Taking the patient to the theatre and handing her over to the theatre.
Post-operative Management
When the operation is finished, the information from the theatre will be sent to the ward and 2 nurses will go and collect the patient, reports are received from the surgeon, recovery room nurses and anaesthetists and then the patient is wheeled to the ward.
Patient Reception: Patient is received in a warm bed, flat position and turned to one side. As soon as she gains consciousness sit her in the bed leaning on the affected side to aid drainage.
Arm Care: Elevation and positioning as per surgeon’s orders.
Observation: Regular monitoring of temperature, pulse, respiration, blood pressure, bleeding, and edema.
Medical Treatment: Pain relief, antibiotics, vitamins, and supportives.
Pethidine 100mg 8 hourly for 3 doses on change to panadol to complete 5 days
Antibiotics: ampicillin or gentamicin as ordered
Supportives: vitamins like vitamin c, Iron, folic acid, diazepam
Wound Care: Inspection, dressing, drainage management, and stitch removal. Stitches are removed on the 8th – 10th day.
Wound and Drainage Care
Aseptic Care: Avoid unnecessary touching; inspect for tension or edema.
First Dressing: Done 48-72 hours post-surgery.
Drain Management: Monitor and remove drainage when discharge ceases.
Nursing Care After Mastectomy
Initial Care: Patient received in a warm bed in a flat position with head turned to one side.
Positioning: Once conscious, position the patient upright to aid drainage.
Vital Observations: Check vitals every 15 minutes in the first hour, then every 30 minutes for the next hour until stable.
Site Observation: Monitor for bleeding and edema.
IV and Blood Transfusion: Ensure correct flow rates.
Welcome and Explanation: Explain the procedure and provide comfort.
Analgesics and Antibiotics: Administer as prescribed (e.g., Pethidine, Ampicillin).
Supportive Care: Provide vitamins and minerals.
Hygiene: Provide bed baths and oral care until self-sufficient.
Diet: Encourage fluids and nutritious food.
Elimination: Promote regular bowel and bladder emptying.
Exercise: Begin chest, arm, and leg exercises to prevent deformity and contractures.
Psychotherapy: Reassure and counsel on using artificial breasts.
Advertisements
Advise on discharge
Radiotherapy: Start when the wound heals (6-8 weeks), lasting 2 months.
Follow-Up: Every 2 months for up to 2 years.
Chemotherapy: Continue as prescribed.
Regular Checkups: Monitor for metastasis.
Cancer Institute Visits: Attend radiotherapy.
Artificial Breast Use: Educate on proper use.
Complication
Necrosis: Death of suture line tissue.
Nerve Damage: Potential paralysis of the arm.
Contractures: Tightening of muscles and joints.
Sloughing: Shedding of dead tissue.
Infections: Risk of infection at the wound site.
Gaping: Opening of the wound.
Chronic Sinus: Persistent drainage site.
Oedema: Swelling of the arm.
Thrombosis: Blood clots in the axillary vein.
Cosmetic Deformity: Changes in appearance post-surgery
The Cervix
The cervix is a vital part of the female reproductive system, connecting the uterus to the vagina. It has two main types of cells:
Squamous cells: Flat, thin cells found in the outer layer of the cervix (ectocervix).
Glandular cells: Column-shaped cells that produce cervical mucus and are found in the cervical canal (endocervix).
Glandular cells from the cervical canal frequently migrate outside the canal and undergo changes to become squamous cells. This transformation process is known as squamous metaplasia, occurring in a region called the transformation zone.
Cervical Cancer
Cervical cancer is a malignant tumor found in the tissues of the cervix, occurring when abnormal cells in the cervix turn into cancer cells. These cancer cells can invade the surface cells (epithelium) and the underlying tissue (stroma) of the cervix, most commonly beginning in the transformation zone.
Epidemiology
Around 3,100 women are diagnosed with cervical cancer each year in the UK.
In Australia, about 780 women are diagnosed annually.
In Uganda, 2,464 women die from cervical cancer annually, with over 3,577 new cases diagnosed each year, making it a leading cause of death among women in the country.
Types of Cervical Cancer
Squamous cell carcinoma: Begins in the flat, thin cells lining the bottom of the cervix; accounts for 80-90% of cervical cancers.
Adenocarcinoma: Develops in the glandular cells lining the upper portion of the cervix; accounts for 10-20% of cervical cancers.
Mixed carcinomas: Involve both types of cells.
Causes of Cervical Cancer
The exact cause is unknown, but several risk factors have been identified:
Human papillomavirus (HPV): A major cause, with types 16 and 18 being the most oncogenic.
Smoking: Chemicals in cigarette smoke can damage cervical cells.
Immunosuppression: Conditions like HIV/AIDS weaken the immune system.
Oral contraceptives: Long-term use increases risk, which decreases after stopping the pill.
Other STIs: Infections like herpes and chlamydia can increase risk.
Circumcision: Women with uncircumcised partners are at higher risk.
Early sexual intercourse: Exposure to sperm can promote cell division in the transformation zone.
High parity: Multiple pregnancies can cause cervical trauma.
Repeated induced abortions: Can cause cervical trauma.
Exposure to chemicals: Occupational exposure to substances like tetrachloroethylene.
Symptoms of Cervical Cancer
Early symptoms may not be noticeable but can include:
Vaginal bleeding (between periods, after intercourse, post-menopausal)
Staging describes the extent of cancer spread. Federation for International Gynecology and Obstetrics (Figo) staging.
Stage 0: Carcinoma in situ (pre-invasive)
Stage I: Confined to the cervix
1a: Microscopic invasion
1b: Clinically visible lesion confined to the cervix
Stage II: Beyond the uterus but not to pelvic wall or lower third of vagina.
IIa: Limited to 2/3 of the vagina
IIb: Parametrial invasion(Cancer cells found outside the smooth muscles of the cervix.
Stage III: To pelvic wall, involves lower third of vagina, or causes hydronephrosis
IIIa: Invasion of lower 1/3 of the vagina.
IIIb: Invasion of pelvic sidewall +/- hydronephrosis
Stage IV: Invades bladder/rectum mucosa or distant metastasis.
Can spread by:
Direct spread to parametria on both sides, upper part of cervix, uterus, vaginal wall, bladder.
Lymphatic spread to lymph nodes in parametria, obturator nodes, external and internal iliac nodes, inguinal nodes, sacral nodes, hypogastric glands and rarely aortic and lumbar glands.
Blood spread to the lungs, liver, bone and intestines implantation.
Diagnosis of Cervical Cancer
1. History and Examination: Includes speculum and colposcopic examination.
Advertisements
2. Colposcopy-directed biopsy: Examination and tissue sample collection. Cervix-lesion may be in the form of an ulcer, Cauliflower growth.
3. Pap smear(papanicolau): Detects early-stage cancer or precancerous changes. The doctor scrapes a sample of cells from the cervix. For a Pap test, the lab checks the sample for cervical cancer cells or abnormal cells that could become cancer later if not treated.
4. Acetic Acid Test: This is of two types;
Unaided Visual Inspection (UVI): 3% acetic acid is painted on to the cervix. The abnormal area stains white and is biopsied to find out what type of lesion it is.
Aided Visual Inspection(AVI): cervix is painted with 3% acetic acid using a magnifying instrument to find the lesions present.
5. HPV testing: Identifies high-risk HPV strains.
6. Other tests: Full blood count, urea and electrolyte levels, liver function tests.
7. Biopsy: This is a surgical removal of tissue to look for cancer cells and usually done under local anesthesia. This may be done if cervical smear reveals evidence of cervical intraepithelial neoplasia. The tissue sample obtained is sent to the pathologist for histology and for confirmation.
Treatment and Prevention of Cervical Cancer
Pre-invasive: Pre invasive- lesions are destroyed using methods like liquid carbon dioxide, laser beam(leep)loop, electric excision procedure where the doctor uses an electric wire loop to slice off a thin, round piece of cervical tissue. Lesions destroyed using cryotherapy, laser beam, or LEEP.
Invasive carcinoma: Treatment is by wertheim’s hysterectomy. This involves total hysterectomy with removal of the upper 1/3 of the vagina as well as dissection of the lymph nodes including Para-aortic nodes plus salpingo-oophorectomy and this can be followed by radiotherapy. Treated with surgery (e.g., hysterectomy), chemotherapy, and radiotherapy.
Radiation therapy: This is the use of high-energy rays to kill cancer cells.
It’s an option for women with any stage of cervical cancer and may prefer radiation therapy to surgery.
It may also be used after surgery to destroy any cancer cells that remain in the area.
For women with cancer that extends beyond the cervix may need to combine radiation therapy and chemotherapy.
Surgical Management
Surgery is an option for women with Stage I or II cervical cancer. If you have a small tumor, the type of surgery may depend on whether you want to get pregnant and have children later on. Some women with very early cervical cancer may decide with their surgeon to have only the cervix, part of the vagina, and the lymph nodes in the pelvis removed (radical trachelectomy).
Prevention
Primary Prevention: Includes vaccination, health education, promoting safe sexual practices, reducing drug abuse, and regular screening.
Secondary Prevention: Early detection through regular screening and prompt treatment of precancerous lesions.
Primary Prevention
Since cervical cancer is often caused by a sexually transmitted infection (STI), steps can be taken to prevent its incidence. Primary prevention involves reducing or eliminating risk factors.
Vaccination: Encourage HPV vaccination to prevent cervical cancer.
Community Health Education
Promote awareness about the importance of early marriages and safe sexual practices.
Conduct educational programs to reduce drug abuse and promote the use of condoms.
Advocate for reducing the number of sexual partners.
Encourage behavior change and improved hygiene.
Men Involvement: Involve men in educational programs to promote understanding and support for prevention measures.
Income Generating Activities: Support income-generating activities to improve community well-being and reduce risk factors associated with poverty.
Secondary Prevention
Secondary prevention involves methods to detect cancer in its earliest stages so that treatment can begin as soon as possible.
Screening
Promote regular Pap smear tests to detect early cervical changes.
Ensure early referral to higher levels of care for further evaluation and treatment if needed.
Awareness and Training
Create awareness among health workers about the importance of early detection.
Train healthcare providers to perform screenings effectively.
Cost and Accessibility
Reduce the cost of screening to make it more accessible to the population.
Provide additional radiotherapy units in the country to extend services closer to the people.
Endometrial Cancer/Uterine Cancer
Endometrial cancer is a malignant tumor within the endometrium, resulting in abnormal cell growth that can invade or spread to other parts of the body.
Incidence/Epidemiology
It is the sixth most common cancer in women globally.
More common in developed countries, with a lifetime risk of 1.6% compared to 0.6% in developing countries.
Occurs in 12.9 out of 100,000 women annually in developed countries.
Most frequently appears during peri-menopause (ages 50-65).
75% of cases occur after menopause.
Women younger than 40 make up 5% of cases; 10-15% occur in women under 50.
Causes/Risk Factors
The exact cause is idiopathic, but it is associated with:
High blood pressure
Diabetes
Excessive or long-term estrogen exposure
Polycystic ovary syndrome (PCOS)
Functioning ovarian tumors
Anovulation
Infertility
Family history or genetic factors
Obesity
Late menopause
Early menarche
Age above 55 years
Excessive use of tamoxifen
Nulliparity (never having had children)
Advertisements
Classifications of Endometrial Cancer
Type 1 Endometrial Carcinoma: Estrogen-related, occurs in younger, obese, premenopausal women, usually low-grade and endometrioid.
Type 2 Endometrial Carcinoma: High-grade, usually serous or clear cell, affects older women.
Type 3 Endometrial Carcinoma: Hereditary or genetic types, some related to Lynch II syndrome.
Clinical Presentation
Vaginal bleeding or spotting in postmenopausal women (90% of cases).
Abnormal menstrual cycles or heavy, frequent bleeding in premenopausal women.
Thin white or clear vaginal discharge in postmenopausal women.
Enlarged uterus on physical examination.
Lower abdominal pain, pelvic cramping, painful sexual intercourse, painful or difficult urination (with metastasis).
Diagnosis
History and physical examination.
Dilation and curettage.
Transvaginal ultrasound to examine endometrial thickness in postmenopausal bleeding.
Endometrial biopsy.
CT scan.
Differential Diagnosis
Senile endometritis/vaginitis.
Dysfunctional uterine bleeding.
Submucous myoma/endometrial polyps.
Cervical cancer.
Uterine sarcoma.
Primary carcinoma of the fallopian tube.
Management
Surgery
Stage I: Total Abdominal Hysterectomy and Bilateral Salpingo-Oophorectomy (TAH-BSO).
Stage II: Radical Hysterectomy.
Stage III: Radical surgery with maximal debulking followed by radiotherapy.
Stage IV: Radical radiotherapy, with or without hormonal therapy and/or chemotherapy.
Radiotherapy
Most patients with early-stage disease receive a combination of surgery and radiotherapy based on histopathological findings.
Surgery alone is limited to patients with endometrioid type carcinoma confined to less than 50% of the myometrial thickness.
Hormonal Therapy
Progestogens are the most commonly used form of hormonal therapy in endometrial cancer.
Chemotherapy
Chemotherapy is uncommon but should be considered in fit patients with systemic disease. Commonly used medications include:
Doxorubicin (Anthracycline) and Cisplatin
Carboplatin (Platinum Medicines): Use is limited by the patient’s advanced age and poor performance status.
Typical regimen: Cisplatin 50 mg/m² IV, Adriamycin 45 mg/m² IV on Day 1, followed by Paclitaxel 160 mg/m², repeated every 21 days.
Alternative regimen: Carboplatin and Paclitaxel as for ovarian cancer.
Ovarian Cancer
Ovarian cancer is a malignant growth within the ovarian tissue.
Etiology and Pathogenesis
There is a link between ovulation and epithelial ovarian cancer. Combined hormonal contraception reduces the risk by approximately 50%. Risk factors include having a first-degree relative with ovarian cancer.
Risk Factors
Postmenopausal women
Family history of ovarian cancer (mother, sister)
Abnormal ovarian development (e.g., Turner’s syndrome)
Nulliparity
BRCA1 and BRCA2 gene mutations
Smoking and alcoholism
Ovulatory stimulant drugs
High-fat diet
Fertility drugs
Hormonal replacement therapy
Increased number of ovulatory cycles (early menarche, late menopause)
Stages of Ovarian Cancer
Stage I: Confined to the ovaries
1a: One ovary involved
1b: Both ovaries involved
1c: Positive cytology, ascites, or capsule breach
Stage II: Confined to the pelvis
Stage III: Confined to the peritoneal cavity
3a: Micronodular disease outside the pelvis
3b: Macroscopic tumor deposits <2 cm
3c: Tumor >2 cm or retroperitoneal node involvement
Stage IV: Distant metastases
Clinical Manifestations
Ovarian cancer often lacks early symptoms. Advanced disease may present with:
Home > Gynaecology & Reproductive Health > Fibroids (Fibromyomas)
Fibroids (Fibromyomas)
Uterine Fibroids are benign (non-cancerous) tumors that originate from the smooth muscle layer (myometrium) of the uterus.
Other Medical Names: Uterine leiomyoma, myoma, fibromyoma, and fibroleiomyoma.
Demographics: They typically occur after the age of 30 years and are most commonly seen in nulliparous women (women who have never had children).
Characteristics: They are composed of dense muscle and fibrous tissue. They can be single or multiple, and range in size from a tiny microscopic pinhead to an enormous mass that distorts the entire abdomen. They are far more likely to arise in the body of the uterus than in the cervix.
Risk Factors for Uterine Fibroids
While the exact primary cause is still being researched, several established clinical risk factors drastically increase a woman's likelihood of developing uterine fibroids:
Age: Fibroids are most prevalent and aggressively grow in women between the ages of 30 to 40 years.
Parity (Number of Pregnancies): Women who are nulliparous (have never given birth) or have very low parity are at a significantly higher risk. Pregnancy seems to have a protective effect.
Race / Ethnicity: Uterine fibroids are disproportionately more prevalent, tend to appear at a younger age, and grow larger in individuals of African descent (Black women) compared to those of Caucasian (White) ethnicity.
Family History: Genetics play a strong role. If a woman has close first-degree relatives (such as a mother or sister) with a history of fibroids, her personal risk is highly increased.
Hyper-estrogenemia: Elevated levels of the female hormone estrogen directly promote the rapid growth of fibroids. Fibroids are highly estrogen-dependent.
Obesity: Being overweight or obese is strongly associated with a higher risk. (Pathophysiology note: Adipose/fat tissue converts androgens into estrogen, leading to higher overall circulating estrogen levels).
Early Onset of Menarche: Starting menstruation at a very young age (early exposure to cyclic hormones) is linked to an increased likelihood of fibroid development later in life.
Low Level of Vitamin D: Recent clinical studies suggest that a deficiency or insufficient levels of Vitamin D might be associated with a higher risk of fibroid growth.
Drugs (Estrogen Replacement Therapy): Long-term use of estrogen replacement therapy, particularly when used without progesterone to balance it, acts as a direct catalyst for fibroid growth.
Classes, Types, and Locations of Uterine Fibroids
Fibroids are classified based on their specific growth patterns and exactly where they are situated within or around the uterus.
1. Types of Uterine Fibroids
The "type" refers to the specific category based on its growth characteristic relative to the uterine layers:
Submucosal Fibroids: These grow directly into the uterine cavity, situated just beneath the inner lining (endometrium). Because they disrupt the cavity, they are the main culprits for heavy menstrual bleeding (menorrhagia) and infertility.
Intramural (Interstitial) Fibroids: The most common type. They grow centrally within the thick muscular wall of the uterus (myometrium). As they expand, they distort the overall shape of the uterus, leading to severe pain and pressure.
Subserosal Fibroids: These grow on the outside surface of the uterus, just under the serosa layer. They project outward into the pelvic cavity, often growing quite large and pressing on nearby organs like the bladder or rectum.
Pedunculated Fibroids: These are attached to the uterus by a narrow stalk or pedicle that contains their blood supply. They can be either pedunculated subserosal (hanging outside) or pedunculated submucous (hanging inside the cavity).
Cervical Fibroids: Located specifically on the cervix (the lower neck of the uterus). These are relatively rare but can cause severe pain, discomfort, and major complications (like obstructed labour) during childbirth.
Fibroid of the Broad Ligament: Develops outward into the broad ligament (the supportive structure holding the uterus in place). They are uncommon and require very specific surgical management to avoid damaging the ureters.
Visual classification of fibroids based on their location within the uterine layers.
Understanding the Difference: Types vs. Location
Many students confuse "Types" with "Location." Here is the clinical distinction:
Concept
Definition
Examples
Types of Fibroids
Refers to the different categories or classifications based on their specific growth patterns and characteristics.
Refers to the specific physical site within or around the pelvic organs where the fibroid has situated itself. Location dictates which organs it will press against.
Subperitoneal (under peritoneal surface), Bulging into the endometrial cavity, Centrally within the myometrium, At the outer border, On the cervix.
Statistical Frequencies and Specific Positions
Intramural / Interstitial: Accounts for the vast majority at 75%. Initially intramural, they may later be pushed outward or inward, but about 70% persist in this central position.
Subserous / Subperitoneal: Accounts for 15%. They are pushed outward towards the peritoneal cavity and are either partially or completely covered by the peritoneum.
Submucous: Accounts for only 5%. Despite being the least common, it produces the maximum number of symptoms.
Cervical Positions: Depending on exactly where they grow on the cervix, they are classified as: Anterior, Posterior, Lateral, or Central cervical fibroids.
Pathology and Microscopic Structure
Understanding the exact cellular structure of a fibroid helps explain its surgical and clinical behavior:
Gross Pathology: Fibroids are firm, spherical, or irregularly lobulated. They possess a false capsule (pseudocapsule) made of areolar tissue and compressed normal myometrium. Because the capsule is false, the fibroid can be easily "enucleated" (shelled out) from the surrounding myometrium during surgery.
Microscopic Structure: Consists of smooth muscle cells that are spindle-shaped and uniform. They are arranged in a distinct whorled pattern interlaced with varying amounts of fibrous connective tissue.
Vascularity: Arteries inside the fibroid are less dense than the surrounding myometrium and lack a regular distribution pattern. Usually, only 1 to 2 major vessels are found at the base or pedicle supplying the entire mass.
Changes in Surrounding Pelvic Organs
The Uterus: The shape becomes grossly distorted. Myohyperplasia (overgrowth of muscle cells) is a constant finding. There is massive dilatation and congestion of the myometrial and endometrial venous plexuses. The uterine cavity itself may become elongated and distorted.
The Ovaries: Often become enlarged, highly congested, and studded with multiple cysts. Anovulation is commonly associated.
The Ureters: Broad ligament fibroids cause severe displacement of normal ureter anatomy, increasing the risk of surgical injury.
Associated Conditions: There is a highly increased clinical association with pelvic endometriosis, adenomyosis, and endometrial carcinoma.
Causes of Uterine Fibroids
The exact trigger that causes a single smooth muscle cell to mutate and multiply into a fibroid is not fully understood, but clinical research points to two major driving forces:
Hormones (Estrogen and Progesterone): These two hormones, which naturally regulate the menstrual cycle and thicken the endometrium, directly stimulate the growth of fibroids. Fibroids possess more estrogen and progesterone receptors than normal uterine muscle cells. Consequently, fibroids grow rapidly during the reproductive years (especially during pregnancy when hormone levels are massive) and naturally shrink (atrophy) during menopause when hormone production ceases.
Genetics: Genetic alterations are frequently found in fibroid cells. A strong familial link exists; women with a mother or sister who had fibroids are genetically predisposed to developing them.
Other Contributing Factors: Diet (high in red meat, low in green vegetables), obesity, and race (African descent) act as strong secondary catalysts.
Degenerative Changes in Uterine Fibroids
Because fibroids grow so rapidly, they often outgrow their own blood supply. When this happens, the tissue undergoes "degenerative changes" (alterations in tissue structure):
Hyaline Degeneration: The most common type. The firm muscle fibers are gradually replaced by a soft, homogenous, structureless hyaline material. The most common type, occurring in 65% of cases affecting all sizes (except tiny ones). The tumor loses its firm feel and becomes soft and elastic. Naked-eye examination of a cut surface shows irregular, glassy, homogenous areas with a complete loss of the normal "whorl-like" appearance.
Cystic Change: This usually follows hyaline degeneration. The soft hyaline tissue liquefies, leaving fluid-filled cavities that make the fibroid look exactly like an ovarian cyst.
Red (Carneous) Degeneration: Occurs mainly in the second half of pregnancy and puerperium. Microscopically: shows evidence of severe necrosis. Odor & Color: It emits a distinct "fishy" odor due to fatty acids, and the raw-beef color is due to the presence of haemolysed red blood cells and hemoglobin trapped in the cystic spaces.
Fatty Change: The muscle fibers of the fibroid are slowly replaced by fat (adipose) tissue.
Atrophy: Following menopause, due to the drastic drop in estrogen and progesterone, the fibroid simply wastes away and shrinks in size.
Calcification: Calcium salts are heavily deposited into the fibroid tissue, causing it to harden.
Eggshell Fibroid: Calcium deposits form a hard shell strictly on the outside, leaving the inside soft.
Womb Stone: The entire fibroid is completely infiltrated with calcium salts, becoming solid and hard like an actual stone.
Septic / Infective Degeneration: Infection gains access to the tumor through thinned, sloughed surface epithelium of a submucous fibroid. This usually happens immediately following delivery or an abortion.
Sarcomatous (Malignant) Change: The rarest but deadliest change. The benign fibroid undergoes malignant transformation into a leiomyosarcoma. This must be heavily suspected if a fibroid suddenly grows rapidly, especially in post-menopausal women.
🧠 Memory Aid: Degenerative Changes of Fibroids
Remember the letters: H - C - C - R - F - S - S
H = Hyaline (Most common, 65%) C = Cystic (Liquefaction) C = Calcific (Womb stone in menopause) R = Red / Carneous (During pregnancy) F = Fatty (Post-menopause) S = Septic / Infective (Post-delivery/abortion) S = Sarcomatous (Malignant transformation)
Parasitic Fibroid: Occurs when a pedunculated fibroid twists on its pedicle (torsion), completely cutting off its original blood supply. To survive, it attaches itself to nearby organs (like the omentum or bowel) and establishes a brand new "parasitic" blood supply from them.
⚠️ Attention: Red Degeneration (Obstetric Emergency)
Red Degeneration is an acute complication that almost exclusively occurs during pregnancy. The fibroid grows so fast that its blood supply fails, leading to massive tissue necrosis (cell death) and hemorrhage inside the fibroid. It becomes soft, reddish, and looks like "beefy" raw meat. It causes the pregnant mother sudden, severe, localized abdominal pain, localized tenderness, and low-grade fever.
Clinical Presentation (Signs and Symptoms)
Many women with fibroids are asymptomatic. However, depending on the size, number, and location, they can present with severe symptoms:
Menstrual Abnormalities:
Painful & Prolonged Menstruation: Heavy menstrual bleeding (menorrhagia) and extremely painful periods (dysmenorrhea).
Postmenopausal Bleeding: Vaginal bleeding occurring after menopause is highly abnormal and requires immediate investigation.
Bulk and Pressure Symptoms:
Urinary Issues: Anterior fibroids pressing against the bladder cause increased frequency of urination or difficulty emptying the bladder (retention).
Constipation: Posterior fibroids pressing on the rectum block the passage of stool.
Pelvic Pressure/Fullness: A constant feeling of heaviness or pressure in the lower abdomen.
Abdominal Enlargement: Large or multiple fibroids can cause the abdomen to distend, mimicking the appearance of a pregnancy.
Vascular Pressure: Extreme pelvic vein pressure can cause the development of severe hemorrhoids and varicose veins in the legs.
Pain and Discomfort:
Lower Back and Leg Pain: Caused by large fibroids pressing directly on pelvic nerves.
Dyspareunia: Deep pain or discomfort during sexual intercourse.
Acute Pain: Sudden, severe pain indicates a complication such as acute red degeneration or torsion (twisting) of a pedunculated fibroid.
Reproductive Issues:
Infertility: Submucosal fibroids distort the uterine cavity, physically blocking fallopian tubes or preventing the proper implantation of a fertilized egg.
Specific Symptom Triggers
Dysmenorrhea Types: Can present as Congestive (due to massive associated pelvic venous congestion or endometriosis) or Spasmodic (associated with the violent uterine contractions attempting to expel a submucous polyp from the cavity).
Extreme Urinary Retention: Rarely, a specific posterior fundal tumor can cause an extreme retroflexion of the entire uterus, violently distorting the bladder base and causing acute urinary retention.
Bowel Obstruction: A parasitic fibroid that has detached and attached to the bowel can cause direct mechanical bowel obstruction.
Cervical Symptoms: Tumors strictly on the cervix heavily provoke foul vaginal discharge, severe bleeding, and dyspareunia.
Diagnosis and Investigations
Diagnosing uterine fibroids involves a combination of thorough clinical examination and advanced imaging.
1. Clinical Examination
History Taking: Comprehensive assessment of menstrual patterns, volume of blood loss, reproductive history, and pain levels.
Physical Examination: Checking the patient's general health, specifically looking for signs of chronic anemia (extreme pallor of the conjunctiva and palms) resulting from prolonged menorrhagia.
Abdominal Examination: Palpating the abdomen to detect large, firm, irregular pelvi-abdominal swellings rising out of the pelvis.
Pelvic & Bimanual Examination: A two-handed examination to feel the size, shape, nodularity, and mobility of the uterus. A speculum examination may reveal fibroid polyps protruding directly through the cervical os.
2. Medical Investigations (Labs & Imaging)
Pregnancy Test: A mandatory first step to rule out pregnancy as the primary cause of an enlarged uterus or amenorrhea.
Full Blood Count (FBC) & Iron Studies: To confirm and quantify the severity of anemia caused by heavy bleeding.
Pelvic Ultrasound (U/S): The standard, non-invasive imaging test to clearly visualize the uterus and detect the size and number of fibroids.
Transvaginal Ultrasound (TVUSS): Inserting a small probe into the vagina provides a much clearer, high-resolution view of the pelvic organs, which is especially useful in obese patients.
Saline Hysterosonography: Injecting sterile saline into the uterus during an ultrasound to sharply outline the cavity and identify hidden submucous fibroids.
Hysterosalpingogram (HSG): An X-ray procedure using contrast dye to visualize the exact shape of the uterine cavity and ensure the fallopian tubes are open (crucial for infertility workups).
Hysteroscopy: Passing a thin, lighted camera (hysteroscope) through the vagina and cervix directly into the uterus to visualize and potentially remove submucosal fibroids.
MRI (Magnetic Resonance Imaging): The most highly accurate tool for mapping out the exact size, location, and vascularity of every single fibroid prior to complex surgeries.
Differential Diagnosis (DDx)
Fibroids are usually easily diagnosed, but the midwife/clinician must clinically exclude other conditions that cause similar presentations:
Exclude Pregnancy: Always the absolute first step for an enlarged uterus.
Exclude Other Pelvic Masses: Ovarian Carcinoma, Tubo-ovarian abscesses, Endometriosis, or Adnexa/omentum/bowel that has adhered to the uterus.
Exclude Other Causes of Uterine Enlargement: Adenomyosis, Generalized Myometrial hypertrophy, Congenital anomalies, or Endometrial Carcinoma.
Exclude Other Causes of Abnormal Bleeding: Endometrial hyperplasia, Endometrial or tubal Carcinoma, Uterine sarcoma, Polyps, and Dysfunctional Uterine Bleeding (DUB).
⚠️ Attention: Rule Out Malignancy
An endometrial biopsy or Dilation & Curettage (D&C) is strictly essential in the evaluation of any abnormal uterine bleeding to definitively exclude Endometrial Carcinoma before assuming the bleeding is solely from a fibroid.
Management of Uterine Fibroids
Most fibroids are totally asymptomatic and require expectant management (watchful waiting), especially since they shrink naturally after menopause. When treatment is required, the choice depends on: Age, Parity, Size/Location of the fibroids, Desire to preserve the uterus, and the Desire for future pregnancies.
1. Emergency Treatment
Blood Transfusion: Immediately given to correct life-threatening severe anemia.
Emergency Surgery (Laparotomy): Indicated immediately for an infected/necrotic myoma, acute torsion (twisting) of a pedicle, or severe intestinal obstruction caused by massive fibroid pressure.
2. Medical Management (Pharmacology)
Medical management does not cure fibroids permanently but controls symptoms and temporarily shrinks them prior to surgery.
NSAIDs: Nonsteroidal anti-inflammatory drugs (like Ibuprofen) to manage severe pelvic pain and cramping.
Antifibrinolytic Agents: Tranexamic acid specifically helps to drastically reduce heavy menstrual bleeding (menorrhagia) by preventing blood clots from breaking down too quickly.
Hormonal Control: Low-dose birth control pills or a Levonorgestrel Intrauterine Device (Mirena coil) effectively limit menstrual blood flow and thin the uterine lining with minimal side effects.
Haematinics: Aggressive supplementation with Ferrous Sulphate and Folic Acid to rebuild hemoglobin levels in anemic patients.
GnRH Agonists (Lupron, Synarel): These drugs put the body into a temporary medical menopause by shutting down estrogen and progesterone production from the ovaries. This stops menstruation and significantly shrinks the fibroids.
Mifepristone: (25-50mg twice weekly) acts as a progesterone receptor inhibitor, effectively reducing fibroid size and stopping bleeding.
Danazol: A synthetic androgen that interrupts ovulation and shrinks fibroid tissue.
3. Surgical Management
Specific Surgical Criteria
Open Myomectomy (Laparotomy): The route of absolute choice for large subserous or intramural fibroids measuring greater than 7 cm, multiple fibroids greater than 5 cm, or when direct entry into the uterine cavity is expected.
Hysteroscopic Myomectomy: The route of choice strictly for removing submucous (SM) fibroids measuring greater than 2 cm.
Laparoscopic Myomectomy: Mostly done for the subserosal type, removing the mass entirely through a small abdominal keyhole incision.
Advanced Non-Invasive Procedures
MRGFUS (Magnetic Resonance Guided Focused Ultrasound Surgery): A non-invasive procedure where focused ultrasound waves are converted into intense heat inside the pathology to destroy it, entirely under MRI guidance.
Selection Criteria: Fibroid must be 4 to 10 cm, the woman must have completed her family, and she should be perimenopausal.
Myomectomy: The surgical removal of the fibroids while leaving the healthy uterus intact. Indications: Young women who strongly desire future pregnancies, have a few isolated fibroids, but suffer from heavy bleeding or infertility.
Hysterectomy: The complete surgical removal of the entire uterus. Indications: Women who have completed their families, are approaching menopause, have massive/numerous fibroids that destroy the uterine structure, or if there is any suspicion of malignant (cancerous) changes.
Hysteroscopic Resection: Passing a wire loop through the cervix to shave off and remove submucosal fibroids from inside the cavity without cutting the abdomen.
Endometrial Ablation: Surgically destroying the entire inner lining of the uterus using heat or freezing to permanently stop heavy bleeding (only for women who do not want more children).
Uterine Artery Embolization (UAE): A radiologist injects tiny polyvinyl particles into the femoral artery, guiding them to block the specific blood vessels feeding the myoma, causing it to starve and shrink.
Radiofrequency Ablation: Inserting a needle-like device directly into the fibroid and heating the tissue with radiofrequency energy to destroy it.
Pre and Post-Operative Care for Fibroid Surgery
Whether a patient is undergoing a Myomectomy or a Hysterectomy, meticulous nursing care is required to prevent life-threatening surgical complications.
Pre-Operative Management
Admission & History: Obtain personal, medical, social, and detailed gynecological history. Conduct a full physical head-to-toe examination specifically ruling out severe anemia, dehydration, and jaundice. Ensure a general assessment by the gynecologist is documented.
Informed Consent: The surgeon must explain the exact reasons for the operation, the benefits, the risks (including the risk of converting a myomectomy to a full hysterectomy if uncontrollable bleeding occurs), and expected results. Involve the partner where culturally or legally appropriate, and secure written consent.
Investigations: Ensure all preoperative lab work is back on the file: Urinalysis, Hemoglobin (HB) level, Blood Grouping & Cross-matching (ensure at least 2 units of blood are ready), Abdominal ultrasound, Urea and Electrolytes, INR/PT (clotting profile), and an ECG/ECHO if the patient is older or hypertensive.
Patient Education & Counseling: Educate the patient about what to expect when waking up (pain, catheters, IV lines). Provide strong reassurance to relieve surgical anxiety.
Physical Preparation: Ensure the patient fasts from food and drinks (NPO) for at least 8 hours prior. Shave and prep the abdominal/pubic area. Arrange for a wide-bore IV line insertion. Insert a urethral Foley catheter to keep the bladder completely empty and safe from surgical injury. Administer prescribed pre-medications.
Theatre Transfer: Help the patient change into a clean theatre gown, remove jewelry and dentures, and wheel her to the operating theatre while providing continuous emotional support.
Post-Operative Management
Reception & Positioning: Receive the patient from the recovery room into a pre-warmed bed. Keep her lying flat (supine for abdominal surgery) with the head turned to one side to prevent aspiration if she vomits.
Intensive Observation: Take vital signs continuously (every 15 minutes for the first hour, then every 30 minutes until fully stable). Closely monitor BP and pulse for early signs of internal hemorrhage or hypovolemic shock. Check the surgical dressing for active bleeding. Monitor the IV infusion rate and continuous blood transfusions.
Upon Full Consciousness: Gently welcome the patient, orient her to the ward, and explain that the surgery was successful. Assist with face sponging, provide mouthwash to relieve dry mouth, and change her into a fresh gown.
Medical Treatment & Pain Relief: Administer strong analgesics precisely as prescribed (e.g., IM Pethidine 100mg every 8 hours for the first 24 hours, then step down to oral Paracetamol/NSAIDs). Administer broad-spectrum IV antibiotics (e.g., Ampicillin/Gentamicin) to prevent pelvic sepsis. Continue Haematinics and Vitamin C to aid rapid wound healing.
Wound Care: Monitor the abdominal wound closely. If minor strike-through bleeding occurs, do not remove the dressing; simply reinforce it with a fresh bandage on top and notify the surgeon.
Nursing & Rehabilitative Care: Maintain strict hygiene (bed baths, catheter care). Once bowel sounds return and the doctor permits, start sips of water and progress to a soft diet. Encourage deep chest breathing and early leg exercises while in bed to prevent Deep Vein Thrombosis (DVT) and chest infections. Assist with early ambulation.
Specific Vaginal Surgery Management (If applicable)
If a vaginal pack was inserted to control hemorrhage, inspect it frequently for soakage.
Once the pack is removed (usually after 24 hours), apply a sterile vulval pad. Swab and clean the vulva at least every 8 hours using aseptic technique to prevent ascending infections.
🧠 Discharge Advice (Crucial for Myomectomy)
For Myomectomy Patients: The uterine wall has been cut and scarred. Advise the mother to strictly avoid conception for at least 2 years to allow the uterine scar to achieve maximum strength. When she does conceive, she must deliver via Elective Cesarean Section to prevent a catastrophic uterine rupture during labour.
For Hysterectomy Patients: Provide deep psychological counseling. Assure her she will no longer have periods and cannot conceive, but her sexual function will remain intact once healed. Recommend abstaining from sexual intercourse for 6 weeks.
Complications of Uterine Fibroids
General Gynecological Complications
Severe Menorrhagia: Leading to chronic, debilitating iron-deficiency anemia.
Infertility: Due to blocked tubes or a distorted endometrial cavity preventing embryo implantation.
Torsion: A pedunculated fibroid twisting on its stalk, causing acute ischemic pain and gangrene.
Urinary Tract Diseases: Chronic retention of urine leading to repeated severe urinary tract infections (UTIs) and hydronephrosis (kidney swelling) due to ureter compression.
Complications During Pregnancy and Labour
If a woman with significant fibroids conceives, the pregnancy is automatically classified as High Risk due to the following massive threats:
Antepartum Hemorrhage (APH): The presence of fibroids heavily increases the risk of Placenta Previa and Placental Abruption.
Abortion/Miscarriage: The distorted cavity lacks enough healthy blood supply to sustain the early placenta.
Fetal Growth Restriction (FGR): The fibroids steal the blood supply away from the growing baby, leading to a small, undernourished fetus.
Malpresentation: Large fibroids block the baby from turning properly, leading to Breech or Transverse lies.
Labor Dystocia & Obstruction: A cervical or lower segment fibroid acts as a literal physical roadblock, causing completely Obstructed Labour.
Premature Labor: The uterus becomes overstretched too early by the combined bulk of the baby and the fibroids.
Uterine Inertia & PPH: The fibroid-riddled myometrium loses its ability to contract effectively. This leads to weak labour (inertia) and massive Postpartum Hemorrhage (PPH) because the uterus cannot clamp down on the bleeding blood vessels.
Subinvolution: During the puerperium, the fibroid prevents the uterus from shrinking back to normal size, causing prolonged, heavy lochia.
Clinical Nursing Care Plan: Uterine Fibroids
Clinical Scenario: Mrs. A.O., a 44-year-old teacher, is admitted for a scheduled total abdominal hysterectomy due to symptomatic fibroids. Complaints: Menorrhagia (bleeding 8-10 days, soaking pad/super tampon hourly), pelvic pain/pressure (5/10), and severe fatigue. Pre-op Hb: 9.8 g/dL. She feels "drained" and is highly anxious about surgery and loss of fertility.
Diagnosis:Chronic Pain related to pressure from enlarged fibroids on pelvic organs/nerves.
- Report pain decrease to manageable level (< 3/10).
- Demonstrate two non-pharmacological relief techniques.
- Rest comfortably.
Interventions:
1. Conduct comprehensive pain assessment.
2. Administer prescribed NSAIDs on a scheduled basis.
3. Teach non-pharmacological comfort (heating pad, guided imagery).
4. Position in semi-Fowler's or side-lying with pillows.
Rationale: Scheduled dosing provides consistent analgesia. Positioning alleviates direct fibroid pressure on structures.
Goals Met. Patient reports pain is 2/10 after scheduled ibuprofen and heating pad. Resting comfortably in semi-Fowler's.
Subjective: "Drained all the time, no energy." Reports menorrhagia. Objective: Pale conjunctiva, Hb 9.8 g/dL, lethargic, mild tachycardia on exertion.
Diagnosis:Excessive Fatigue burden related to chronic blood loss and anemia.
- Identify relationship between heavy bleeding, anemia, and fatigue.
- Participate in energy conservation.
- Verbalize anemia management plan.
Interventions:
1. Cluster nursing activities; schedule rest periods.
2. Administer iron supplements with Vitamin C.
3. Educate on fatigue causes linking to blood loss.
4. Provide an iron-rich diet (lean meat, spinach).
Rationale: Vitamin C heavily enhances iron absorption. Energy conservation prevents exhaustion while maintaining dignity.
Goals Met. Patient explains, "My heavy periods made my blood count low, which is why I'm tired." Taking iron actively.
Subjective: "Worried about surgery. Feels strange not having a uterus." Objective: Restless, anxious expression, increased HR/BP when discussing surgery.
Diagnosis:Excessive Anxiety related to impending major surgery, body image changes, and loss of fertility.
- Verbalize specific fears.
- Report noticeable decrease in anxiety.
- Demonstrate effective coping mechanisms (deep breathing).
Interventions:
1. Establish a trusting relationship to express feelings.
2. Provide clear, factual pre/post-op routine info.
3. Teach relaxation (mindfulness, calming music).
4. Acknowledge and validate grief over end of fertility.
Rationale: Validation normalizes emotional response. Factual knowledge dispels myths and reduces fear of the unknown.
Goals Met. Patient reports feeling "less on edge" after talking through fears. Listening to music to relax.
Subjective: Soaking pad and tampon hourly. Objective: Scheduled for total abdominal hysterectomy. Pre-existing anemia.
Diagnosis:Risk for Bleeding related to underlying condition and impending surgery.
- Remain hemodynamically stable.
- Pre-op prep for blood loss completed.
- Verbalize post-op signs of excessive bleeding to report.
Interventions:
1. Ensure current CBC, blood type, and screen are on chart.
2. Monitor vitals for hypotension/tachycardia.
3. Educate to report soaking >1 pad/hour post-op.
4. Ensure surgical consent (incl. blood transfusion) is signed.
5. Assess/stop anticoagulant use (NSAIDs/fish oil).
Rationale: Type/screen ensures blood is readily available. Stopping NSAIDs prevents coagulation failure during surgery.
Goals Met. Labs complete, consent signed. Patient states two signs of post-op bleeding to report. Hemodynamically stable.
References
1. Myles Textbook for Midwives (Latest Edition) - Anatomy and Physiology of the Female Reproductive System.
2. DC Dutta's Textbook of Gynecology - Benign Lesions of the Uterus.
3. UNMEB Curriculum for Diploma in Midwifery Extension Program - Gynaecology & Reproductive Health (DME 112).
4. Clinical Guidelines for Obstetrics and Gynaecology (Ministry of Health, Uganda).
Quick Quiz
Fibroids Quiz
Gynaecology
Privacy: Your details are used only for quiz tracking and certificates.
Home > Gynaecology & Reproductive Health > Pelvic Inflammatory Diseases (PID)
Pelvic Inflammatory Diseases (PID)
Pelvic Inflammatory Diseases (PID) refer to a spectrum of severe, acute, or chronic infections that ascend and affect the upper female genital tract and its surrounding structures.
These affected pelvic organs and structures primarily include:
The Cervix (Cervicitis)
The Endometrium (Endometritis)
The Fallopian Tubes (Salpingitis)
The Ovaries (Oophoritis)
The Pelvic Peritoneum and Pelvic Vascular System
PID is a major cause of gynecological morbidity, contributing heavily to female infertility, chronic pelvic pain, and ectopic pregnancies.
Causes and Causative Organisms of PID
PID is rarely caused by a single mechanism; it is usually a polymicrobial infection. The infection reaches the sterile upper genital tract through three primary routes of spread:
1. Ascending Infections: This is the most common route. It occurs when pathogenic bacteria from the vagina or cervix travel upwards through the endocervical canal into the normally sterile reproductive organs (uterus, fallopian tubes, and ovaries).
2. Haematogenous Infections: Infections that are spread systemically through the bloodstream to reach the pelvic organs (e.g., Tuberculosis).
3. Direct Spread: Infection spreading from infected neighboring or adjacent organs. For example, a ruptured or highly infected appendix (appendicitis) can directly spill purulent material into the pelvic region, infecting the fallopian tubes.
Specific Causative Organisms
PID is often polymicrobial, involving both aerobic and anaerobic bacteria. The most common culprits include:
Neisseria gonorrhoeae: A primary sexually transmitted pathogen responsible for severe acute PID.
Chlamydia trachomatis: Another major sexually transmitted pathogen, often causing silent or subclinical but highly destructive PID.
Haemophilus influenzae
Escherichia coli (E. coli): Common in obstetric PID or when bowel flora cross-contaminates the vagina.
Anaerobes: Organisms associated with bacterial vaginosis (e.g., *Gardnerella vaginalis*).
Risk Factors for Developing PID
Certain behavioral, medical, and obstetric factors highly increase a woman's vulnerability to developing Pelvic Inflammatory Disease. These include:
History of STIs: Previous or current untreated sexually transmitted infections, especially Gonorrhea and Chlamydia.
Bacterial Vaginosis (BV): An overgrowth of harmful bacteria causing an imbalance in normal, protective vaginal flora (Lactobacilli).
Sexual Practices: Having multiple sexual partners or a partner who has multiple partners, increasing exposure to pathogens.
Douching: This practice vigorously washes away protective vaginal mucus and flora, and can actively push existing lower tract bacteria up into the uterus.
Previous History of PID: One episode of PID heavily damages protective mucosal barriers, drastically increasing the risk of recurrence.
Use of Intrauterine Devices (IUDs): The risk is slightly elevated immediately after insertion if pre-existing cervical infections are pushed into the uterus.
Surgical/Gynecological Procedures: Invasive procedures like Dilation and Curettage (D&C), manual vacuum aspiration, or hysteroscopy can introduce bacteria.
Obstetric Causes: Infections following abortion, ectopic rupture, or puerperal sepsis (postpartum infections).
Pathophysiology of PID
The disease process of PID is highly destructive to the delicate reproductive tissues. It typically follows this pattern:
The infection typically begins localized in the vagina and cervix (often asymptomatic or presenting as mild cervicitis).
The bacteria then actively ascend through the endocervical canal to reach the Fallopian tubes and ovaries. During menstruation, the endocervical canal naturally dilates slightly and the protective cervical mucus plug is lost, facilitating the easy entry of bacteria into the uterus.
Once inside the highly vascular reproductive tracts, the bacteria rapidly multiply. The body's immune response triggers massive inflammation.
This inflammation destroys the tiny, hair-like cilia inside the fallopian tubes, causing purulent exudate (pus) to build up.
The infection can then easily spill out of the open ends (fimbriae) of the fallopian tubes, spreading further to the ovaries, the pelvic peritoneum, and even other abdominal organs, causing severe peritonitis.
Visual comparison: Normal female reproductive anatomy versus ascending infection showing severe Salpingitis and Oophoritis.
Clinical Manifestations (Signs and Symptoms)
The clinical presentation of PID can vary from mild, vague discomfort to an acute, life-threatening acute abdomen. Diagnosis relies heavily on detailed history-taking and physical examination.
1. On History Taking (What the Patient Reports)
Severe Lower Abdominal Pain: Approximately 70% of individuals with PID experience intense, continuous pain in the lower abdomen. It can be localized (one side) or diffuse (spread out). It heavily worsens during movement, walking, or sexual activity (dyspareunia).
Acute Fever: Around 40% of PID cases present with a high fever (often >38°C) accompanied by chills, responding to the massive internal infection.
Purulent Vaginal Discharge: About 90% of PID patients complain of a heavy, purulent (pus-like) vaginal discharge. It is often thick, yellowish or greenish, and foul-smelling.
Menstrual Changes: Severe inflammation disrupts normal hormonal and uterine function leading to:
Menorrhagia: Heavy or abnormally prolonged bleeding.
Oligomenorrhea: Infrequent, irregular, or scanty periods.
2. On Physical Examination (What the Midwife/Doctor Finds)
Signs of Inflammation: The pelvic region may feel unusually warm, swollen, and look reddened externally.
Peritoneal Signs: Abdominal palpation reveals peritonitis signs: Guarding (involuntary tensing of abdominal muscles to protect inflamed organs), Abdominal distension, and Rebound tenderness (sharp pain felt when the examiner's pressing hand is quickly released).
Vaginal Examination (Speculum & Bimanual):
Vaginal Changes: The vaginal walls appear red, highly inflamed, and dry due to ongoing local irritation.
Purulent Discharge: Pus is visibly seen escaping from the cervical os.
Cervical Excitation (Chandelier Sign): Extreme pain when the cervix is gently moved side to side during a bimanual exam.
Tender Fornices: Palpation of the vaginal fornices reveals extreme tenderness and possibly a swollen mass, indicating pyosalpinx (accumulation of pus in the Fallopian tubes).
Specific Pelvic Infections Breakdown
PID is an umbrella term. Depending on exactly where the infection settles, it is medically divided into the following specific inflammatory conditions:
Condition
Definition
Specific Signs & Symptoms
Cervicitis
Inflammation of the cervix (the lower part of the uterus opening into the vagina). Often caused by Chlamydia/Gonorrhea.
Red, swollen cervix.
Cervical friability: Slight bleeding on intercourse or contact.
Itching/burning sensation in the vagina.
Watery, yellowish, or greenish abnormal discharge.
Endometritis
Inflammation of the endometrium (the inner lining of the uterus). Often occurs postpartum, post-abortion, or post-IUD insertion.
Enlargement of the uterus: Feels boggy, tender, and larger than normal.
Foul-smelling, offensive lochia/discharge.
Lower abdominal pain and high fever.
Salpingitis
Inflammation of one or both fallopian tubes. It is a highly destructive complication causing tubal blockage.
Severe lower abdominal or lower back pain.
Dyspareunia: Deep pain during sexual intercourse.
Risk of forming a pus-filled tube (pyosalpinx).
Oophoritis
Inflammation of one or both ovaries. Often occurs in conjunction with salpingitis (Salpingo-oophoritis).
Deep pelvic, abdominal, and back pain.
Dyspareunia.
Palpable, highly tender adnexal mass.
Hospital Management of PID
Because PID can permanently damage a woman's reproductive system, aggressive, immediate, and comprehensive management is required.
1. Main Aims of Management
To strictly prevent permanent complications (like infertility and ectopic pregnancy).
To quickly relieve the intense pain.
To completely eradicate the infection and prevent the disease from spreading to the peritoneum or systemic bloodstream.
2. Nursing & Supportive Care
Admission & Position: Admit the patient to a clean, well-ventilated gynecological ward for strict, complete bed rest. Place the patient in a Semi-Fowler’s position (propped up). Gravity assists in draining the purulent discharge downwards and prevents the pus from flowing upwards into the abdominal cavity (preventing generalized peritonitis).
Hydration: The patient is often febrile and dehydrated. Start an I.V. line immediately and administer intravenous fluids (like Normal Saline or Ringer's Lactate). Encourage high oral fluid intake if she can tolerate it without vomiting.
Histories & Examination: Take exhaustive medical and sexual histories. Conduct a comprehensive general and abdominal examination.
Continuous Observations: Monitor vital signs strictly (Temperature, Pulse, Respiration, Blood Pressure) every 4 hours. Daily, observe and accurately record the color, specific amount, and smell of the vaginal discharge on a fluid chart.
Diet & Elimination: Advise a highly nutritious, easily digestible diet. Provide a bedpan or urinal to maintain bed rest. Observe the urine; disinfect urine and feces with a strong hypochlorite solution (like JIK) before disposal to prevent cross-infection.
Hygiene & Exercise: Perform bed-making daily, removing wrinkles to prevent bedsores. Once the fever breaks and pain reduces, encourage light physical exercise (like walking around the ward) to prevent DVT.
Care of Mind (Psychotherapy): Severe pain and fears of infertility cause high anxiety. Reassure the patient and her relatives constantly. Provide diversional therapies like newspapers, TV, or radios.
3. Diagnostic Investigations
Do not delay initial treatment waiting for results, but perform these urgently:
High Vaginal Swab (HVS) / Endocervical Swab: Sent for Culture and Sensitivity (C&S) to exactly identify the causative bacteria (e.g., Gonorrhea).
Urinalysis: For C&S to rule out a concurrent severe Urinary Tract Infection (UTI).
Blood Tests: A blood culture for C&S to check for a hematogenous (bloodstream) source or septicemia. A malaria blood slide (BS) to rule out malaria as a cause of the high fever. Complete Blood Count (CBC) to check for highly elevated White Blood Cells (Leukocytosis).
Ultrasound Scan: A pelvic scan is critical to rule out other severe causes of acute abdominal pain (e.g., ruptured ectopic pregnancy, acute appendicitis, or the presence of a massive Tubo-Ovarian Abscess).
4. Medical Treatment (Pharmacology)
Treatment is started immediately using powerful broad-spectrum antibiotics before laboratory results return, covering both aerobic and anaerobic bacteria.
Initial I.V. Antibiotic Regimens:
Ceftriaxone 2g daily IV for 5 days.
Chloramphenicol 2g stat, then 1g 6-hourly for 5 days.
Gentamicin 160mg Once Daily (OD) for 5 days.
Metronidazole 500mg I.V. 8-hourly (TDS) for strict anaerobic coverage.
Oral Step-Down Therapy: If the fever subsides and discharge drastically reduces, switch to oral antibiotics based on sensitivity results. Common choices include Azithromycin (1g single dose for Chlamydia), Doxycycline (100mg BD for 14 days), Ciprofloxacin, or Tetracycline.
Analgesics: Severe pain requires powerful relief. Administer strong NSAIDs like Diclofenac or Ibuprofen to reduce both pain and local inflammation. In extremely severe cases, short-term narcotics (e.g., Pethidine) may be required. Paracetamol is used to control fever.
⚠️ Attention: Severe Complications of PID
If PID is left untreated, inadequately treated, or if the patient presents too late, the irreversible destruction of pelvic tissues leads to life-altering complications:
Infertility: Severe inflammation leaves thick scar tissue blocking the fallopian tubes, preventing the sperm from reaching the egg.
Ectopic Pregnancy: The damaged, narrowed tubes may allow sperm up, but trap the larger fertilized embryo, causing it to grow and dangerously rupture the fallopian tube.
Pelvic Abscess & Tubo-Ovarian Mass: Massive collections of walled-off pus (abscesses) forming dangerous masses involving the tubes and ovaries.
Chronic Pelvic Pain & Adhesions: Thick scar tissue binds the pelvic organs and intestines together like glue, causing permanent, agonizing daily pain.
Intestinal Obstruction & Peritonitis: Severe infection spills into the abdominal cavity, paralyzing or blocking the bowels.
Advice on Discharge
A comprehensive counseling session must be held before the patient goes home to prevent recurrence:
Medication Compliance: Strictly complete the entire 14-day course of oral antibiotics, even if the pain has completely stopped.
Partner Treatment: Emphasize that all recent sexual partners MUST be tested and treated simultaneously to prevent the "ping-pong" re-infection cycle.
Safe Sex Practices: Strongly advise a reduction in multiple sexual partners. Advocate for the strict, consistent use of barrier methods (condoms).
Contraception Review: Advise avoiding Intrauterine Contraceptive Devices (IUDs) if she is at high risk for STIs. Discuss safer alternative methods.
Hygiene: Educate on proper perineal hygiene (wiping front to back) and strictly forbid vaginal douching.
Follow-up: Instruct the patient to return to the clinic immediately for review if she experiences a relapse of pain, abnormal discharges, itching, or fever.
💡 Quick Practice Check
Question: Why is a patient admitted with severe acute PID placed specifically in a Semi-Fowler’s (propped up) position in bed?
Answer: To utilize gravity to help drain the toxic, purulent discharge downwards and out through the vagina, preventing the pus from tracking upwards and spilling into the abdominal cavity, which would cause a deadly generalized peritonitis.
Endometritis
Endometritis is a specific inflammatory condition characterized by the severe inflammation and infection of the endometrium (the innermost mucosal lining of the uterus).
It can present as an acute infection (sudden and severe) or a chronic condition (long-lasting, often silent). It is one of the most common precursors to widespread Pelvic Inflammatory Disease (PID) if the bacteria are allowed to ascend further into the fallopian tubes.
Causes and Major Risk Factors
Endometritis is primarily caused by an ascending bacterial infection from the lower genital tract (vagina or cervix). The highly vascular, nutrient-rich lining of the uterus provides a perfect environment for rapid bacterial multiplication once the protective cervical barrier is breached.
The condition is most commonly triggered by major obstetric or surgical events that introduce bacteria directly into the uterine cavity:
Postpartum (Childbirth): The most common cause. After delivery, the raw, open placental site acts as a massive wound. If bacteria enter during prolonged labour, frequent vaginal examinations, or unhygienic delivery practices, puerperal endometritis develops rapidly.
Post-Abortion: Induced or spontaneous abortions (miscarriages), especially if retained products of conception (tissue) are left behind in the uterus, provide a breeding ground for bacteria.
IUD Insertion: The physical insertion of an Intrauterine Contraceptive Device (IUD) can accidentally push pre-existing cervical bacteria (like Chlamydia or Gonorrhea) up into the sterile endometrium.
Gynecological Procedures: Invasive procedures such as Dilation and Curettage (D&C), hysteroscopy, or endometrial biopsies.
Clinical Manifestations (Signs and Symptoms)
A mother or patient presenting with endometritis will typically exhibit a combination of localized pelvic symptoms and systemic signs of infection. The midwife must carefully assess for the following:
Acute Fever and Chills: The patient will often present with a suddenly elevated body temperature (typically above 38.0°C or 100.4°F) accompanied by chills and tachycardia (fast heart rate). This is the body's aggressive systemic response to the bacterial infection inside the uterus.
Severe Lower Abdominal Pain: A hallmark symptom. The patient will complain of continuous, deep, dull, or cramping pain and extreme discomfort in the lower abdomen/pelvic region due to the severe swelling of the uterine lining.
Abnormal Vaginal Discharge: The infection produces heavy, purulent (pus-filled) vaginal discharge. In postpartum women, this manifests as highly offensive, foul-smelling lochia that may appear yellowish, greenish, or dark brown and prolonged.
Enlargement of the Uterus (Subinvolution): Upon abdominal palpation or bimanual examination, the uterus will feel extremely tender, "boggy" (soft instead of firm), and larger than expected. The severe inflammation prevents the uterine muscles from effectively contracting and shrinking back to their normal size.
General Malaise: The patient will look visibly ill, fatigued, and may experience anorexia (loss of appetite), nausea, or headaches due to the circulating bacterial toxins.
⚠️ Attention: The Danger of Untreated Endometritis
Endometritis is a medical emergency. If the infection is not aggressively treated with strong intravenous broad-spectrum antibiotics, the bacteria will rapidly ascend out of the uterus and destroy the upper reproductive organs, leading to permanent, irreversible complications.
Severe Complications of Untreated Endometritis
Poorly managed or delayed treatment of endometritis sets off a chain reaction of destructive pelvic inflammatory diseases. The direct complications include:
Salpingitis: The infection spreads directly from the uterine lining into the fallopian tubes, causing severe inflammation and filling the tubes with pus (pyosalpinx).
Pelvic Abscess & Tubo-Ovarian Mass: Massive, dangerous pockets of pus form in the pelvic cavity, wrapping around the fallopian tubes and ovaries, often requiring emergency surgery to drain.
Infertility: The intense inflammation leaves behind thick, fibrous scar tissue that permanently blocks or damages the fallopian tubes, preventing sperm and egg from meeting.
Ectopic Pregnancy: Because the delicate inner hairs (cilia) of the fallopian tubes are destroyed by the infection, a fertilized egg may get stuck in the tube instead of reaching the uterus, leading to a life-threatening ruptured ectopic pregnancy.
Chronic Pelvic Pain & Adhesions: Severe scarring causes the pelvic organs (uterus, tubes, ovaries, and bowels) to stick together unnaturally, resulting in debilitating, constant pain that lasts for years.
Peritonitis: The infection completely spills out of the reproductive tract and deeply infects the entire lining of the abdominal cavity, a deadly condition.
Intestinal Obstruction: As pelvic adhesions and scar tissue form, they can wrap around and strangle the intestines, causing a partial or complete blockage of the bowels.
💡 Quick Practice Check
Question: A mother who delivered a baby 4 days ago presents to the clinic with a high fever, a soft/boggy uterus that is larger than expected, and highly offensive, foul-smelling lochia. What specific condition must the midwife suspect immediately?
Answer:Puerperal Endometritis. The combination of fever, subinvolution (boggy, enlarged uterus), and foul-smelling discharge in the postpartum period are the classic triad of this dangerous uterine infection.
Endometriosis
Endometriosis is a chronic, often painful gynecological condition where tissue that behaves exactly like the lining of the uterus (the endometrium) grows outside the uterine cavity.
Unlike Endometritis (which is an infection/inflammation of the inside lining), Endometriosis involves stray endometrial tissue implanting on organs such as the ovaries, fallopian tubes, the pelvic peritoneum, the Pouch of Douglas, and sometimes the bowel or bladder.
Because this misplaced tissue responds to monthly ovarian hormones just like the normal uterine lining, it builds up, breaks down, and bleeds every menstrual cycle. However, because this blood has no way to exit the body, it becomes trapped, leading to severe inflammation, excruciating pain, scar tissue, and infertility.
Causes and Theories of Origin
The exact, definitive cause of endometriosis remains a medical mystery. However, several highly researched scientific theories explain how this tissue escapes the uterus:
Retrograde Menstruation (Sampson’s Theory): This is the most widely accepted theory. It suggests that during menstruation, some of the menstrual blood containing live endometrial cells flows backwards through the fallopian tubes and spills into the pelvic cavity, instead of leaving the body through the vagina. These stray cells then stick to the pelvic walls and organs, where they grow and thicken.
Cellular Metaplasia: This theory suggests that cells in the abdomen or pelvis retain their embryonic ability to transform (metaplasia) into endometrial cells under the influence of hormones or immune factors.
Lymphatic and Vascular Spread: Just like cancer cells, endometrial cells may travel through the blood vessels or the lymphatic system to reach distant parts of the body (which explains rare cases of endometriosis found in the lungs or brain).
Immune System Dysfunction: A normal immune system should recognize and destroy endometrial-like tissue growing outside the uterus. In women with endometriosis, the immune system fails to seek and destroy these rogue cells.
Surgical Scar Implantation: After surgeries involving the uterus, such as a Cesarean section (C-section) or a myomectomy, endometrial cells can accidentally attach to the surgical incision site (e.g., the abdominal wall scar).
Clinical Manifestations (Signs and Symptoms)
The primary symptom of endometriosis is pelvic pain, often specifically tied to the menstrual cycle. The severity of the pain does not always correlate with the extent of the disease (some women have severe disease but little pain, and vice versa).
Severe Dysmenorrhea: Excruciating pelvic pain and cramping that begins before the menstrual period and lasts several days into it. It is often described as feeling far worse than "normal" period cramps.
Dyspareunia: Deep pelvic pain during or immediately after sexual intercourse. The thrusting motion hits the tender, inflamed endometrial nodules tethered behind the uterus or in the vaginal fornices.
Chronic Pelvic Pain: A continuous, heavy, dull ache in the lower abdomen, lower back, and pelvis that happens even when not menstruating.
Dyschezia and Dysuria: Intense pain during defecation (passing stool) or urination, particularly during the menstrual period. This occurs when endometrial tissue implants on the bowel or bladder.
Menorrhagia and Menometrorrhagia: Experiencing excessively heavy menstrual periods or bleeding irregularly between periods.
Infertility: Endometriosis is diagnosed in up to 50% of women seeking treatment for infertility. The thick scar tissue (adhesions) distorts the pelvic anatomy, blocking the fallopian tubes and preventing the egg and sperm from uniting.
⚠️ Attention: The "Chocolate Cyst"
When endometrial tissue implants deeply into an ovary, it bleeds into itself every month. Over time, this old, trapped, oxidized blood turns thick and dark brown, forming an Endometrioma, classically referred to in gynecology as a "Chocolate Cyst." If a chocolate cyst ruptures, it causes an acute, surgical abdominal emergency.
Diagnosis of Endometriosis
Because the symptoms heavily mimic other pelvic diseases (like PID or Ovarian Cysts), a definitive diagnosis requires specialized investigations:
Detailed Pelvic Examination: The healthcare provider may feel cysts on the reproductive organs or thick scars behind the uterus.
Transvaginal Ultrasound (TVUS): Highly effective for identifying specific endometrial cysts (endometriomas) on the ovaries, though it may miss smaller, flat implants.
Magnetic Resonance Imaging (MRI): Gives a much more detailed image to map out the exact locations and depths of the endometrial implants prior to surgery.
Diagnostic Laparoscopy (The Gold Standard): A tiny camera is inserted through a small abdominal incision. This is the only way to 100% definitively diagnose endometriosis. The surgeon can directly visualize the classic "powder-burn" lesions, take a biopsy for histology, and remove the implants simultaneously.
Management and Treatment
There is currently no absolute cure for endometriosis. Treatment is highly individualized based on the severity of symptoms, the extent of the disease, and whether the woman desires to have children in the future.
1. Medical / Pharmacological Management
The goal is to relieve pain and suppress the menstrual cycle, effectively starving the misplaced tissue of the hormones it needs to bleed and grow.
Analgesics: Non-steroidal anti-inflammatory drugs (NSAIDs) like Ibuprofen or Diclofenac are used aggressively to reduce inflammation and severe cramping.
Hormonal Contraceptives: Combined oral contraceptive pills (COCs), patches, or vaginal rings are used continuously to stop the hormonal fluctuations, thereby reducing or entirely stopping the bleeding and pain.
Progestin Therapy: Progestin-only pills, contraceptive implants, or the Mirena IUD halt the menstrual periods and prevent the growth of endometrial implants.
GnRH Agonists (e.g., Danazol, Zoladex): These powerful drugs block the production of ovarian-stimulating hormones, causing a temporary "medical menopause." This stops menstruation entirely, forcing the endometriosis to drastically shrink.
2. Surgical Management
Conservative Surgery (Laparoscopy): For women trying to get pregnant or suffering severe pain. The surgeon carefully excises (cuts out) or burns away (ablates) the endometrial lesions and scar tissue while leaving the healthy uterus and ovaries perfectly intact.
Definitive Surgery (Hysterectomy): Used only as a last resort for women who have severe, uncontrollable pain and do not wish to have any more children. It involves the total removal of the uterus (Total Abdominal Hysterectomy), and frequently the removal of both ovaries and fallopian tubes (Bilateral Salpingo-Oophorectomy) to permanently stop all hormone production.
3. Nursing Care and Psychotherapy
Provide extensive emotional support. Endometriosis causes immense psychological stress, depression, and anxiety due to chronic pain, dyspareunia (which damages relationships), and the devastating fear of infertility.
Educate the mother extensively on her medication compliance, especially the side effects of hormone therapies (like weight gain or menopausal flashes from GnRH agonists).
Encourage attendance at specialized fertility or chronic pain support groups.
💡 Quick Practice Check
Question: A 28-year-old woman is admitted to the gynecology ward complaining of severe, incapacitating pelvic pain exactly three days before her period starts, deep pain during sexual intercourse, and inability to conceive for 3 years. Her ultrasound reveals a large "chocolate cyst" on her left ovary. What is the most likely diagnosis?
Answer:Endometriosis. The classic triad of severe dysmenorrhea, dyspareunia, and infertility, combined with an endometrioma (chocolate cyst) on the ovary, points definitively to endometriosis.
References
Ministry of Health (MOH) Uganda - National Clinical Guidelines for the Management of Common Conditions.
Berek, J. S. (Ed.). Berek & Novak's Gynecology. Wolters Kluwer.
Syllabus guidelines for Diploma in Midwifery Extension Program, Uganda Nurses and Midwives Council (UNMEB).
Quick Quiz
PID Quiz
Gynaecology
Privacy: Your details are used only for quiz tracking and certificates.
Home > DME 112: Gynaecology & Reproductive Health > Infertility
Infertility
Infertility refers to the failure or inability of a couple to conceive (get a child) after one full year of regular, unprotected sexual intercourse (coitus) during the childbearing age (15–49 years) without using any form of contraception.
Types of Infertility:
Primary Infertility: The inability to conceive in a couple that has had absolutely no previous pregnancies at any time after 1 year of unprotected sex.
Secondary Infertility: Refers to a couple who have previously succeeded in achieving at least one pregnancy (even if it ended in a spontaneous abortion/miscarriage) but are now unable to conceive again despite regular unprotected sex.
⚠️ Attention: Infertility vs. Sterility
The term Sterility should only be used when there is absolutely no possible treatment to enable a couple to conceive (achieve pregnancy). For example, when a man has no testes (anorchia) or a woman lacks a uterus (hysterectomy or congenital absence).
Conditions for Normal Implantation and Conception
For a pregnancy to successfully occur, a very specific chain of events must be perfectly executed. The following conditions must be fulfilled:
There should be two partners actively involved and willing.
They must engage in regular, unprotected coitus without any form of contraception.
They must use the right sexual route (vaginal penetration with ejaculation).
The female should be within the active childbearing age (14 to 49 years).
The male must release healthy semen containing a normal count of motile and morphologically normal spermatozoa.
A normal, healthy ovum (egg) must be released from the female's ovary (ovulation).
The ovum must unite with the sperms in the fallopian tube to be fertilized.
The fertilized ovum (zygote) must successfully travel to and implant in the healthy endometrium of the uterus.
Causes of Infertility in Males
Male factor infertility accounts for a significant portion of infertility cases. The causes range from psychological to severe physiological and genetic abnormalities:
Sperm Abnormalities: The release of immature sperms, structurally abnormal sperms, too few sperms (oligospermia), or sperms that are too slow in movement (asthenospermia).
Ejaculatory Issues: Poor ejaculation, premature ejaculation, or complete failure to ejaculate. Retrograde ejaculation is a specific condition where semen is ejaculated backward into the bladder instead of out through the urethra (assessed by urinalysis after ejaculation).
Extreme Heat: An increase in the temperature of the testes from a prolonged fever, tight clothing, or occupational exposure to excessive heat can greatly reduce sperm count, reduce the vigor of sperm movement, and increase the number of abnormal sperms in the semen.
Hydrocele: Excessive collection of fluid in the scrotum. This extra fluid creates pressure and alters the environment, preventing the adequate production of sperms.
Varicocele: Varicose (swollen and enlarged) veins of the scrotum. This abnormality prevents the proper supply and drainage of blood from the testes, thus raising the scrotal temperatures and drastically reducing the rate of sperm production. It also affects the quality of ejaculation.
Medications & Drugs: Certain drugs cause failure in erection or spermatogenesis. Examples include amoebicides (for amoebiasis), anti-hypertensives like Aldomet (Methyldopa), and diabetic drugs. Nitrofurantoin (an antibiotic) can cause degenerative changes in sperms.
Infections: Diseases like Mumps in adult males can cause Orchiditis (severe inflammation of the testes), leading to permanent testicular damage and sterility.
Hormonal Imbalance: Inadequate production of testosterone from the Leydig cells can result in immature sperms and poor libido.
Lifestyle Factors: Excessive smoking, chronic alcohol consumption, severe obesity, and extreme depression or stress heavily inhibit spermatogenesis and sexual performance.
Toxic Exposure: Chronic exposure to toxic industrial chemicals, heavy metals, or radiations physically damages the germinal epithelium of the testes, halting spermatogenesis.
Genetic Factors in Males
Klinefelter’s Syndrome: A chromosomal genetic syndrome where a male has 47 chromosomes with an extra X chromosome (47, XXY instead of the normal 46, XY). The loss of a dominant Y-chromosome effect leads to a feminine body build. It presents with gynaecomastia (enlarged breasts), testicular atrophy (shrinking testes), azoospermia (zero sperms), and complete infertility. The testicular atrophy is a result of peritubular fibrosis commencing in childhood and progressing until all seminiferous tubules are replaced by useless fibrous tissue.
Causes/Factors of Infertility in Females
Female infertility is deeply complex and is clinically best discussed under the following distinct headings:
1. Defective Implantation & Tubal Factors
Tubal blockage is the major cause of infertility, especially in Uganda, contributing to 60 – 70% of cases.
Pelvic Inflammatory Disease (PID) & Salpingitis: Infection of the fallopian tubes caused by Gonorrhoea, Chlamydia, Tuberculosis, or pelvic peritonitis (e.g., from a burst appendix) after an abortion or delivery. This damages the delicate ciliated tubal epithelium. In severe cases, it causes total tubal blockage. This mostly occurs at the outer end of the tube where the fimbriae adhere together, but it is also seen in the very narrow, interstitial part of the tube.
Ectopic Risks: When the tubes are not completely blocked, fertilization of the ovum may still take place. However, because of the damage to the ciliated epithelium, the fertilized ovum cannot be carried down the tube to the uterus, resulting in a dangerous Ectopic Pregnancy.
Uterine Abnormalities: Congenital malformations such as having no uterus, a bicornuate uterus (heart-shaped), or a Didelphys uterus (two completely separate horns and cervixes).
Uterine Fibroids: Gross fibroids create an irregular, bumpy implantation surface or physically block the fallopian tube ostia.
Uterine Synechiae (Asherman's Syndrome): Severe inflammation of the endometrium (endometritis) or scarring caused by over-curetting of the uterus during a D&C, or from surgeries like myomectomy, leads to the walls of the uterus sticking together (intrauterine adhesions).
Endometriosis: A painful condition where patches of endometrial-like tissue develop outside the uterine cavity in abnormal locations (ovaries, fallopian tubes, abdominal cavity). This tissue grows and bleeds with hormonal stimulation, causing massive inflammation, scar tissue, pelvic adhesions, and infertility.
Cervical & Vaginal Issues: Stenosed (narrowed) cervix due to trauma/surgery. Acquired or congenital Gynaeatresia (a very small vaginal hole with a blind end), septate vagina, or a completely rigid hymen preventing penetration.
Infections & Contraceptives: Severe Trichomonas vaginalis infections (evidence of cause noted in Zambia). Prolonged use of barrier contraceptives (condoms, IUDS, Spermicides) without recognizing underlying fertility delays.
2. Endocrine (Hormonal) Disorders
Hypothalamic-Pituitary Inefficiency: Stress, extreme weight loss, or excessive weight gain causes an unstable cerebrum and hypothalamus. This alters dopamine or noradrenaline transmission. Certain drugs (Rawolfia, phenothiazines, Metoclopramide) also suppress hypothalamic function, leading to failure of ovulation.
Hyperprolactinaemia: A pituitary tumor (micro or macroadenoma) leading to the production of excessive Prolactin hormone. Elevated prolactin is normal during lactation (causing lactational amenorrhea), but if a woman is not lactating, this hormone suppresses GnRH, causing total anovulation.
Thyroid & Adrenal Function: Hyperthyroidism, Hypothyroidism, Cushing's syndrome, or Congenital Adrenal Hyperplasia all cause severe hormonal imbalances resulting in anovulation.
Age & Menopause: Fertility steeply declines with advanced age. Postponement of childbearing for careers frequently leads to age-related ovulatory decline.
3. Ovarian Causes
Resistant Ovary Syndrome: Absence of FSH receptors in the ovarian follicle leads to the complete failure of the ovary to respond to gonadotrophins.
Polycystic Ovarian Syndrome (PCOS): Disturbance in the interaction between FSH and the follicle results in an abnormal enzyme reaction. The follicles fail to rupture (anovulation), and the ovary becomes enlarged and multicystic. Without ovulation, the endometrium lacks secretory changes, and cervical mucus remains thick and impenetrable by sperms.
Ovarian Damage/Absence: Congenital lack of eggs/follicles, premature menopause, surgical removal of the ovary by mistake, or destruction of the ovarian substance by deep infections like Mumps.
Radiation Exposure: Chronic or excessive exposure to radioactive substances or X-rays physically damages and mutates the delicate ova.
4. Defective Transport & Hostility
Cervical Hostility: A condition in which the cervical mucus is totally unreceptive to spermatozoa. The mucus either blocks their progressive advance or actively kills them. This may be due to chronic cervical infection or the presence of specific Sperm Antibodies (an allergic immune response to the man's sperms).
Vaginal pH: A highly acidic vaginal pH rapidly destroys the motility of the sperms before they can enter the protective cervix.
5. Physical, Psychological & Systemic Causes
Psychological & Sexual Dysfunction:Dyspareunia (severe painful sexual intercourse due to psychological or physical factors) and Vaginismus (involuntary spasms of the pelvic floor muscles preventing penetration).
Wrong Timing: Having sexual intercourse exclusively during infertile periods (miscalculating the ovulation window).
Systemic Diseases: Chronic, uncontrolled diseases such as Diabetes Mellitus, severe Hypertension, and Renal Failure drastically lower fertility chances.
Turner’s Syndrome (Genetic): Caused by the complete deletion or abnormality in one of the female's two X chromosomes (Karyotype 45, XO). These females present with complete ovarian failure (streak ovaries), widely spaced nipples, cardiovascular problems, squints, hypothyroidism, and diabetes mellitus. They face absolute infertility and require estrogen therapy in adult life.
General Investigations & Evaluation
All couples complaining of infertility must be investigated together. The length and depth of the investigations will vary depending on the initial findings.
Evaluation in Women
1. Comprehensive History & Physical Examination
Menstrual History: Age of menarche, length, and regularity of the menstrual cycles.
Gynaecological History: Previous contraceptive use, history of D&C, salpingectomy, abortions, or highly suggestive symptoms of PID.
Obstetric History: Any previous pregnancies and the exact number of children fathered specifically by her current partner.
General Health: Extremely thin women face amenorrhoea due to lack of body fat. Very obese women face anovulation because the ovary cannot secrete enough estradiol, converting androgens into excess estrone instead. Age is strictly noted (above 50 is generally menopause).
Physical Inspection: Check for visual field deficits (suggestive of a large pituitary tumor pressing on the optic chiasm). Check pubic and body hair distribution (presence of male-pattern hair / virilism suggests excess androgens).
Vaginal Examination: Check the normality of the vaginal canal, cervix, and uterus. Confirm pelvic anatomy with an ultrasound.
2. Hormonal & Special Tests
Progesterone Levels: In a standard 28-day cycle, blood is drawn on Day 21 (or 1 week before the expected period). A progesterone level of more than 20 mmol/L firmly confirms that ovulation took place.
FSH and LH Levels: Checked to identify premature menopause, ovarian failure, or polycystic ovaries.
Basal Body Temperature (BBT): The woman takes her oral temperature every morning upon waking, before any physical activity. A sustained rise of about 0.5°C in the last 14 days of the cycle indicates ovulation has occurred. Monitored for 6 months.
Cervical Mucus Examination: Mid-cycle ovulatory mucus is clear, copious, and stretches into a fine thread (called Spinnbarkeit). On a glass slide, it dries to form a characteristic fern pattern under the microscope.
Post Coital Test (Huhner’s Test): Carried out exactly at ovulation. 2 to 8 hours after unprotected intercourse, cervical mucus is withdrawn using a wire loop/pipette, placed on a warm slide, and examined. Normally, a large number of progressively motile sperms are seen. Absence or dead sperms indicate cervical hostility or sperm antibodies.
Prolactin Tests: If prolactin is higher than 800 mU/L, a CT scan of the pituitary fossa is mandatory to exclude a prolactin-producing adenoma.
Endometrial Biopsy: Done 10-12 days after ovulation. Histology will prove if the glands have undergone necessary secretory changes to support an embryo.
3. Tubal Patency Tests
Laparoscopy & Dye Test: The gold standard. A premenstrual procedure combining visual inspection of the pelvis with the injection of dilute methylene blue dye through the cervix. The uterus distends, and if the tubes are patent (open), the dye freely spills from the fimbrial ends. No spill indicates a block. (Pregnancy must be ruled out first).
Hysterosalpingogram (HSG): An opaque radio-aqueous solution is injected through the cervix. An X-ray is taken to visualize the uterine cavity and tubal patency. This is done between day 5 and 10 of the cycle (after bleeding stops but before ovulation).
Tubal Insufflation: An older, highly unreliable method where Carbon Dioxide (CO2) gas is passed into the uterus. Patency is assumed if the gas is heard via auscultation or confirmed on X-ray.
Transvaginal Ultrasound (TVS): Gives clear images of the ovaries and uterus. Contraindications: Suspected pregnancy, severe cervical erosion, active pelvic infection, DUB, or serious heart/lung diseases. Risks: Embolism or ascending infection.
Evaluation in Men
General Exam: Check for severe obesity, diabetes, and hypertension. Evaluate male hair distribution and genital development. Check for surgical scars (e.g., undescended testis operation before puberty).
Breast Check: Enlargement (gynaecomastia) indicates abnormally high estrogen levels or Klinefelter's syndrome.
Testicular Exam: Assess the exact size, consistency, and situation of the testes in the scrotum.
Hormonal Blood Tests: Evaluate FSH, LH, and Testosterone levels to rule out endocrine failure.
🧠 Terminology for Seminal Fluid Analysis
Azoospermia: Absolute lack of sperms in the semen (Zero). Oligospermia: Little or few sperms (Less than 20 million/ml). Asthenospermia: Decreased motility (slow-moving sperms). Teratospermia: Excessive abnormal shapes (monsters/mutations) of the sperms.
Normal Seminal Fluid Analysis Findings
A fresh semen sample is analyzed. Normal parameters must meet or exceed the following:
Volume: ≥ 2.0 to 2.5 ml.
pH: 7.0 to 8.0 (Slightly alkaline to survive the acidic vagina).
Total Sperm Count: More than 20 million per ml.
Liquefaction: Must be completely liquefied within 1 hour.
Motility: ≥ 50% must have strong, forward, progressive motility.
Morphology: ≥ 30% or more must have a perfectly normal shape.
Treatment of Infertility
Treatment is strictly tailored according to the identified underlying cause.
General Preventive Measures & Counseling
Stop all smoking and significantly reduce alcohol consumption.
Adopt a proper, highly nutritious diet to manage weight (obesity or extreme thinness).
Educate the couple on meeting at the exact right time (tracking the fertile ovulation window).
Actively reduce psychological stress, marital tension, and provide deep psychological counseling to prevent depression, divorce, or polygamy.
Treatment in Women
1. Chemotherapy for Anovulatory Infertility
Clomiphene Citrate (Clomid): Induces ovulation by stimulating the Hypothalamic-Pituitary system.
Dosage: 50mg daily for 5 days, starting on the 2nd day of menstruation. If ovulation fails, a second course of 100mg daily for 5 days is given (starting as early as 30 days later). Generally, 3 courses are adequate to assess efficacy.
Side Effects: Ovarian Hyperstimulation Syndrome (OHSS), multiple pregnancies (twins/triplets), visual disturbances, hot flushes, heavy abnormal bleeding (menorrhagia), hair loss, depression, dizziness, and nausea.
Tamoxifen: 20mg daily on days 2, 3, 4, and 5 of the cycle. Dose may be increased to 40mg then 80mg to stimulate ovulation.
Bromocriptine (Parlodel, Dopagon): For hyperprolactinaemic infertility. It inhibits the synthesis and release of prolactin from the pituitary.
Dosage: Initially 1.25mg at bedtime, gradually increased to 2.5mg three times a day with food. Max 30mg daily.
Side Effects: Severe nausea, hypotension, dizziness, nasal congestion, fatigue, and dry mouth.
Interactions: Erythromycin increases its toxicity. Antipsychotics and Metoclopramide antagonize its effect.
Luteinizing Hormone (LH) / GnRH Pumps: Given via a subcutaneous/IV syringe pump releasing 10-25 micrograms every 90 minutes.
HCG & HMG (Pregnyl / Metrodin): Synthetic Human Chorionic Gonadotrophin or Human Menopausal Gonadotrophin triggers ovulation when Clomiphene fails.
2. Surgical Measures in Women
Salpingolysis: Dividing peritubal adhesions around the ampullary ends of the tubes to restore free movement.
Salpingostomy: Surgically turning back the fimbriae to create a brand new opening for a blocked tube.
Tubal Anastomosis & Repair: Coring out the blocked segment (e.g., at the isthmus) and intricately re-stitching (anastomosing) the healthy ends back together.
Myomectomy: Surgical removal of uterine fibroids to clear the implantation space.
Treatment in Men
Medical: Human Gonadotrophin Therapy or Clomiphene Citrate to forcibly stimulate sperm production. Testosterone therapy to stimulate sexual desire (libido) — Note: Do not give exogenous testosterone if the primary issue is impaired spermatogenesis, as it can suppress natural sperm production further.
Surgical: Repair of inguinal hernias, correction of undescended testis, or Varicocelectomy (surgical ligaturing of the internal spermatic vein to reduce testicular heat and pooling). Relief of reproductive tract obstructions.
Assisted Reproductive Technologies (ART) & Other Options
In Vitro Fertilization (IVF)
Developed in 1978 (Robert Edwards won the Nobel Prize for this). IVF bypasses blocked fallopian tubes by fertilizing the egg outside the body.
Process: The woman's ovaries are hyper-stimulated using GnRH agonists and FSH to produce multiple eggs. An HCG "trigger shot" is given. Eggs are retrieved via ultrasound-guided transvaginal aspiration exactly between 34 and 36 hours (just before follicle rupture at 38-40 hrs).
Fertilization: The retrieved eggs are mixed with purified, washed sperms (to remove microbes/HIV) in a laboratory dish.
Transfer: The healthiest resultant embryos are carefully transferred directly into the mother's uterus. (Caution: Often results in multiple pregnancies, and ovarian hyperstimulation must be monitored).
Intracytoplasmic Sperm Injection (ICSI)
Performed alongside IVF for severe male infertility. If sperms are very low in number, highly abnormal, or unable to penetrate the egg wall, a single healthy sperm is captured in a microscopic needle and injected directly into the cytoplasm of the egg.
Other Alternatives
Surrogate Mothers: If a woman lacks a functional uterus, her own IVF embryo (using her egg and husband's sperm) is implanted into another woman's uterus. The surrogate carries the pregnancy and hands the baby over to the genetic parents after birth.
Artificial Insemination by Donor (AID): If the male partner is completely sterile (azoospermia), semen from a healthy, anonymous fertile donor is introduced into the woman's reproductive tract during ovulation.
Adoption: Couples can legally apply to an adoption center to adopt a child of their choice if medical treatments fail.
Nursing Diagnoses & Care for Infertility
The psychological toll of infertility is massive. The midwife/nurse plays a crucial role in providing holistic care:
Anxiety and Fear: Related to unknown invasive diagnostic procedures, complex treatments, and unpredictable outcomes, evidenced by the patient’s constant verbalization of worry. (Intervention: Provide clear, empathetic explanations of all procedures).
Low Self-Esteem & Grief: Related to the inability to conceive, evidenced by low mood, crying, feeling "inadequate," and social isolation. (Intervention: Offer therapeutic communication, refer to support groups).
Knowledge Deficit (Reproductive Process): Related to the complex process of ovulation, fertile windows, and proper sexual relationship timing, evidenced by inadequate verbalization. (Intervention: Teach BBT charting, fertile period calculations, and sexual health).
Knowledge Deficit (Anatomy/Causes): Related to the physical causes of infertility, evidenced by misconceptions. (Intervention: Use anatomical charts to explain tubal blockages, sperm counts, etc.).
💡 Quick Practice Check
Question: A male patient's semen analysis returns with a sperm count of 8 million/ml and highly reduced motility. What are the correct medical terms for these specific findings?
Answer: A count below 20 million/ml is termed Oligospermia, and the decreased motility is termed Asthenospermia.
References
Myles, M. (Latest Edition). Textbook for Midwives. Churchill Livingstone Elsevier.
Uganda Ministry of Health. (2001). Midwifery Handbook and Guide to Practice (11th ed.). Kampala, Uganda.
Stanfield, P., Beladia, & Versluys. (2004). Child Health: A Manual for Medical and Health Workers in Health Centres and Rural Hospitals (2nd ed.). English Press Limited, Nairobi.
Local Clinical Guidelines and Training Manuals for the Diploma in Midwifery Extension Program (UNMEB).
Quick Quiz
Infertility Quiz
Gynaecology
Privacy: Your details are used only for quiz tracking and certificates.