Midwives Revision

Gynaecology

Ectopic Pregnancy
Home > Midwifery I

Ectopic Pregnancy

Overview: An Ectopic Pregnancy is a life-threatening obstetric emergency where a fertilized egg (ovum) implants and grows completely outside the normal uterine cavity. Because these areas cannot stretch or provide enough blood supply like the uterus, the pregnancy cannot develop properly and often results in a dangerous rupture, causing severe internal bleeding.

1. Definition and Causes

Normally, a fertilized egg travels down the fallopian tube and embeds safely inside the thick lining of the uterus. In an ectopic pregnancy, the fertilized ovum embeds outside the uterine cavity.

Causes and Risk Factors

Any condition that slows down or prevents the fertilized egg from moving smoothly down the fallopian tube can cause an ectopic pregnancy.

  • Pelvic Inflammatory Disease (PID): Infections like salpingitis (inflammation of the tubes) destroy the tiny hair-like structures (cilia) inside the tube. PID also forms sticky scar tissue (adhesions) that stop the normal wave-like squeezing motions (peristalsis) of the tubes.
  • Fallopian Tube Damage & Congenital Issues: Previous infections or surgeries can leave behind thick scars. Some women are also born with abnormally long tubes that easily kink (bend), or congenitally narrow tubes, making it hard for the egg to pass.
  • Previous Ectopic Pregnancy: A woman who has already suffered one ectopic pregnancy is at a much higher risk of having another one because the underlying tube damage is usually still present.
  • Endometriosis: This is the abnormal growth of the uterine lining (endometrium) in places outside the uterus. The fertilized egg may accidentally implant on this misplaced tissue.
  • Repeated Induced Abortions: Multiple scraping procedures can introduce infections or cause scarring that damages the reproductive pathways.
  • Tubal Surgery: Surgical operations on the fallopian tubes (like tying them or attempting to unblock them) create scars inside (intraluminal) or outside (extraluminal) the tubes.
  • Intrauterine Devices (IUDs): While IUDs are great at preventing normal pregnancies inside the uterus, if a pregnancy *does* accidentally happen with an IUD in place, it is highly likely to be ectopic because the device blocks the normal implantation site.
  • Tumors: Large growths, like fibroids or ovarian cysts, can press hard against the outside of the fallopian tube, causing a partial or complete physical blockage.
  • Hormonal Factors: Imbalances in hormones can slow down the movement of the egg and affect how quickly it implants.
  • Reproductive System Abnormalities: Being born with a misshapen uterus (like a bicornuate uterus) or abnormally placed tubes.

2. Sites of Ectopic Pregnancy

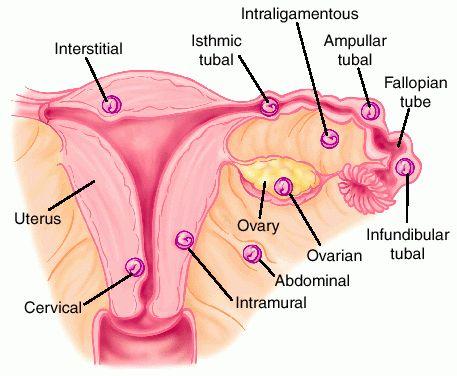
An ectopic pregnancy can happen in several places, but the Fallopian Tubes are by far the most common site (accounting for about 95% of cases). Other rare sites include the broad ligament, the ovary, the cervix, and the intraperitoneal abdominal cavity.

Specific Sites for Tubal Pregnancy

  • Ampulla (Most Common): The widest part of the fallopian tube where fertilization usually occurs. The egg often gets stuck here.
  • Isthmus (Most Dangerous): The narrowest part of the tube. Because it is so small and tight, a growing pregnancy here will cause the tube to burst (rupture) very early, sometimes even before the mother misses her period or realizes she is pregnant.
  • Fimbriated End (Infundibulum): The finger-like ends of the tube (rare site).
  • Interstitial Part: The section of the tube that crosses through the thick uterine wall (rare but causes massive bleeding if ruptured).

3. Possible Outcomes of a Tubal Pregnancy

If the egg implants in the tube, the pregnancy cannot last to term. One of four things will eventually happen:

OutcomeClinical Description
1. Tubal MoleThe fertilized egg (zygote) dies quietly. It is retained inside the fallopian tube, completely surrounded by a thick blood clot. This may result in a slow-leaking, chronic ectopic pregnancy with mild, lingering pain.
2. Tubal AbortionThe zygote completely detaches from the wall of the fallopian tube and is pushed out (expelled) through the open fimbriated end into the abdomen. It may die and be absorbed, or very rarely, it can stick to abdominal organs and become an abdominal pregnancy.
3. Tubal RuptureThe growing baby quickly becomes too large for the tiny tube. The tube violently bursts open, tearing major blood vessels. This causes massive internal bleeding straight into the abdominal cavity, leading to sudden, severe hypovolemic shock.
4. Tubal ErosionThe aggressive cells of the growing zygote slowly eat through (erode) the wall of the fallopian tube, causing a steady leakage of blood into the abdominal cavity.

⚠️ Clinical Emergency: Tubal Rupture

A ruptured ectopic pregnancy is a top-tier obstetric emergency. The mother can bleed to death internally in a matter of hours. Always suspect an ectopic pregnancy in any woman of childbearing age presenting with abdominal pain and fainting, even if she claims she is not pregnant.

4. Signs and Symptoms (Focusing on Tubal Rupture)

On History Taking

  • Amenorrhea: A clear history of missing her periods for 6 to 10 weeks.
  • General Danger Signs: The patient heavily complains of feeling faint, extreme dizziness, severe thirst (a classic sign of internal bleeding), and vomiting.
  • Acute Pain: She reports sharp, sudden, colicky abdominal pain localized in one side of the lower abdomen (iliac fossa).
  • Referred Shoulder Pain: The mother complains of pain at the tip of her shoulder, especially when she lies down flat. This happens because the free blood pooling in her abdomen irritates the diaphragm muscle and the phrenic nerve, which shares a pain pathway with the shoulder.

On Physical Examination

  • Signs of Pregnancy: Early signs may be visible, such as darkening of the breast areola.
  • Signs of Shock: Because of massive internal bleeding, she will have cold and clammy skin, a rapid but very weak (thready) pulse, dangerously low blood pressure, and a slightly low temperature.
  • Mental State: She appears highly anxious, restless, and terrified (air hunger).
  • Pallor: Extreme whiteness (pallor) of the eyes, gums, and mucous membranes due to blood loss.

On Abdominal Palpation

  • Extreme tenderness, especially on the affected side.
  • The abdominal muscles become hard and rigid like a board because the mother is unconsciously guarding against the severe pain.
  • The abdomen is visibly swollen (distended) due to the large amount of free blood floating in the abdominal cavity.

On Vaginal Examination

  • Bleeding Discrepancy: The small amount of bleeding seen coming from the vagina absolutely does not match the mother's severe state of shock (because the real bleeding is hidden inside the abdomen).
  • Cervical Excitation: Moving the cervix slightly during the exam causes her extreme, jumping pain.
  • A distinct, painful swelling or mass can be felt on one side (lateral fornix) or bulging down behind the uterus in the Pouch of Douglas.
  • Dark brown, old blood may be seen on the examining finger.

5. Investigations & Differential Diagnosis

  • Ultrasound Scan: This is the gold standard. It will confirm the diagnosis by revealing an empty uterus, a mass in the fallopian tube, and a large collection of free fluid/blood in the abdomen.
  • Pregnancy Test: A urine or blood hCG test will be positive, proving she is pregnant.
  • Blood Tests: Check Hb (Hemoglobin level will be very low due to bleeding), Grouping, and Cross-matching (to prepare for immediate blood transfusion).
  • Culdocentesis (Emergency Puncture): If a scan is not available in a rural setting, a doctor may insert a needle through the top of the vagina into the Pouch of Douglas. If fresh, non-clotting blood is drawn out (aspirated), it proves there is internal bleeding from a rupture.

❓ Differential Diagnosis

Before confirming an ectopic pregnancy, a midwife or doctor must rule out other conditions that cause severe abdominal pain in women, including:

  • Salpingitis / PID: Specially if associated with foul discharge and irregular menses.
  • Appendicitis: Right-sided pain, often with a fever, but no missed period.
  • Abortion (Miscarriage): Will have heavy vaginal bleeding matching the pain level.
  • Twisted Ovarian Cyst: Sudden, severe pain, but pregnancy test is usually negative.
  • Urinary Tract Infection (UTI): Pain on urination, usually no signs of severe shock.

6. Management at a Health Centre (Primary Care)

At a lower-level health center (Level III or IV), this is a critical emergency. Every second counts to save the mother's life. Do not delay.

Aims of Care: To prevent deep shock, relieve severe pain, reassure the terrified patient, and transfer her safely and immediately.

  • Admission: Temporarily admit her to the gynecological or emergency bed. Quickly take a brief history and do a rapid physical, abdominal, and vaginal examination to make a diagnosis.
  • Observations: Immediately take and record Temperature, Pulse, Respiration, and Blood Pressure to assess how badly her vital organs are failing.
  • Resuscitation (Treatment):
    • Put up an incredibly fast intravenous (IV) drip of Normal Saline to elevate her dropping blood pressure and treat the shock.
    • Administer strong pain relief as prescribed (e.g., Morphine 15mg intramuscularly) to stop pain from worsening the shock.
    • Raise the foot of the bed (Trendelenburg position) to force whatever blood is left to flow to her vital brain and heart centers.
  • Nursing Care: Swab the vulva quickly and apply a clean pad to monitor exactly how much vaginal blood is lost during transit.
  • Transport and Transfer: Inform the patient and her relatives honestly about the danger and the immediate need for surgery. Send for an ambulance or vehicle immediately. Write a detailed referral note stating the time of arrival, her exact condition, and what drugs/IV fluids you have given. A qualified midwife MUST escort the mother to monitor the IV drip and hand her over safely to the hospital staff.

7. Hospital Management

Upon arrival at a main hospital, this is handled as a top-priority gynecological emergency. All nurses and doctors must work as a rapid-response team to get the patient to the operating theatre as fast as possible.

Aims: To treat anemia, reverse shock, reassure the patient, completely stop the internal bleeding, and prevent further complications.

Admission and Immediate Care

  • Admit the patient into a warm, well-ventilated room. Establish a fast but comforting nurse-patient relationship.
  • Take a collateral history from the relatives if the mother is too weak to speak. Focus on exactly when the pain started, vomiting, and missed periods.
  • Call the doctor or surgeon immediately.
  • Do a rapid head-to-toe examination focusing on signs of extreme dehydration, anemia, and hypovolemic shock.

Doctor's Orders and Resuscitation

  • Investigations Ordered: Hb estimation (to see blood lost and rule out malaria), Blood Group & Crossmatch (transfusion is almost always necessary), Pregnancy test, Ultrasound scan, and Urinalysis.
  • IV Fluids & Fluid Balance: Run Normal Saline rapidly. Start a strict fluid balance chart (input vs. output).
  • Blood Transfusion: Book 1 to 2 units of blood immediately based on the Hb results.
  • Pain Relief: Administer strong analgesics like Morphine or Pethidine.
8. Pre-Operative, Theatre, and Post-Operative Care

Pre-Operative Care (Preparation for Theatre)

  • Explain the life-saving nature of the operation and obtain a signed Informed Consent form from her or her husband.
  • Give a quick bed bath, dress her in a clean theatre gown, and inform the theatre staff to prepare.
  • Ensure the IV line is running perfectly. Swab the vulva to prevent taking infections into theatre.
  • Pass a urethral catheter to empty the bladder (an empty bladder is out of the surgeon's way and prevents accidental injury).
  • Pass a Naso-Gastric (NG) tube to empty stomach contents, or give an antacid (like Magnesium Trisilicate) to make stomach acid safe. This prevents the mother from vomiting and breathing acid into her lungs while unconscious.
  • Give premedication like Atropine to dry up mouth and lung secretions.
  • Take one last set of vital signs, gather all her medical charts, and carefully wheel her to theatre, giving a full verbal handover to the theatre nurse. Stay with her until she is asleep if possible.

🩸 What happens in Theatre? (Auto-transfusion)

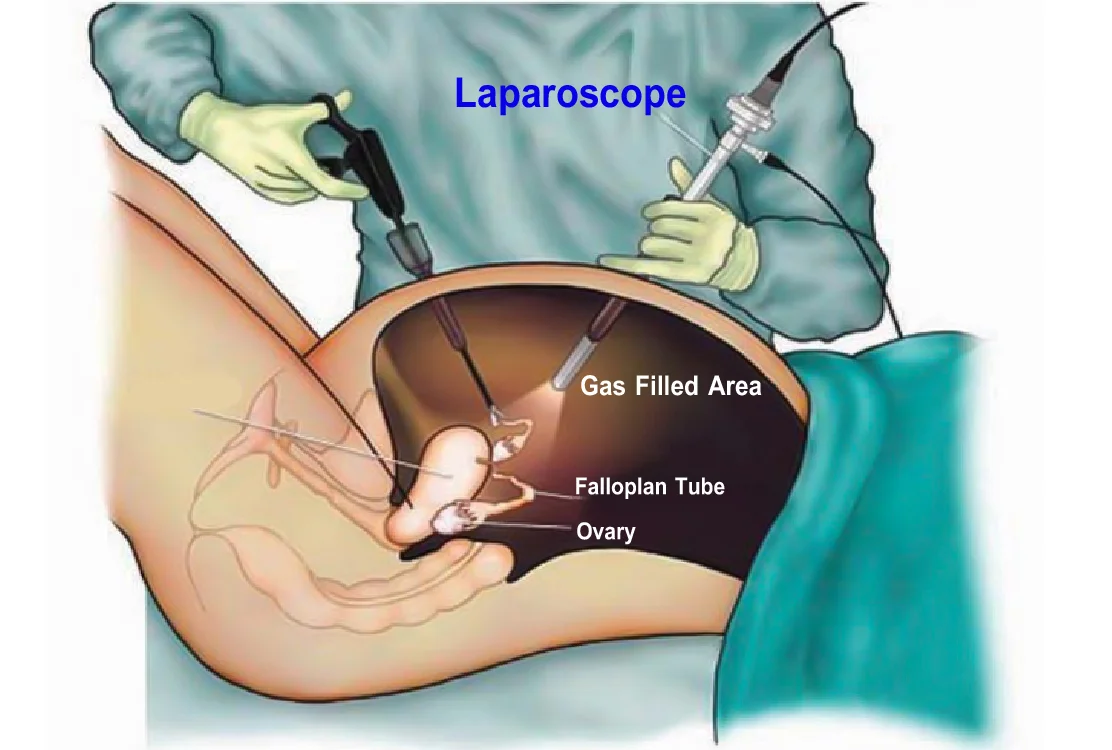
The surgeon performs a Laparotomy (opening the abdomen) and a Salpingectomy (cutting out the burst fallopian tube). The bleeding is clamped and tied off. If the bleeding just happened and the blood in her stomach is totally fresh, the surgeon can scoop it up, filter (sieve) it, mix it with an anti-clotting chemical (Sodium Citrate), and give her own blood back to her through her IV line. This amazing life-saving trick is called Auto-transfusion.

Post-Operative Care (On the Ward)

While the mother is in surgery, the ward nurse prepares a special recovery bed equipped with an oxygen machine, drip stand, observation charts, and resuscitation tray.

  • Receiving the Patient: Collect her from the recovery room. Check her Airway, Breathing, and Circulation (ABCs). Check her surgical wound for fresh bleeding. Check if the catheter is draining clear yellow urine.
  • Positioning: Place her flat (recumbent) in the bed with her head turned to one side. This allows saliva to drain out and stops her tongue from falling back and choking her.
  • Monitoring Vitals: Take her BP, Pulse, Respiration, and Temp every 15 minutes, then every 30 minutes, then every hour as she gets stronger. Continue this until she is discharged.
  • Fluid/Hydration: Continue IV Normal Saline (0.9%). Monitor the cannula site for swelling. Stop IVs only when her intestines wake up (bowel sounds are heard) and she can drink safely.

Drug Therapy and Diet

The mother will be on a heavy regimen of drugs to ensure full recovery and prevent deadly infections inside her abdomen.

  • Antibiotics: Ampicillin 500mg (6 hourly for 5 days), Ceftriaxone 2gm (once daily), Metronidazole 500mg (8 hourly), or Gentamycin 160mg (once daily).
  • Painkillers: Pethidine 100mg (8 hourly for early severe pain), Diclofenac 75mg, then switch to oral Panadol 1gm (8 hourly) when she can swallow.
  • Blood Builders: Ferrous sulphate and Folic acid to cure her severe anemia over the coming weeks.
  • Diet: Once bowel sounds are positive, start with sips of water. Upgrade to soft foods rich in Proteins (for tissue repair), Roughage (to stop constipation), and Carbohydrates (for lost energy). Remove the NG tube.
  • Physiotherapy: Force her to take deep breaths to prevent lung collapse (hypostatic pneumonia). Encourage her to wiggle her toes, then stand up and walk around quickly to prevent dangerous blood clots in her legs (Deep Vein Thrombosis).
  • Wound & Hygiene Care: Check the dressing daily. Do not let it soak with blood. Stitches are usually removed on the 7th and 8th day. Give her a bed bath until she can walk to the shower. Remove the catheter in 24-48 hours. Give laxatives (Bisacodyl 5-10mg) if she cannot pass stool.

9. Advice on Discharge & Complications

Advice on Discharge

  • Rest completely at home. Absolutely no heavy lifting or digging, to avoid bursting her healing abdominal muscles.
  • Complete every single antibiotic pill given to her.
  • Bring the husband in for STI treatment if Pelvic Inflammatory Disease (PID) caused the ectopic.
  • She must attend the hospital immediately when she gets pregnant again, to verify the new baby is in the right place.
  • Return to the clinic on her exact appointed review dates.

10. Medical Management of Ectopic Pregnancy (Methotrexate Therapy)

In modern midwifery, surgery is not always required for early, silent ectopic pregnancies. Methotrexate is a highly effective, non-surgical alternative that preserves the mother's fallopian tube, protecting her future fertility.

Mechanism of Action: Methotrexate is a folate antagonist (specifically a dihydrofolate reductase inhibitor). It works by blocking folic acid, which prevents fast-growing cells—like the embryonic trophoblastic tissue—from dividing and replicating their DNA. This causes the ectopic pregnancy to stop growing and naturally dissolve over time.

A. Patient Selection Criteria (Who Can Receive It?)

Not every ectopic pregnancy can be treated medically. The midwife must ensure the patient meets strict criteria before starting Methotrexate therapy:

  • Hemodynamic Stability: The mother must have normal vital signs (stable blood pressure and heart rate) with absolutely no signs of internal bleeding, active rupture, or shock.
  • Ectopic Mass Size: The adnexal mass containing the ectopic pregnancy must be small, typically less than 3.5 cm (35mm) on an ultrasound scan.
  • Fetal Cardiac Activity: There must be no visible fetal heartbeat inside the ectopic sac on the ultrasound.
  • Serum Beta-hCG Levels: Ideally, the baseline hCG level should be low. The absolute limit for medical management is < 5,000 mIU/mL (Success is highest when hCG is < 1,500 mIU/mL; success drops drastically if hCG exceeds 5,000 mIU/mL).
  • Normal Organ Function: The mother must have healthy kidneys and liver. Liver Function Tests (LFTs) and kidney function (creatinine) must be normal. She must not have severe blood disorders (like deep anemia or thrombocytopenia).
  • Patient Compliance: The mother must understand, agree to, and be physically able to return to the clinic for strict, repeated follow-up blood tests over several weeks.

⚠️ Absolute Contraindications to Methotrexate

Never administer Methotrexate to a mother who has: Ruptured ectopic pregnancy, active liver or kidney disease, severe anemia, active pulmonary (lung) disease, a compromised immune system, or who is currently breastfeeding (the drug passes into breast milk and is highly toxic to a baby).

B. Dosages and Administration Regimens

There are three standard clinical protocols used to administer Methotrexate:

  • 1. Single-Dose Protocol (Most Common):

    The patient receives a single intramuscular (IM) injection of Methotrexate at a dose of 50 mg/m² (calculated using the mother's body surface area based on her height and weight). It is injected into the gluteal muscle (buttock) or thigh.

  • 2. Two-Dose Protocol:

    Given as a 50 mg/m² IM injection on Day 1, followed by a second 50 mg/m² IM injection on Day 4. This is often used if the starting hCG levels are moderately high.

  • 3. Multi-Dose Protocol (Fixed Regimen):

    Alternating injections of Methotrexate (1 mg/kg IM) on Days 1, 3, 5, and 7, alternated with Leucovorin (Folinic Acid) 0.1 mg/kg IM on Days 2, 4, 6, and 8. Leucovorin acts as a "rescue drug" to protect the mother's healthy liver and bone marrow from the harsh effects of Methotrexate.

C. Follow-up Protocol: The 15% Rule

The midwife must follow a highly strict monitoring timeline to confirm that the medicine is working successfully:

Day of ProtocolClinical Action & Expected Findings
Day 1Draw blood for a baseline serum beta-hCG test. Give the first IM injection of Methotrexate. (Give Rhogam injection if the mother has an Rh-negative blood type).
Day 4Draw blood for a second beta-hCG test.
Note: It is normal for the hCG level to rise or stay flat on Day 4. This happens because the dying pregnancy cells are breaking open (lysing) and dumping their hormones into the bloodstream. Do not panic if the level is higher than Day 1.
Day 7Draw blood for a third beta-hCG test.
Day 7 EvaluationCompare the hCG levels of Day 4 and Day 7.
There must be a decrease of at least 15% between the Day 4 and Day 7 readings.
Weekly Follow-upIf the 15% drop is successful, the patient must return every 7 days for a repeat hCG blood draw. This must continue weekly until the hCG level drops to a non-pregnant level (typically < 5 mIU/mL). This process can take anywhere from 2 to 6 weeks.

🚫 Crucial Patient Care Instructions

While undergoing Methotrexate therapy, the mother must be strongly counseled to:

  • DO NOT take folic acid or prenatal vitamins: Folate blocks the action of the drug and will make the treatment fail.
  • Avoid gas-producing foods: Stomach gas causes sharp abdominal pain, which can be easily confused with a ruptured fallopian tube.
  • Avoid aspirin and NSAIDs (like Ibuprofen): These can react poorly with Methotrexate and cause liver or kidney strain. Use Paracetamol for mild pain.
  • Avoid sunlight: Methotrexate makes the skin highly sensitive to sun, leading to fast, painful sunburns.
  • Avoid vigorous exercise and sexual intercourse: Hard physical pelvic movement can physically trigger the fragile tube to rupture.
  • Use strict birth control for 3 to 6 months: If she gets pregnant immediately after taking Methotrexate, the drug can cause severe, fatal birth defects in the new baby.

D. When Has Medical Management Failed? (Indications for Surgery)

The midwife must immediately take the patient to the operating theatre for emergency surgery (Laparotomy and Salpingectomy) if any of the following signs of treatment failure occur:

  • Worsening Abdominal Pain: Sharp, severe, or worsening lower abdominal pain with rigid, guarded abdominal muscles. This is a primary warning sign that the tube has ruptured and she is bleeding internally.
  • Hemodynamic Instability: Sudden signs of shock, such as a drop in Blood Pressure (hypotension), a rapid thready pulse (tachycardia), and cold, clammy skin.
  • Suboptimal hCG Drop: If the beta-hCG level fails to drop by at least 15% between Day 4 and Day 7:
    • If she is still asymptomatic and completely stable, a second dose of Methotrexate may be administered.
    • If the hCG levels still fail to drop after the second dose, or if she develops pain, she must go straight to surgery.

Complications of Ectopic Pregnancy

Immediate ComplicationsLong-Term Complications
Hypovolemic Shock (from massive blood loss)Chronic Pelvic Sepsis / Infection
Peritonitis (inflammation of the abdominal cavity from old blood)Severe Chronic Anaemia
Severe DehydrationFibrosis and massive abdominal adhesions
Death (if not operated on rapidly)Recurrence (high risk of another ectopic pregnancy)
Secondary Infertility (struggling to get pregnant again because one tube is gone and the other may be damaged)

Quick Quiz

Ectopic Pregnancy Quiz

Gynaecology

Privacy: Your details are used only for quiz tracking and certificates.

Ectopic Pregnancy Read More »

MENSTRUAL DISORDERS
Home > Midwifery I > Menstrual Disorders

Menstrual Disorders

Overview: Menstrual Disorders are abnormalities in menstruation that occur during a woman's reproductive life. These conditions can range from the complete absence of a period (Amenorrhoea) to severely painful cramps (Dysmenorrhoea) or heavy, irregular bleeding. Understanding the exact causes, pathophysiology, and detailed nursing interventions is crucial for providing holistic care and improving the patient's quality of life.

There are several common disorders associated with the menstrual cycle that midwives and nurses frequently encounter in clinical practice. These include:

  • Amenorrhoea (Absence of periods)
  • Dysmenorrhoea (Painful periods)
  • Menorrhagia (Heavy or prolonged bleeding)
  • Metrorrhagia (Irregular bleeding between periods)
  • Polymenorrhoea / Epimenorrhoea (Frequent periods)
  • Dysfunctional Uterine Bleeding (DUB) (Abnormal bleeding with no organic cause)
  • Endometriosis (Misplaced uterine tissue)

1. Amenorrhoea

Amenorrhoea refers to the complete absence of menstruation in a female during her reproductive age.

Types of Amenorrhoea

  • Primary Amenorrhoea: This is the complete failure of menses to start by the age of 16 years. A common example is an imperforate hymen, where the girl actually menstruates internally, but the thick membrane blocks the blood from coming out.
  • Secondary Amenorrhoea: This is the cessation (stopping) of menses in a woman who has previously had normal menstrual cycles. It is officially diagnosed as secondary amenorrhoea when she goes for a period of 6 months or more without seeing her menses.

Causes of Amenorrhoea

The causes can be natural (physiological), anatomical, or hormonal:

  • Physiological Causes: Pregnancy and lactation. During pregnancy, the high levels of Oestrogen and Progesterone ensure the endometrium remains intact, resulting in no menses. During lactation, the hormone Prolactin is secreted in massive quantities by the anterior pituitary gland. This partially suppresses the Luteinizing Hormone (LH), meaning ovarian follicles might grow, but ovulation never occurs.
  • Hypothalamic Dysfunction: These patients have abnormally low levels of Follicle Stimulating Hormone (FSH) and LH. This includes congenital syndromes associated with abnormal hypothalamic-gonadal function. A specific example is Kallmann’s Syndrome (absence of the hypothalamus or congenital hypogonadotrophic hypogonadism), characterized by a lack of secondary sexual characteristics.
  • Pituitary Disorders: Conditions leading to elevated levels of prolactin (Hyperprolactinaemia), or tumors of the pituitary gland.
  • Congenital Abnormalities: Anatomical defects such as an imperforate hymen, vaginal septum, absence of the uterus, presence of a uterus but no endometrial lining, absence of ovaries, or extreme narrowing of the cervix (cervical stenosis).
  • Psychological & Environmental: Extreme fear, severe anxiety, high excitement, or a sudden change of environment or occupation.
  • Pseudoamenorrhoea: Meaning "false" amenorrhoea. A woman psychologically convinces herself she is pregnant when she is not, causing her periods to stop.
  • Medical & Surgical Causes: After a hysterectomy or surgical removal of both ovaries (bilateral oophorectomy). Exposure to full doses of radiation. Use of certain drugs, especially hormonal contraceptives. Debilitating systemic diseases like Tuberculosis (TB), HIV/AIDS, or Diabetes Mellitus (DM).
  • Other Causes: Tumors in the ovaries, uterus, or brain. Early onset of menopause, or it may simply be Idiopathic (having no known cause).

Diagnosis and Investigations

  • Detailed history taking (asking about sudden weight changes, high stress, or the growth of excessive facial/body hair which hints at hormones) and a thorough physical examination.
  • Urine test for HCG to rule out pregnancy.
  • Blood tests for hormone analysis to definitively rule out hormonal imbalance.
  • Ultrasound scans of the pelvis to visually inspect the pelvic cavity and its organs.
  • Computerized Tomography (CT) scans to check the brain (pituitary) and pelvic organs.

Management of Amenorrhoea

The treatment approach heavily depends on the root cause and is divided into Medical, Surgical, Psychological, and Nursing care.

Medical Management

  • Hormone Therapy: Prescribed to regulate levels and restore menstruation, especially in cases like Polycystic Ovary Syndrome (PCOS) or hypothalamic dysfunction.
  • Medications: Progestins or combined oral contraceptives may be used to artificially induce menstruation.
  • Hyperprolactinaemia Treatment: Treated by administering Bromocriptine, an ergot alkaloid drug that directly stops prolactin secretion.
  • Radiotherapy: Reserved strictly for patients with tumors who fail to respond to standard medical therapy.

Surgical Management

Surgery is rare but necessary for structural issues:

  • Hysteroscopic Surgery: Inserting a thin, illuminated tube (hysteroscope) through the vagina to view and cut away abnormalities like polyps or scar tissue (adhesions).
  • Imperforate Hymen: Treated by a simple surgical incision and drainage. Large amounts of trapped, old blood may be released. If the membrane is very thick, a minor plastic surgery operation is required.
  • Tumor or cyst removal in the reproductive organs.

Psychological Management

  • Offering deep psychological counseling or referring the woman to mental health professionals to help her cope with emotional distress.
  • Suggesting support groups so she can connect with other women facing similar challenges.
  • Addressing body image and self-esteem. Reassure the patient that the absence of a period does not define her femininity or her worth as a woman.

Comprehensive Nursing Management

  • Assessment: Conduct a comprehensive evaluation of her medical and menstrual history.
  • Emotional Support: Offer empathetic, gentle, and non-judgmental support.
  • Education: Teach the patient about her own reproductive anatomy, physiology, and how treatments work.
  • Lifestyle Modifications: Encourage regular exercise, balanced nutrition, stress reduction techniques, and plenty of sleep to naturally regulate hormonal balance.
  • Contraception Counseling: Discuss family planning options to prevent unintended pregnancies once her cycle returns.

2. Dysmenorrhoea

Dysmenorrhoea is the medical term used to describe severely painful menstrual cramps that occur just before or during the shedding of the uterine lining. Nearly 50% of all women experience some degree of pain, but about 10% are completely unable to perform their normal daily activities because the pain is so severe.

It can happen at any age but is uncommon in the first 6 months of a girl's first period and uncommon right before menopause. The most frequent sufferers are girls in their late teens and women in their early twenties.

The Core Cause

While the exact cause isn't fully understood, the severe cramping is directly linked to the release of strong chemicals called prostaglandins from the cells lining the uterus. These chemicals cause the muscular walls of the uterus to contract aggressively, leading to painful cramps and reduced blood supply to the muscle tissue.

Types of Dysmenorrhoea

A. Primary Dysmenorrhoea

This refers to painful menstruation that naturally starts a few years after puberty, where no exact underlying disease or pathology can be identified.

Predisposing Factors:
  • Narrow Cervical Os (Stenosis): A very tight cervix makes it difficult for blood to flow out, causing immense tension during muscle contractions.
  • Ischaemia: Reduced blood supply and oxygen to the uterine lining.
  • Hormonal Imbalance: Excess prostaglandins.
  • Retroverted Uterus: When the uterus tilts sharply backwards, causing physical tension on the ligaments.
  • Psychological Factors: High social stress, deep fear, or anxiety about menstruation.
Signs and Symptoms:
  • Lower Abdominal Pain (LAP) that ranges from mild to severe, colicky, and crampy. The pain often radiates to the lower back, thighs, and legs.
  • Severe nausea and vomiting.
  • Bowel changes like constipation or diarrhea.
  • Fainting, heavy headaches, and general body weakness (malaise).
  • Emotional irritability, nervousness, and depression.

💊 Specific Drug Management for Dysmenorrhoea

Start treatment 2 days before the expected period begins and continue until 2 days after the bleeding stops.

  • Mild Analgesics: Ibuprofen 400mg three times a day (tds).
  • Prostaglandin Synthetase Inhibitors: Mefenamic acid (250-500mg tds) or Flufenamic acid (100-200mg tds). They stop the cramps from forming.
  • Oral Contraceptives (COCs): Decreases the thickness of the uterine lining (endometrial proliferation). Given for 4-6 months; many women get permanent pain relief even after stopping.
  • Progesterones: Dydrogesterone 10mg twice a day (b.d) taken from day 5 of the cycle for 20 days to relax the uterine muscle (myometrial relaxation).
  • Antispasmodics: Buscopan to relax smooth muscle spasms.
  • Antiemetics: Phenergan to stop severe nausea and vomiting.
Other Primary Management Strategies:
  • Apply heat therapy (hot water bottles or heating pads) to the abdomen for relief.
  • Surgical widening (dilation) of a narrow cervical canal if cervical stenosis is the main problem.
  • Effective counseling, as pain can have psychological triggers. Avoid creating drug dependence.
  • Encourage proper sleep, hygiene, a balanced diet, and light exercise. (Note: Getting older or delivering a baby often permanently cures the pain by naturally relaxing the uterine muscles and improving blood flow).
  • Alternative therapies like hypnotherapy or acupuncture.
  • Note: Dilatation and Curettage (D&C) removes dead tissue but is highly discouraged as it heavily increases the risk of severe infections.

B. Secondary Dysmenorrhoea

This refers to painful periods that start suddenly, many years after a woman has already had normal, pain-free menstrual cycles. This is pathological; upon medical investigation, a clear disease or cause is usually found.

Causes:
  • Pelvic Inflammatory Disease (PID): Chronic infection of the reproductive organs.
  • Uterine Fibroids: Benign tumors causing partial, painful contractions of the uterus.
  • Endometriosis: The growth of endometrial tissue outside the uterus.
  • Endometritis: Severe inflammation of the endometrium lining.
Additional Signs & Symptoms:
  • Lower Abdominal Pain (LAP) begins much earlier—usually 3 to 4 days or even a full week before menstruation starts.
  • Painful sexual intercourse (Dyspareunia).
  • Inability to conceive (Infertility).
  • Signs of Menorrhagia (very heavy bleeding).

Nursing Care Plan for Dysmenorrhoea

Nursing DiagnosisNursing Interventions & Rationale
Acute Pain related to increased uterine contractility. - Warm the abdomen to cause vasodilation and reduce spasmodic contractions.
- Massage the painful area; therapeutic touch blocks pain signals.
- Perform light exercises to increase blood flow and improve muscle tone.
- Administer prescribed analgesics (NSAIDs) to block nociceptive pain receptors.
Ineffective Coping related to emotional stress and anxiety. - Assess the patient's understanding; anxiety is reduced by knowledge.
- Provide an opportunity to discuss the pain safely.
- Ensure she gets periods of deep sleep and rest to relax the mind and body.
Inadequate Nutrition (Less than body requirements) related to nausea and vomiting. - Encourage very small, frequent feeds which are easier for the sick stomach to tolerate.
- Administer anti-emetics like promethazine to directly block the brain's emetic (vomiting) centers.

3. Menorrhagia

Menorrhagia is characterized by abnormally heavy bleeding, prolonged menstrual bleeding (lasting longer than 7 days), or a combination of both.

Causes

  • Hormonal Imbalances: Sudden fluctuations in Estrogen and Progesterone disrupt the cycle, causing the lining to build up too much.
  • Uterine Fibroids & Polyps: Noncancerous growths or small benign tissue polyps inside the uterus that bleed heavily.
  • Adenomyosis: A painful condition where the inner lining of the uterus actually grows deep into the thick muscular wall of the uterus.
  • Endometrial Hyperplasia: An abnormal, dangerous thickening of the uterine lining.
  • Inherited Bleeding Disorders: Blood clotting issues like von Willebrand’s disease.
  • Other Factors: Pelvic Inflammatory Disease (PID), a retroverted uterus, or serious reproductive cancers (cervical or endometrial cancer).

Signs and Symptoms

  • Bleeding continuously for longer than 7 days.
  • Soaking completely through one or more heavy sanitary pads every single hour for several hours in a row.
  • Passing extremely large blood clots.
  • Extreme fatigue, tiredness, and disruption of daily activities.
  • Signs of severe anemia: Shortness of breath, rapid heart rate (tachycardia), feeling lightheaded, or dizzy.

Investigations

  • Complete medical history, physical exam, and Transvaginal Ultrasound to evaluate the uterine structure.
  • Blood tests: Complete blood count, iron levels, and hormone analysis.
  • Coagulation Profile: Bleeding time, Prothrombin time, and Clotting time. In cases of bleeding disorders, these results will be distinctly abnormal, showing a lack of available platelets or clotting factors.
  • Endometrial biopsy to rule out cancer, and a Hysteroscopy to directly look inside the lighted uterine cavity.

Management of Menorrhagia

The golden rule is to investigate and treat the exact cause.

  • Medical: Give NSAIDs to reduce pain and slightly reduce bleeding. Prescribe hormonal contraceptives (pills or hormonal IUDs) to tightly regulate cycles. Give Iron supplements to restore lost iron and cure anemia.
  • Surgical: Endometrial ablation (a minimally invasive procedure that destroys the lining of the uterus) or Uterine Artery Embolization (injecting small particles into the blood vessels to drastically reduce blood flow to the bleeding uterus).
  • Nursing Interventions: Provide education on menstrual hygiene. Manage symptoms of pain. Offer deep emotional support for the distress caused by heavy bleeding. Encourage a healthy diet.

🚨 Nursing Diagnosis: Ineffective Tissue Perfusion

Due to massive blood loss, the patient is pale, weak, and tissues are not getting enough oxygen.

  • Action 1: Assess vital signs frequently to get accurate baseline data.
  • Action 2: Lift the foot of the bed. This allows gravity to force blood flow back up to vital centers like the brain, kidneys, heart, and liver.
  • Action 3: Rapidly administer Intravenous (IV) fluids and Whole Blood transfusions to restore circulatory volume.
  • Action 4: Administer Vitamin K as prescribed to forcefully activate blood coagulation factors and stop the bleeding.

4. Metrorrhagia

Metrorrhagia is irregular or abnormal uterine bleeding that happens completely between normal menstrual periods. It is also defined as cyclic bleeding that occurs at normal intervals, but the bleeding is massive in amount (>80 ml) or duration. Metrorrhagia is always a warning symptom of some underlying organic or functional pathology.

Causes

  • Uterine Issues: Fibroids, Adenomyosis, Uterine polyps (polyps have a vast blood supply making them bleed very easily), or a retroverted uterus causing deep pelvic congestion.
  • Pelvic Endometriosis and Chronic tubo-ovarian masses.
  • Cervical Erosions: The presence of a raw wound on the cervix paired with an increased blood supply results in frequent spotting/bleeding.
  • Pregnancy Complications: A chronic threatened abortion, incomplete abortion, or retained pieces of placenta (which physically block the uterus from contracting tightly to seal off blood vessels).
  • Molar Pregnancy (Hydatidiform Mole): An abnormal mass growing after fertilization that is supplied by thousands of tiny, fragile blood capillaries that bleed easily.
  • Cancer: Malignant cancer of the cervix or endometrium.
  • Hormonal: Normal ovulation bleeding or very short cycles (polymenorrhoea).

Management

Diagnosis involves a digital and speculum exam to directly visualize the cervix, pelvic scans, hormone checks, and biopsies. Treatment relies heavily on correcting the underlying cause.

  • Prescribe targeted hormonal therapy (progestin or birth control pills) to regulate the cycle.
  • Surgical interventions to remove polyps, fibroids, or retained placental products.
  • Provide strong supportive nursing care, teaching the patient about hygiene and ensuring she comes back for critical follow-up monitoring.

5. Polymenorrhoea / Epimenorrhoea

Polymenorrhoea is a condition characterized by highly frequent menstrual periods. The periods occur at much shorter intervals than usual (between 14 and 21 days), meaning the woman bleeds every two weeks or less, though the bleeding happens at a regular, predictable pace.

Causes

  • Hormonal & Glandular: Severe fluctuations in Estrogen/Progesterone, or Thyroid disorders (both hyperthyroidism and hypothyroidism affect cycle length).
  • Polycystic Ovary Syndrome (PCOS): Causes hormonal chaos and enlarged ovaries filled with cysts.
  • Lifestyle Factors: Chronic, immense stress, excessively heavy athletic exercise, drastic weight changes, and poor nutrition completely disrupt hormonal balance.
  • Uterine Abnormalities: Fibroids, polyps, or adenomyosis.

Signs, Symptoms & Management

The patient will present with frequent bleeding, intense fatigue from constant blood loss, and severe emotional anxiety. Management involves:

  • Hormone-regulating medications to physically force the cycle to lengthen back to 28 days.
  • If caused by retained tissue or polyps, perform a Dilatation and Curettage (D&C) to scrape and clean the uterus.
  • Strict lifestyle modifications: Ensure the patient engages in stress reduction, gets adequate sleep, and eats a nutrient-dense diet to naturally calm the hormonal system.

6. Dysfunctional Uterine Bleeding (DUB)

Dysfunctional Uterine Bleeding (DUB) is abnormal bleeding that results entirely from hormonal changes rather than from physical trauma, inflammation, pregnancy, or a tumor. It is defined as abnormal bleeding with absolutely no organic cause or underlying medical condition.

Incidence: It has a wide prevalence, but accounts for approximately 10% of patients attending outpatient gynaecology clinics.

⚠️ Clinical Rule for DUB

A diagnosis of Dysfunctional Uterine Bleeding is an official "Diagnosis of Exclusion." This means a doctor or midwife can only diagnose a woman with DUB after every other possible cause of bleeding (like cancer, fibroids, or pregnancy) has been completely tested and ruled out.

Pathophysiology

DUB is triggered by sustained, unbroken levels of Oestrogen. This continuous Oestrogen causes the endometrium to grow incredibly thick. Because the hormones are imbalanced, this thickened lining does not shed cleanly all at once; it sheds incompletely and irregularly over long periods.

Furthermore, there is a disturbance in the delicate endometrial blood vessels, capillaries, and the local coagulation of blood. This occurs due to an alteration in the ratio of endometrial prostaglandins (which normally balance bleeding and clotting) and an incoordination in the Hypothalamo-Pituitary-Ovarian (HPO) axis.

Management Strategies

Treatment is highly customized based on the woman's age, the thickness of her uterine lining, and whether she wants to have children in the future.

  • Acute Medical Stop: Heavy bleeding can be stopped quickly using high-dose oral contraceptives (COC) or Intravenous (IV) Oestrogen, followed by oral progestin. This generally stops the massive bleeding within 12 to 24 hours. Afterward, normal low-dose COCs are given for at least 3 months to stabilize the body.
  • Progestin Only: If a woman cannot take Oestrogen safely, she is given Progestin-only pills for 10-14 days each month to force a clean shed of the lining.
  • Fertility Goals: If the woman desperately wants to become pregnant, a drug called Clomiphene is given orally to forcefully induce ovulation and correct the hormonal axis.
  • Surgical D&C: Used quickly if hormonal therapy fails to stop the bleeding.
  • Total Hysterectomy: Strongly indicated if the woman is over 35 years old, her uterine lining is dangerously thick, it contains abnormal pre-cancerous cells, and she definitively does not want to become pregnant.

7. Endometriosis

Endometriosis is a severe, chronic, and incredibly painful condition where tissue that behaves exactly like the lining of the uterus (the endometrium) grows outside the uterus. This "misplaced" tissue still responds to monthly hormones—it thickens, breaks down, and bleeds inside the body cavity, causing massive inflammation and pain.

Incidence: Affects 10-15% of women between 25 and 45 years old. Alarmingly, it is found in 25-50% of all women suffering from infertility.

Common Sites of Misplaced Tissue

This stray tissue can grow almost anywhere, including: the abdominal organs, ovaries, pelvic ligaments, intestines, ureters, urinary bladder, vagina, vulva, navel, lungs, nose, conjunctiva of the eye, and rarely, on normal skin.

Causes and Predisposing Factors

  • Retrograde Menstruation: The most widely accepted theory. Menstrual blood flows backwards through the fallopian tubes and spills into the open pelvic cavity, where the tissue implants and grows like a weed.
  • Hormonal & Immune: Estrogen promotes the growth, while a weakened or dysfunctional immune system fails to seek out and destroy this abnormal tissue outside the uterus.
  • Genetics & Race: It tends to run heavily in families (especially first-degree relatives like a mother or sister) and is more common in Caucasian women.
  • Surgical Transfer: Previous surgeries involving the uterus (like C-Sections or D&C) can accidentally drag and transplant endometrial cells to surgical scars.
  • Other Factors: Environmental toxins, having a retroverted uterus, or having a first baby very late in life (late primipara over 30 years old).

Signs and Symptoms

  • Lower abdominal pain and extremely painful periods.
  • Painful sexual intercourse (Dyspareunia).
  • Infertility (due to blocked tubes and scarred ovaries).
  • Pain when opening the bowels (defecating).
  • Rectal Bleeding: Bleeding from the anus during menstruation because endometrial tissue has grown inside the rectum and is shedding.
  • Visible bleeding from strange sites (like the nose or a surgical scar) exclusively during menstruation.
  • Palpable masses and the formation of heavy scar tissue that glues organs together (Adhesions).

Diagnosis and Medical Management

Diagnosis requires a Laparoscopy to directly see the tissue, followed by a microscopic biopsy to officially confirm it. Ultrasounds, MRIs, and a blood test for the marker cell CA-125 are also utilized.

  • Hormonal Suppression: The goal is to shut down the ovaries to starve the misplaced tissue. This is done using continuous COCs, heavy Progestin, or powerful GnRH agonists.
  • Surgical Excision: Laparoscopic surgery to physically cut out, burn, or destroy as much of the abnormal growths as possible to restore anatomy and relieve pain.
  • Total Hysterectomy: As a last resort, combined with the removal of both ovaries, when the disease destroys the pelvic organs and all other treatments fail.
  • Fertility Assistance: Recommending In Vitro Fertilization (IVF) for patients desperate to bypass their scarred fallopian tubes and conceive.

⚠️ Severe Complications of Endometriosis

If left untreated, Endometriosis leads to permanent Infertility, crippling chronic daily pain, and massive internal scarring (Adhesions). It also forms dangerous ovarian cysts filled with old, dark menstrual blood, medically referred to as Endometriomas or "Chocolate Cysts."

Quick Quiz

Menstrual Disorders Quiz

Gynaecology

Privacy: Your details are used only for quiz tracking and certificates.

MENSTRUAL DISORDERS Read More »

Introduction To Gynaecology

Introduction To Gynaecology

Gynaecology is the study of diseases affecting the female reproductive system.

As the genital tract is closely linked anatomically with the urinary tract and the large bowel, certain disorders of the urethra, bladder and rectum may lead the woman to a gynaecologist.

General causes of gynaecological problems

  • Congenital abnormalities: eg absence of the vagina, ovaries, uterus or divided uterus.
  • Environment: This can cause physical or mental illness.eg stress or anxiety that can lead to absence of menstruation.
  • Pathological agents: In relation with entry of pathogenic micro-organisms which may lead to infection.eg vaginitis, vulvitis etc.
  • Trauma: Genetic organs may be traumatized by instruments leading to fistula.

Clinical methods of assessing a gynaecological patients.

  • History taking

The most important information is always provided by the patient or relatives. History taking tactics are required for it is concerned with discussing intimate matters. Therefore, privacy is essential in order to get reliable information from the patient.

  1. Personal data: This includes name, age, address, next of kin, occupation, religion, tribe etc.
  2. Presenting complaints: eg Pain onset
  • Where it is felt
  • Intensity
  • Defecation or micturition
  • Dyspareunia

      3. History of presenting complaints.

  1. Obstetric history: Number of pregnancies, abortion, type of delivery, history of trauma, prolonged labour etc.
  2. Menstrual cycle: Menarche, regularity, duration and length of cycles, volume of blood loss etc. 
  3. Social history: Look out for marital status, life style, smoking, alcohol, occupation etc. 
  4. Past medical and surgical history: Has she ever suffered from a serious disease eg. Tuberculosis, had an accident which involved the spine, pelvis and lower limbs or any operation on her pelvic organs.
  5. Gynaecological history: Has she ever had any gynaecological condition like fibroids, rectal vaginal fistula, vesicle vaginal fistula, perennial tears, abortions etc., any operations on the cervix or dilation and curettage. 

        4.  Examination 

  1. General examination

The general examination is important in gynaecology. This is done from head to toe. Note. 

  • General appearance of the patient
  • Behavior
  • Look out for signs of anaemia
  • Examine breasts: Look for signs of pregnancy and any discharge.  Examine the breast to exclude malignancies.
  • Abdomen It is inspected for size and shape and palpated for tumours.
  • Pelvic examination: This is the last examination done to confirm the diagnosis already suspected during history taking.

Note:

  • The patient should consent for the examination, if not married, parents can consent for her because the hymen can be broken.
  • The patients bladder and bowels must be empty.
  • Good light is also needed.

      2. Vaginal examination

Each part of the genital tract should be examined in a logical sequence;

  • Vulva
  • Vagina
  • Cervix (inspect for tears, prolapse etc.)
  • Body of the uterus
  • Pouch of Douglas

NB: The cervix and uterus should be examined for size, shape, position and tenderness.

Special procedures and investigations

These are useful to fill gaps which remain after history taking during clinical assessment.

  1. Evacuation: It refers to removal of the contents of a cavity. It is done when pelvic examination has not been possible. Its disadvantage is that important signs of tenderness are missed out. (examination is done under anaesthesia)
  2. Curettage:  Refers to scrapping of the internal surface of an organ or body cavity by means of a spoon shaped instrument called a curette. It is done to; Remove retained products of conception and to obtain a specimen for diagnostic purposes
  3. Biopsy:  This is the removal of a small piece of leaving tissue from an organ or part of the body for microscopic examination so as to exclude certain diseases. It can be obtained from the cervix, endometrium etc.
  4. Ultra sound scan: The use of ultrasound produces images of structures in the human body using sound waves of high frequency. This is now used widely to detect diseases of the pelvic organs and pregnancy.
  5. Hysterosalpingography: Refers to x-ray imaging of the uterus and fallopian tubes. It is useful in diagnosing;
  • Tubal obstruction
  • Peritubal and intrapelvic adhesions
  • Malformations of the uterus
  • Small intracavity tumours
  • Detect the internal os of the cervix causing abortion and premature labour.

      6. Laparoscopy: Examination of abdominal structures by means of a laparoscope (type of endoscope). This is passed through a small incision in the wall of the abdomen. Used when;

  • Taking a biopsy
  • Aspirating cysts
  • Dividing adhesions
  • Collecting ova for vitro fertilization

GYNAECOLOGICAL OPERATIONS

  • Hysterectomy: This is surgical removal of the uterus.

    Types of hysterectomy

  1. Wertheim’s hysterectomy: It’s a radical operation performed for cervical cancer involving removal of the entire uterus, the connective tissue and lymph nodes close to it, fallopian tubes, ovaries and the upper part of the vagina.
  2. Subtotal hysterectomy: Surgical removal of the body of the uterus leaving the neck (cervix) in place.
  3. Total hysterectomy: Surgical removal of the entire uterus.

 Indications 

  • Fibroids 
  • Cancers
  • Raptured uterus
  • Salpingectomy : Refers to surgical removal of the fallopian tubes.

 Indications 

  • Raptured ectopic pregnancy
  • Chronic salpingitis
  • Vesico-vaginal fistula repair :This is an operation done to repair an abnormal communication between the bladder and vagina.
  • Oophorectomy :This is the surgical removal of the ovary(s)

Indications 

  • Tumours of the ovary
  • Chronic oophoritis
  • Myomectomy : Refers to surgical removal of one or more fibroids from the uterus.
  • Rectal vaginal fistula : An operation done to repair an abnormal communication between the rectum and vagina.
  • Mastectomy : Surgical removal of the breast.

Types

  1. Radical mastectomy: Surgical removal of the breast with the skin and all lymphatic tissue of the armpit. It is performed when breast cancer has spread to involve the lymph nodes.
  2. Simple mastectomy: Surgical removal of the breast retaining the skin and if possible the nipple. It is performed for extensive but not necessarily invasive tumours.
  • Tubal ligation :An operation done by tying and cutting of fallopian tubes which is used as a permanent family planning method.
  • Vulvectomy: Surgical removal of the vulva.

 Types

  1. Simple vulvectomy: Excision of the labia majora, minora and clitoris to eradicate a non-malignant growth.
  2. Radical vulvectomy: Excision of the labia majora, minora, clitoris and all regional lymph nodes on both sides together with the skin covering these areas. It is carried out in malignant growths.
  • Dilatation and curettage

An operation in which the cervix(neck) neck of the uterus is dilated using a dilator (heggar's dilators) and the endometrium is lightly scrapped off with a manual curette or removed by suction using an aspirator.

Indications

  • Removal of any retained products after abortion
  • Obtaining endometrial biopsy for histological examination.
  • Perineoplasty: An operation done to enlarge the vaginal opening by incising the hymen and part of the perineum.
  • Perineorrhaphy: Surgical repair of a damaged perineum. The damage is usually as a result of a tear sustained during child birth.

Introduction To Gynaecology Read More »

Want notes in PDF? Join our classes!!

Send us a message on WhatsApp
0726113908

Scroll to Top